Related Experiment Video
Updated: Mar 20, 2026
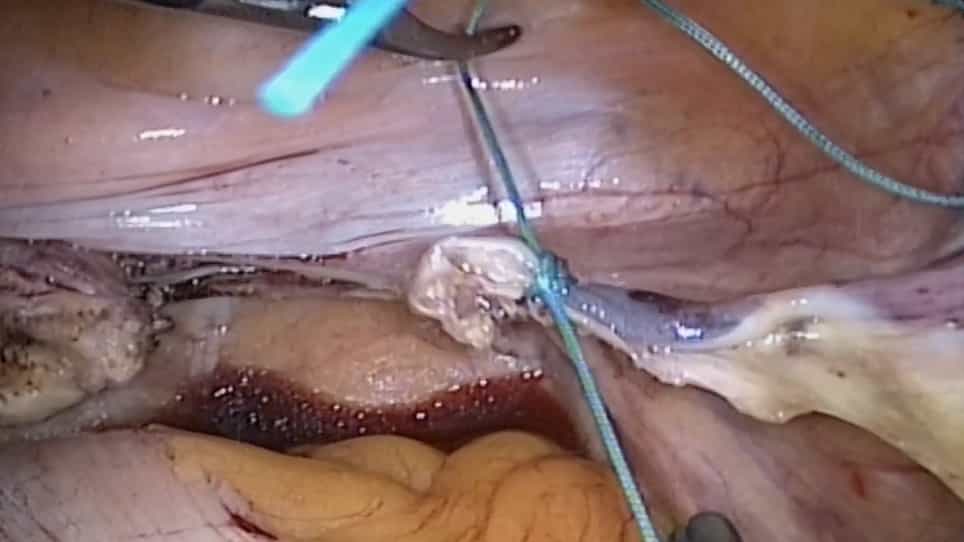

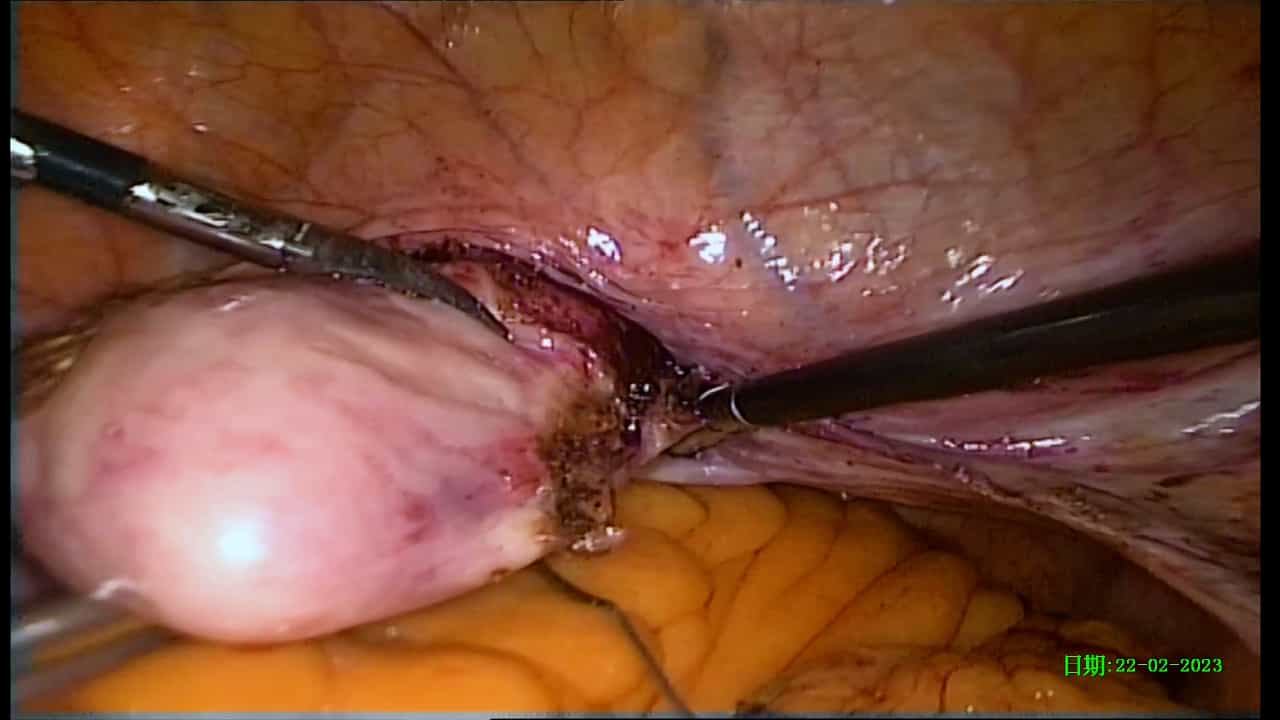
Laparoscopic Non-Mesh Cerclage Pectopexy for Pelvic Organ Prolapse
Published on: September 13, 2022
Laparoscopic wrap round mesh sacrohysteropexy for the management of apical prolapse
Anthony Sarkis Kupelian1, Arvind Vashisht2, Nikola Sambandan2
1Urogynaecology and Pelvic Floor Unit, University College London Hospital, Clinic 2, Lower Ground, EGA Wing, 25 Grafton Way, London, WC1E 6DB, UK. anthonyskupelian@hotmail.com.

Introduction And Hypothesis:
Interest in uterine-conserving surgery for apical prolapse is growing. Laparoscopic sacrohysteropexy is one of the conservative surgical options, although different surgical approaches have been described. We report medium-term outcome data using a bifurcated mesh implant, employing 'wrap round' uterine attachment.
Methods:
All procedures undertaken at our unit were reviewed. Study inclusion was contingent on the collection of baseline and 3-month anatomical and symptomatic outcome data. Medium-term follow-up data were collected by telephone review. Anatomical outcome was reported using the Pelvic Organ Prolapse Quantification scale. Symptom prevalence and treatment response were assessed using validated instruments including the Patient Global Impression of Improvement scale (PGI-I), and the International Consultation on Incontinence Urinary Incontinence Short Form (ICIQ-UI) and Vaginal Symptoms (ICIQ-VS) questionnaires. Patient satisfaction was reported using Kaplan-Meier survival analysis.
Results:
Data were available for 110 patients. Of 80 patients providing PGI-I data at 3 months, 75 (94 %) described their prolapse symptoms as 'much better' or 'very much better'. Anatomical success in the apical compartment was 98 %. ICIQ-UI and ICIQ-VS responses demonstrated significant improvement. Despite a concurrent vaginal repair in only 11 % of patients, satisfaction at a mean follow-up of 2.6 years was 96 %. Repeat surgery for vaginal wall prolapse was required in only 5 % of patients. No safety concerns or graft complications were recorded.
Conclusions:
This surgical variant of laparoscopic sacrohysteropexy is safe and highly effective. These data also cast doubt on the need for correction of modest vaginal wall prolapse at the time of surgery, and imply that apical prolapse may play a dominant role in the generation of symptoms.