Related Experiment Video
Updated: Mar 20, 2026


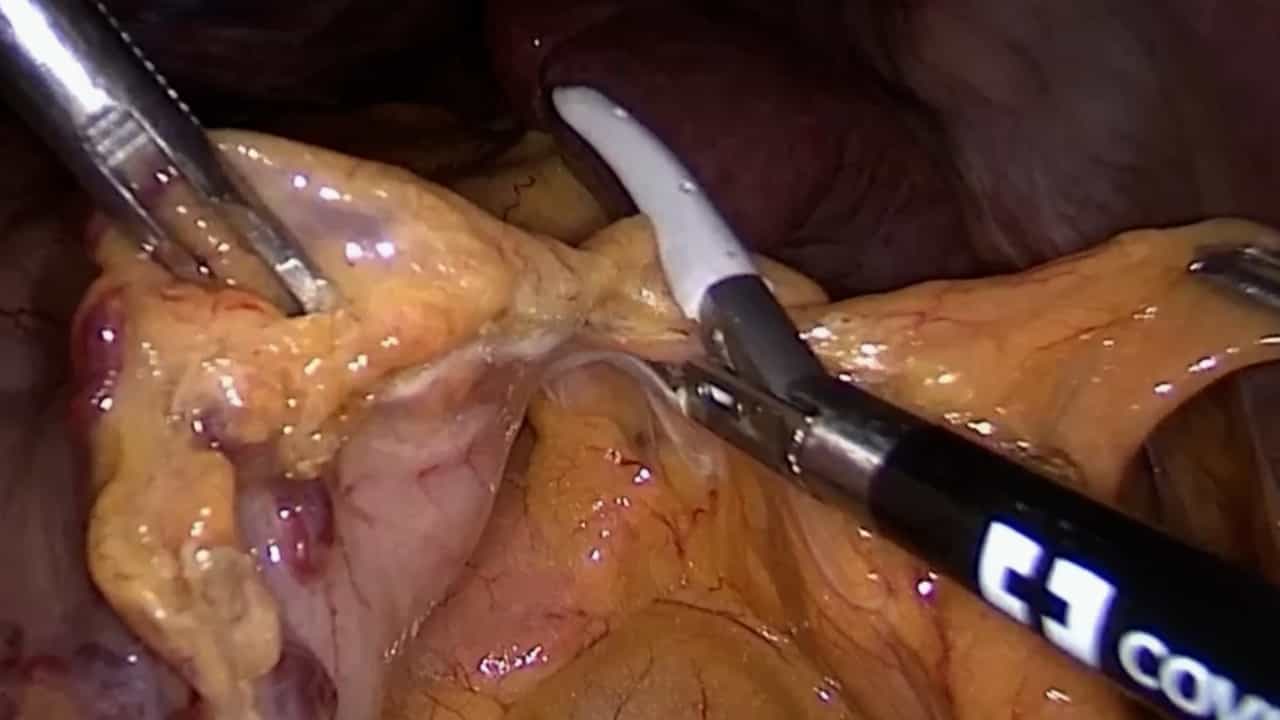
Laparoscopic Splenectomy with Pericardial Devascularization for Hypersplenism and Esophageal Variceal Hemorrhage Due to Portal Hypertension
Published on: November 15, 2024
Laparoscopic splenic artery ligation for hypersplenism in cirrhosis: A case series
Hirdaya H Nag1, Sandip Chandrasekar1, John M Manipadum1
1Department of Gastrointestinal Surgery, Govind Ballabh Pant Institute of Postgraduate Medical Education and Research, New Delhi, India.

Insights
Laparoscopic splenic artery ligation (LSAL) offers a safe and feasible alternative to splenectomy for patients with hypersplenism in cirrhosis (HIC). This minimally invasive approach shows promising results in improving blood counts and MELD scores, though further research is needed.
Area of Science:
- Gastroenterology
- Hepatology
- Minimally Invasive Surgery
Background:
- Splenectomy for hypersplenism in cirrhosis (HIC) carries significant risks.
- Laparoscopic splenic artery ligation (LSAL) presents a potential alternative treatment.
Purpose of the Study:
- To assess the safety and feasibility of LSAL in treating HIC.
- To evaluate the efficacy of LSAL in improving hematological parameters and MELD scores.
Main Methods:
- Retrospective analysis of prospectively collected data.
- Ten patients with HIC underwent LSAL between October 2012 and February 2015.
Main Results:
- Significant improvements observed in leukocyte and platelet counts, as well as MELD scores (P < 0.05).
- Complications included intraoperative bleeding (20%), splenic cyst (10%), and post-ligation syndrome (40%).
- One patient (10%) required splenectomy due to inadequate response after a median follow-up of 19.5 months.
Conclusions:
- LSAL is a safe and feasible option for palliating symptomatic HIC.
- Further prospective trials are warranted to confirm these findings.
Background:
Splenectomy for the treatment of hypersplenism in patients with cirrhosis (HIC) is related with complications. Laparoscopic splenic artery ligation (LSAL) may be an alternative treatment option.
Aims:
To evaluate safety and feasibility of LSAL in the treatment of HIC.
Patients And Methods:
Retrospective analysis of prospectively collected data of ten patients with HIC who were treated with LSAL from October 2012 to February 2015.
Results:
The median (range) age was 33.2 (13-56) years and sex distribution was equal. The median (range) leukocyte counts (×10(9)/L) before, and at 3, 6 and 12 months after LSAL were 2.2 (0.8-8.2) and 5.65 (2.78-10.7), 4.7 (2.8-7.8) and 4.95 (3.4-7.7) respectively. The median (range) platelet counts (×10(9)/L) before and at 3, 6 and 12 months after LSAL were 25.5 (11-65) and 75 (39-289), 74 (32-184) and 76 (56-251) respectively. Following LSAL, there was a significant improvement in total leucocyte count, platelet count and Model for End-Stage Liver Disease (MELD) score (P < 0.05). Two patients (20%) developed intraoperative bleeding and required conversion; one of these two patients developed splenic cyst that required radiological intervention. Four patients (40%) had post ligation syndrome (PLS) that was managed conservatively. During a median (range) follow-up of 19.5 (5-29) months, one patient (10%) required splenectomy due to inadequate response.
Conclusion:
LSAL is a safe and feasible treatment option for the palliation of symptomatic HIC, however, further prospective trials are necessary for confirmation.