Related Experiment Video
Updated: Mar 20, 2026
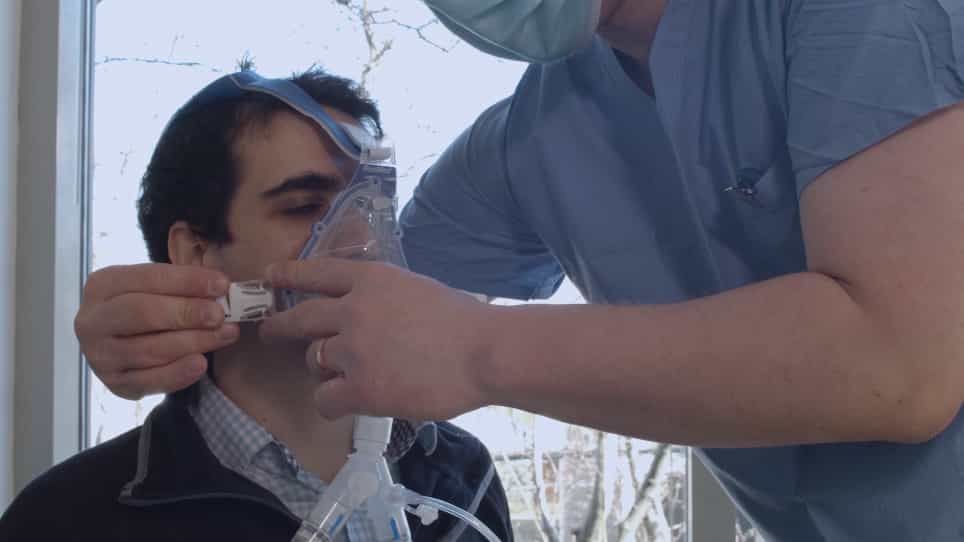

A Novel Inhalation Mask System to Deliver High Concentrations of Nitric Oxide Gas in Spontaneously Breathing Subjects
Published on: May 4, 2021
Effect of Inhaled β2-Agonist on Exhaled Nitric Oxide in Chronic Obstructive Pulmonary Disease
Mostafa Amer1, Jan Cowan1, Andrew Gray2
1Otago Respiratory Research Unit, Department of Medicine, University of Otago, Dunedin, New Zealand.

Abstract:
The fractional exhaled nitric oxide measured at an expiratory flow of 50mL/s (FENO50) is a marker of airway inflammation, and high levels are associated with greater response to steroid treatment. In asthma, FENO50 increases with bronchodilation and decreases with bronchoconstriction, the latter potentially causing an underestimate of the degree of airway inflammation when asthma worsens. It is unknown whether the same effect occurs in chronic obstructive lung disease (COPD). Likewise, it is not known whether changes in airway calibre in COPD patients alter flow-independent parameters describing pulmonary nitric oxide exchange, such as the maximal flux of nitric oxide (NO) from the proximal airway compartment (J'awNO) and the distal airway/alveolar concentration of NO (CANO). We recruited 24 patients with COPD and performed FENO analysis at multiple expiratory flows before and after treatment with inhaled β2-agonist bronchodilator therapy. For the 21 patients analysed, FENO50 rose from 17.1 (1.4) ppb (geometric mean (geometric SD)) at baseline, to 19.3 (1.3) ppb after bronchodilator therapy, an increase of 2.2 ppb (95% CI, 0.7-3.6; P = 0.005). There were non-significant changes in flow-independent NO parameters. The change in FENO50 correlated positively with the change in J'awNO (rs = 0.67, P < 0.001; rs = 0.62, P = 0.002 before and after correction for axial back-diffusion respectively) following bronchodilation. Inhaled bronchodilator therapy can increase exhaled nitric oxide measurements in COPD. The standardisation of inhaled bronchodilator therapy before FENO analysis in COPD patients should therefore be considered in both research and clinical settings.
More Related Videos


Related Concept Videos
 01:20
Chronic Obstructive Pulmonary Disease-II: Pathophysiology
Chronic Inflammation
 01:26
COPD: Management Using Bronchodilators and Corticosteroids
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:24
Chronic Obstructive Pulmonary Disease
Smoking is a primary risk factor for COPD, with over 80% of patients having a history of it. Patients typically experience progressive dyspnea or labored breathing, frequent coughing, and recurrent pulmonary infections. Many eventually succumb to respiratory failure, characterized by...
 01:20
Chronic Obstructive Pulmonary Disease-I: Introduction
 01:20
COPD: Pathogenesis and Clinical Features
The primary cause for the onset of COPD is cigarette smoking and exposure to air pollution. These hazardous factors initiate a chain reaction within the lungs, resulting in chronic inflammation, damage to the airways, and a...