Related Experiment Video
Updated: Mar 19, 2026

Laparoscopic Anterior Right Hepatectomy: A Single-Center Experience
Published on: December 4, 2023
Laparoscopic Right Hepatectomy for Cirrhotic Patients: Takasaki's Hilar Control and Caudal Approach
Jaime Arthur Pirola Krüger1,2, Gilton Marques Fonseca3, Fabrício Ferreira Coelho3
1Hospital das Clinicas (HC/FMUSP), University of Sao Paulo, São Paulo, Brazil. jaime.kruger@hc.fm.usp.br.

Insights
Laparoscopic hepatectomy using the caudal approach is feasible for cirrhotic patients with hepatocellular carcinoma (HCC). This technique offers reduced complications and adequate oncologic outcomes, benefiting patients with liver disease.
Area of Science:
- Hepatobiliary surgery
- Minimally invasive surgery
- Surgical oncology
Background:
- Laparoscopic hepatectomy offers benefits for cirrhotic patients with hepatocellular carcinoma (HCC), including reduced bleeding and complications.
- Adequate inflow control is crucial in cirrhotic patients to minimize blood loss during liver surgery.
- The caudal approach, a laparoscopic technique, involves initiating parenchymal transection from the visceral surface, potentially reducing tumor cell dissemination.
Observation:
- A 46-year-old male with viral and alcoholic cirrhosis underwent a totally laparoscopic right hepatectomy for a 4-cm HCC.
- The procedure utilized six ports, with specimen extraction via a Pfannenstiel incision and a 10-mm 30° scope.
- Key vascular structures were managed using laparoscopic vascular staplers under 12 mmHg pneumoperitoneum.
Findings:
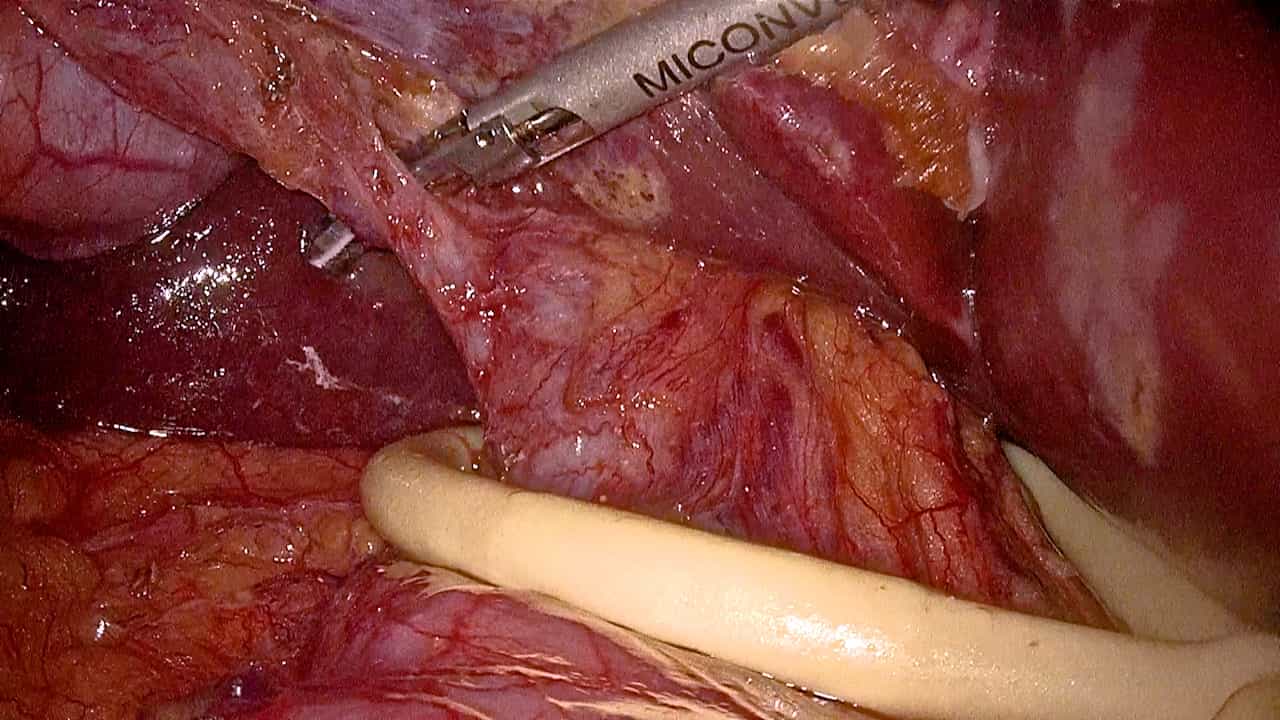
- The surgery employed the laparoscopic Takasaki technique with en bloc extrafascial right pedicle control and caudal parenchymal transection.
- Operative time was 450 minutes with an estimated blood loss of 800 ml, requiring no transfusions.
- The intervention achieved oncologic adequacy with reduced morbidity.
Implications:
- The laparoscopic Takasaki technique combined with the caudal approach is a viable option for HCC in cirrhotic patients.
- This minimally invasive approach can lead to improved patient outcomes compared to open surgery.
- Further adoption of these techniques may enhance the management of liver cancer in patients with underlying liver disease.
Background:
Cirrhotic patients bearing hepatocellular carcinomas (HCC) derive benefits from laparoscopic hepatectomy1 - 6 such as reduced bleeding, less overall and liver-specific complications, and fewer adhesions in the case of future reoperation or transplantation.7 - 10 Bleeding is concerning in the setting of cirrhosis,11 - 15 and adequate inflow control reduces blood loss. The caudal approach is the laparoscopic counterpart of the anterior approach to open surgery. It implies in parenchymal transection initiated from the visceral surface of the liver after limited hepatic mobilization, reducing the risk of increased circulating tumoral cells.16 - 18 Venous outflow transection and completion of ligament mobilization are left as last steps.
Methods:
A 46 years-old-male with hepatitis C virus and alcoholic cirrhosis was diagnosed with a 4-cm HCC (right hepatic lobe). Expected future liver remnant was 45 % of his total liver volume. A totally laparoscopic right hepatectomy was performed using six ports, and the specimen was removed through a Pfannenstiel auxiliary incision. A 10-mm 30° scope was used. The pneumoperitoneum pressure was set to 12 mmHg. The right hepatic pedicle, the caudate lobe, and the major hepatic veins were managed with laparoscopic vascular staplers.
Results:
Surgery was performed with limited liver mobilization and en bloc extrafascial right pedicle control (Takasaki's technique),19 followed by caudal parenchymal transection along the paracaval plane. The operative time was 450 min, and the estimated blood loss was 800 ml (no transfusion was required).
Conclusion:
The laparoscopic Takasaki technique and caudal approach are feasible procedures in the setting of cirrhosis, resulting in an oncologic adequate intervention with less morbidity.