Related Experiment Video
Updated: Mar 19, 2026


Quantification of the Immunosuppressant Tacrolimus on Dried Blood Spots Using LC-MS/MS
Published on: November 8, 2015
Therapeutic variability in adult minimal change disease and focal segmental glomerulosclerosis
Gema Fernandez-Juarez1, Javier Villacorta1, Gloria Ruiz-Roso2
1Department of Nephrology , Hospital Universitario Fundación Alcorcón , calle Budapest 1, Alcorcón, Madrid , Spain.

Background:
Variability in the management of glomerulonephritis may negatively impact efficacy and safety. However, there are little/no data on actual variability in the treatment of minimal change disease (MCD)/focal segmental glomerulosclerosis (FSGS) in adults. We assessed Spanish practice patterns for the management of adult nephrotic syndrome due to MCD or FSGS. The absence of reasonably good evidence on treatment for a disease often increases the variability substantially. Identification of evidence-practice gaps is the first necessary step in the knowledge-to-action cyclical process. We aim to analyse the real clinical practice in adults in hospitals in Spain and compare this with the recently released Kidney Disease: Improving Global Outcomes clinical practice guideline for glomerulonephritis.
Methods:
Participating centres were required to include all adult patients (age >18 years) with a biopsy-proven diagnosis of MCD or FSGS from 2007 to 2011. Exclusion criteria included the diagnosis of secondary nephropathy.
Results:
We studied 119 Caucasian patients with biopsy-proven MCD (n = 71) or FSGS (n = 48) from 13 Spanish hospitals. Of these patients, 102 received immunosuppressive treatment and 17 conservative treatment. The initial treatment was steroids, except in one patient in which mycophenolate mofetil was used. In all patients, the steroids were given as a single daily dose. The mean duration of steroid treatment at initial high doses was 8.7 ± 13.2 weeks and the mean global duration was 38 ± 32 weeks. The duration of initial high-dose steroids was <4 weeks in 41% of patients and >16 weeks in 10.5% of patients. We did find a weak and negative correlation between the duration of whole steroid treatment in the first episode and the number of the later relapses (r = -0.24, P = 0.023). There were 98 relapses and they were more frequent in MCD than in FSGs patients (2.10 ± 1.6 versus 1.56 ± 1.2; P = 0.09). The chosen treatment was mainly steroids (95%). Only seven relapses were treated with another drug as a first-line treatment: two relapses were treated with mycophenolate and five relapses were treated with anticalcineurinics. A second-line treatment was needed in 29 patients (24.4%), and the most frequent drugs were the calcineurin inhibitors (55%), followed by mycophenolate mofetil (31%). Although cyclophosphamide is the recommended treatment, it was used in only 14% of the patients.
Conclusions:
We found variation from the guidelines in the duration of initial and tapered steroid therapy, in the medical criteria for classifying a steroid-resistant condition and in the chosen treatment for the second-line treatment. All nephrologists started with a daily dose of steroids as the first-line treatment. The most frequently used steroid-sparing drug was calcineurin inhibitors. Cyclophosphamide use was much lower than expected.
More Related Videos
 09:40
Isolation, Characterization, And High Throughput Extracellular Flux Analysis of Mouse Primary Renal Tubular Epithelial Cells
Published on: June 20, 2018
 07:35
Use of Ultra-high Field MRI in Small Rodent Models of Polycystic Kidney Disease for In Vivo Phenotyping and Drug Monitoring
Published on: June 23, 2015
Related Concept Videos
 01:24
Dosage Regimen: Individualization
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant
 01:24
Nephrotic Syndrome I : Introduction
 01:25
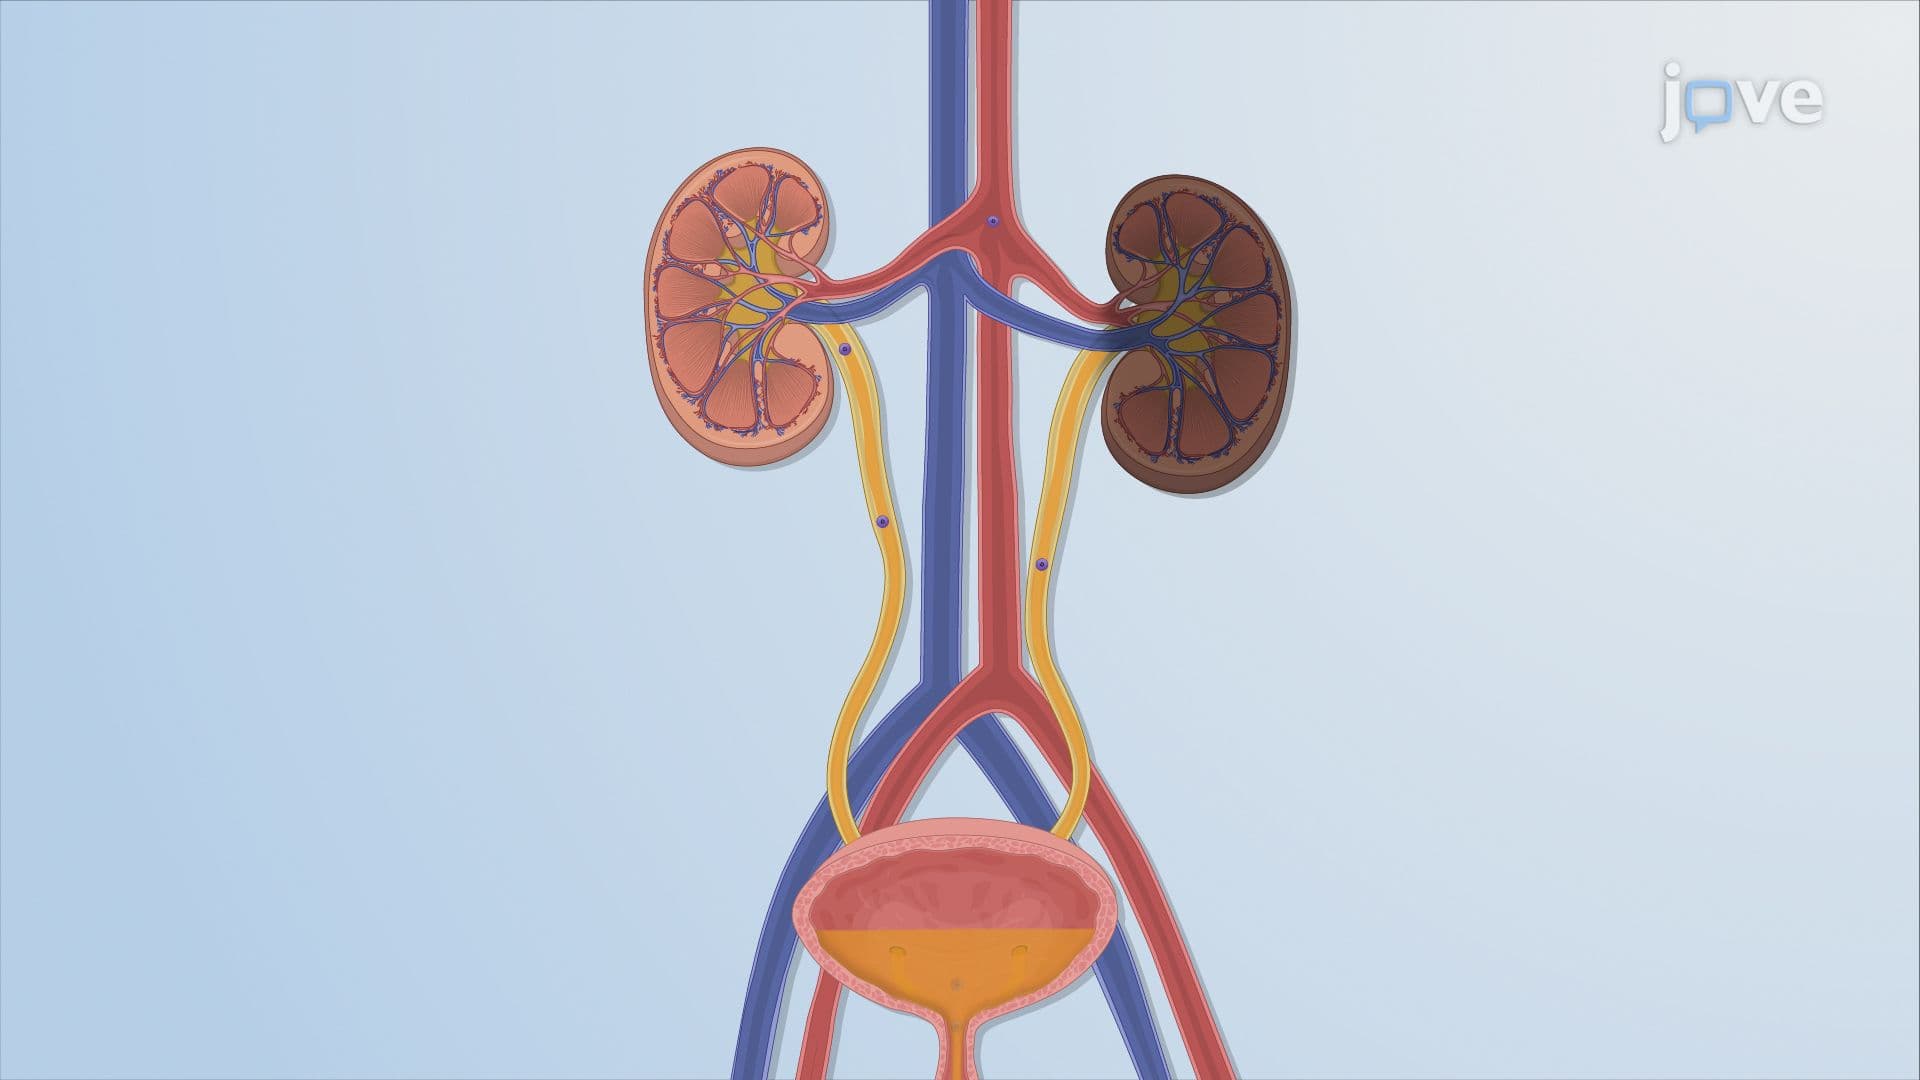
Drug Dosing in Renal Diseases: Measurement of Glomerular Filtration Rate
 01:28
Drug Dosing in Renal Diseases: Estimation of Glomerular Filtration Rate Based on Serum Creatinine Concentration
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...