Related Experiment Video
Updated: Mar 19, 2026
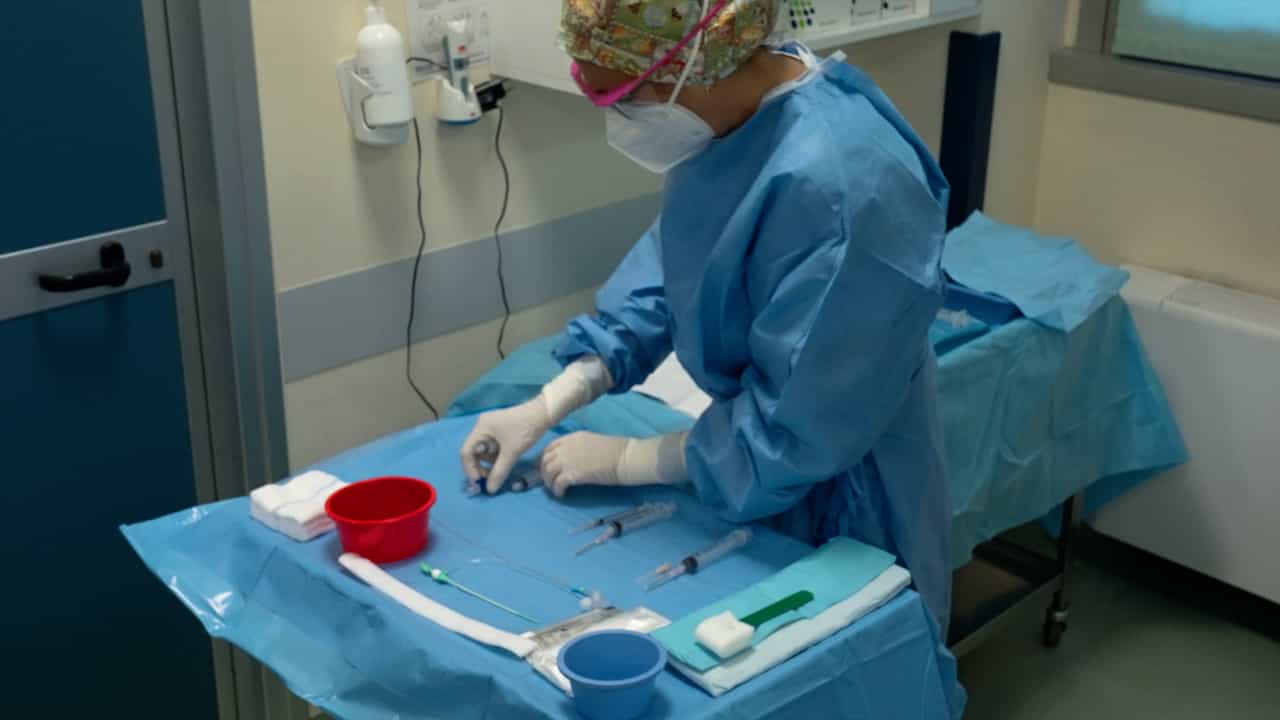

Occlusion of the Great and Small Saphenous Vein Using Copolymeric Glue Based on N-Butyl Cyanoacrylate and Methacryloxy Sulfolane
Published on: December 9, 2022
Compression use in the era of endovenous interventions and wound care centers
Seshadri Raju1, Fedor Lurie2, Thomas F O'Donnell3
1The RANE Center, St. Dominic's Memorial Hospital, Jackson, Miss.

Background:
Compression has long been the mainstay of treatment in chronic venous disease (CVD). The current treatment paradigm emphasizes compression as primary treatment, awarding saphenous ablation only an optional role. The advent of endovenous interventions, such as endovenous ablation (EVA) of the saphenous vein and iliac vein stenting, has dramatically expanded therapeutic options. The relative roles of the old and newer techniques are in a state of flux and need to be redefined. Herein we provide a broad review of compression use in the context of emergent endovenous therapies.
Methods:
Relevant key literature is selectively reviewed. It includes many past randomized controlled studies but also newer case series with a lower level of evidence that reflect evolving practice trends.
Results:
Compression may correct local reflux, arguably improve calf hemodynamics, and control some end manifestations of CVD. Its efficacy varies widely because there is a large variability in the actual compression delivered by different products and individual bandaging techniques. Approximately 50% of ulcers recur with compression alone when it is used long term. Noncompliance with stocking use is a major issue that ranges >50% in some reports. EVA has no such compliance issues, and there is little aftercare required. EVA reduces long-term recurrence and may shorten healing time in wounds that are slow to heal with compression alone. Failure of compression can be detected as early as 2 to 6 weeks by monitoring ulcer healing metrics. Endovenous interventions yield durable clinical results in a large subset of patients in whom compression failed or could not be used. Initial costs of interventions are higher than those of compression, but long-term direct and indirect costs are likely to be substantially lower.
Conclusions:
Compression is the appropriate initial treatment in symptomatic CVD patients, even those with ulcer. The main concern at this time is ulcer care and quick control of symptoms. However, compression is not a long-term solution, particularly in venous leg ulcers as the majority of ulcers will recur without interventional correction. The option of interventional correction should be offered early, preferably concurrently with start of compression, as delay allows progression of disease, prompts recurrence, and increases overall costs. Persisting with compression alone fruitlessly for months or years does not seem justified, given the efficacy and the minimally invasive nature of newer treatments. A treatment paradigm that emphasizes intervention side by side with compression in symptomatic CVD patients at the outset should be considered.
Related Concept Videos
 01:29
Venous Thrombosis III: Interprofessional Care
 01:30
Venous Thrombosis IV: Nursing Management
 01:26
Varicose Veins II: Diagnostic Studies and Interprofessional Care
 01:23
Peripheral Artery Disease V: Postoperative Nursing Management
 01:20
Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies
 01:26
Cardiac Catheterization IV: Nursing Management