Related Experiment Video
Updated: Mar 19, 2026
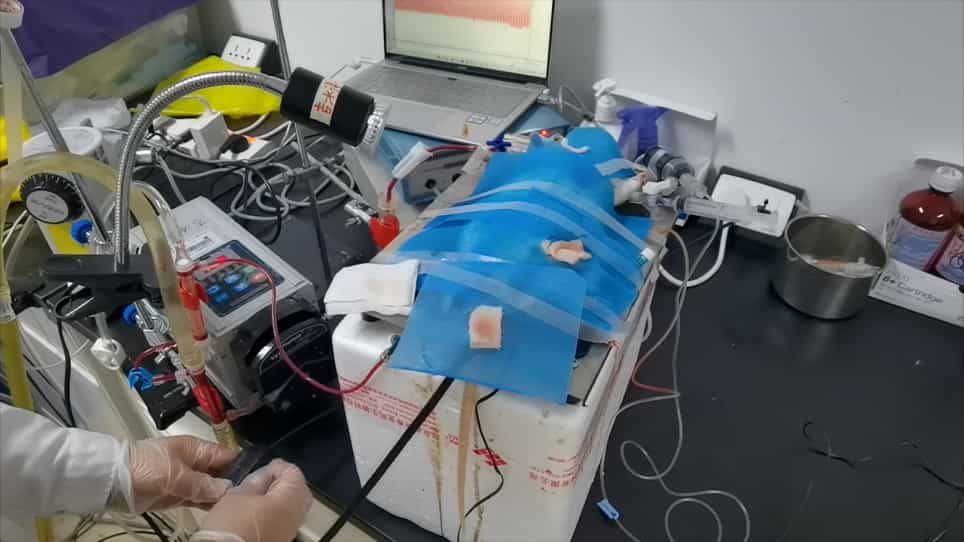

Establishment of Deep Hypothermic Circulatory Arrest in Rats
Published on: December 16, 2022
The Impact of Deep Versus Moderate Hypothermia on Postoperative Kidney Function After Elective Aortic Hemiarch Repair
George J Arnaoutakis1, Prashanth Vallabhajosyula1, Joseph E Bavaria1
1Division of Cardiovascular Surgery, University of Pennsylvania, Philadelphia, Pennsylvania.

Background:
There remains concern that moderate hypothermic circulatory arrest (MHCA) with antegrade cerebral perfusion (ACP) may provide suboptimal distal organ protection compared with deep hypothermic circulatory arrest (DHCA) with retrograde cerebral perfusion (RCP). We compared postoperative acute kidney injury (AKI) in in patients who underwent elective hemiarch repair with either DHCA/RCP or MHCA/ACP.
Methods:
This was a retrospective review of all patients undergoing elective aortic hemiarch reconstruction for aneurysmal disease between 2009 and 2014. Patients were stratified according to the use of DHCA/RCP versus MHCA/ACP. The primary outcome was the occurrence of AKI at 48 hours, as defined by the Risk, Injury, Failure, Loss, End-Stage (RIFLE ) criteria. A multivariable logistic regression identified risk factors for AKI.
Results:
One hundred eighteen patients who underwent ACP and 471 patients who underwent RCP were included. The mean lowest temperature was 26.4°C in patients who underwent MHCA/ACP and 17.5°C in patients who underwent DHCA/RCP. Baseline demographics were similar except that patients who underwent DHCA/RCP were more likely to have peripheral arterial disease or bicuspid aortic valves. Cardiopulmonary bypass and aortic cross-clamp times were shorter in the MHCA/ACP group. AKI occurred in 19 (16.2%) patients who underwent MHCA/ACP and 67 (14.3%) patients who underwent DHCA/RCP. Four (0.8%) patients who underwent DHCA/RCP required postoperative dialysis. In-hospital mortality tended to increase with increasing RIFLE classification (RIFLE class-0 (No AKI) = 0.41%; Risk = 1.35%, and Injury = 10.0%; p = 0.09). On multivariable analysis, the lowest temperature and cerebral perfusion strategy were not significant predictors of AKI. Lower baseline glomerular filtration rate (GFR), lower preoperative ejection fraction, and longer cardiopulmonary bypass (CPB) time were independently associated with higher AKI.
Conclusions:
We applied the sensitive RIFLE criteria to examine AKI in patients undergoing elective aortic hemiarch replacement for aneurysmal disease. Baseline renal dysfunction, lower ejection fraction, and longer CPB time are independent predictors of AKI. Compared with DHCA/RCP, our data suggest that an MHCA/ACP cerebral protection strategy does not appear to be associated with worse postoperative renal outcomes.
More Related Videos
 08:22
In vitro Assessment of Myocardial Protection following Hypothermia-Preconditioning in a Human Cardiac Myocytes Model
Published on: October 27, 2020
 03:13
Technical Refinement of a Bilateral Renal Ischemia-Reperfusion Mouse Model for Acute Kidney Injury Research
Published on: November 3, 2023
Related Concept Videos
 01:22
Aneurysm IV: Nursing Management
 01:28
Cardiac Catheterization I: Pre-Procedure Overview
 01:26
Kidney Transplant II: Surgical Procedure
 01:23
Peripheral Artery Disease V: Postoperative Nursing Management