Related Experiment Video
Updated: Mar 19, 2026
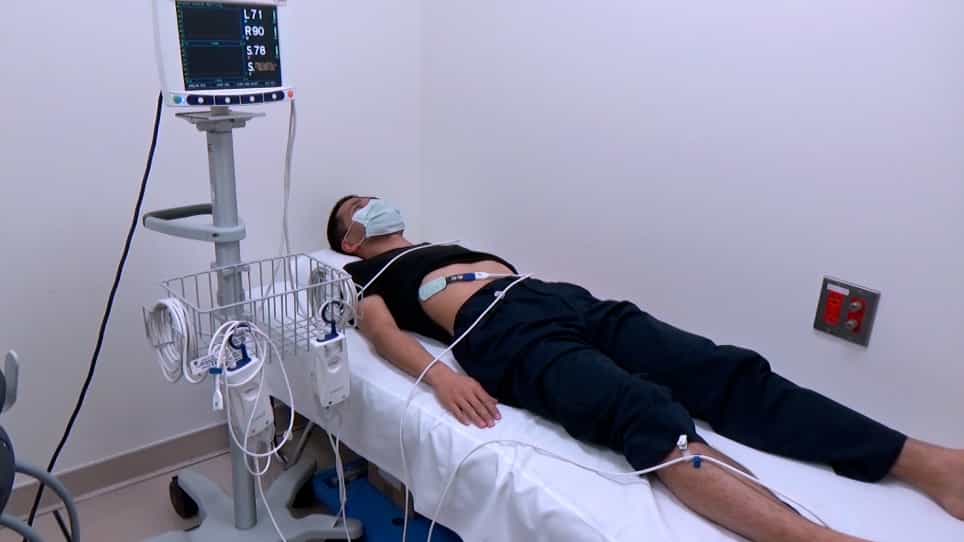

Measurement of Tissue Oxygenation Using Near-Infrared Spectroscopy in Patients Undergoing Hemodialysis
Published on: October 2, 2020
Nutritional Status in Nocturnal Hemodialysis Patients - A Systematic Review with Meta-Analysis
Karin J R Ipema1,2, Simone Struijk2, Annet van der Velden2
1Dialysis Center Groningen, Groningen, The Netherlands.

Background:
Hemodialysis patients experience an elevated risk of malnutrition associated with increased morbidity and mortality. Nocturnal hemodialysis (NHD) results in more effective removal of waste products and fluids. Therefore, diet and fluid restrictions are less restricted in NHD patients. However, it is ambiguous whether transition from conventional hemodialysis (CHD) to NHD leads to improved intake and nutritional status. We studied the effect of NHD on protein intake, laboratory indices of nutritional status, and body composition.
Study Design:
Systematic review with meta-analysis.
Population:
NHD patients.
Search Strategy:
Systematic literature search from databases, Medline, Cinahl, EMBASE and The Cochrane Library, to identify studies reporting on nutritional status post-transition from CHD to NHD.
Intervention:
Transition from CHD to NHD.
Outcomes:
Albumin, normalized protein catabolic rate (nPCR), dry body weight (DBW), body mass index (BMI), phase angle, protein intake, and energy intake.
Results:
Systematic literature search revealed 13 studies comprising 282 patients that made the transition from CHD to NHD. Meta-analysis included nine studies in 229 patients. In control group controlled studies (n = 4), serum albumin increased significantly from baseline to 4-6 months in NHD patients compared with patients that remained on CHD (mean difference 1.3 g/l, 95% CI 0.02; 2.58, p = 0.05). In baseline controlled studies, from baseline to 4-6 months of NHD treatment, significant increases were ascertained in serum albumin (mean difference (MD) 1.63 g/l, 95% CI 0.73-2.53, p<0.001); nPCR (MD 0.16 g/kg/day; 95% CI 0.04-0.29, p = 0.01); protein intake (MD 18.9 g, 95% CI 9.7-28.2, p<0.001); and energy intake (MD 183.2 kcal, 95% CI 16.8-349.7, p = 0.03). Homogeneity was rejected only for nPCR (baseline versus 4-6 months). DBW, BMI, and phase angle did not significantly change. Similar results were obtained for comparison between baseline and 8-12 months of NHD treatment.
Limitations:
Most studies had moderate sample sizes; some had incomplete dietary records and relatively brief follow-up period. Studies markedly differed with regard to study design.
Conclusions:
NHD is associated with significantly higher protein and energy intake as well as increases in serum albumin and nPCR. However, the data on body composition are inconclusive.
Related Concept Videos
 01:25
Hemodialysis III: Nursing Management
 01:28
Chronic Kidney Disease III: Interprofessional Care
 01:25
Peritoneal Dialysis III: Nursing Management
 01:18
Chronic Kidney Disease IV: Nursing Management
 01:22
Heart Failure VI: Adjunct Therapies
 01:24
Nephrotic Syndrome III : Nursing Management