Related Experiment Video
Updated: Mar 19, 2026
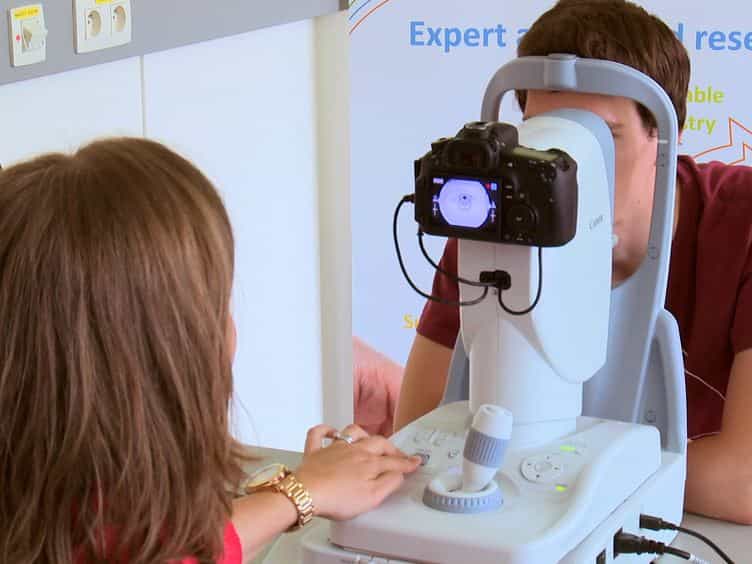

Fundus Photography as a Convenient Tool to Study Microvascular Responses to Cardiovascular Disease Risk Factors in Epidemiological Studies
Published on: October 22, 2014
Conventional and Ambulatory Blood Pressure as Predictors of Retinal Arteriolar Narrowing
Fang-Fei Wei1, Zhen-Yu Zhang1, Lutgarde Thijs1
1From the Studies Coordinating Centre, Research Unit Hypertension and Cardiovascular Epidemiology, KU Leuven Department of Cardiovascular Sciences (F.-F.W., Z.-Y.Z, L.T., W.-Y.Y, L.J., N.C., Y.-M.G., T.K., J.A.S.), Department of Development and Regeneration (K.A.), Centre for Molecular and Vascular Biology, KU Leuven Department of Cardiovascular Sciences (P.V.), University of Leuven, Leuven, Belgium; Center for Epidemiological Studies and Clinical Trials and Center for Vascular Evaluations, Shanghai Institute of Hypertension, Shanghai Key Laboratory of Hypertension, Ruijin Hospital, Shanghai Jiaotong University School of Medicine, Shanghai, China (Y.L.); and Department of Pharmacology (H.A.J.S.-B.) and R&D Group VitaK (J.A.S.), Maastricht University, Maastricht, The Netherlands.

Abstract:
At variance with the long established paradigm that retinal arteriolar narrowing trails hypertension, several longitudinal studies, all based on conventional blood pressure (CBP) measurement, proposed that retinal arteriolar narrowing indicates heightened microvascular resistance and precedes hypertension. In 783 randomly recruited Flemish (mean age, 38.2 years; 51.3% women), we investigated to what extent CBP and daytime (10 am to 8 pm) ambulatory blood pressure (ABP) measured at baseline (1989-2008) predicted the central retinal arteriolar equivalent (CRAE) in retinal photographs obtained at follow-up (2008-2015). Systolic/diastolic hypertension thresholds were 140/90 mm Hg for CBP and 135/85 mm Hg for ABP. In multivariable-adjusted models including both baseline CBP and ABP, CRAE after 10.3 years (median) of follow-up was unrelated to CBP (P≥0.14), whereas ABP predicted CRAE narrowing (P≤0.011). Per 1-SD increment in systolic/diastolic blood pressure, the association sizes were -0.95 µm (95% confidence interval, -2.20 to 0.30)/-0.75 µm (-1.93 to 0.42) for CBP and -1.76 µm (-2.95 to -0.58)/-1.48 µm (-2.61 to -0.34) for ABP. Patients with ambulatory hypertension at baseline (17.0%) had smaller CRAE (146.5 versus 152.6 µm; P<0.001) at follow-up. CRAE was not different (P≥0.31) between true normotension (normal CBP and ABP; prevalence, 77.6%) and white-coat hypertension (elevated CBP and normal ABP, 5.4%) and between masked hypertension (normal CBP and elevated ABP, 10.2%) and hypertension (elevated CBP and ABP, 6.8%). In conclusion, the paradigm that retinal arteriolar narrowing precedes hypertension can be explained by the limitations of CBP measurement, including nonidentification of masked and white-coat hypertension.

Related Concept Videos
 01:10
Pre-Procedural Guidelines for Assessing Blood Pressure
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation
 01:21
Sites for measuring blood pressure
The Brachial Artery: Primary Site for Blood Pressure Measurement
 01:30
Hypertension III: Clinical Manifestations and Diagnostic Studies
 01:18
Hypertension and Regulation of Blood Pressure
 01:28
Special considerations while measuring blood pressure
Monitoring Both Arms:
Monitoring BP in both arms during the initial assessment is advisable, as the systolic value may differ by five to ten mm Hg between arms. For subsequent BP assessments, use the arm with the higher reading.