Could acupuncture be an adequate alternative to dexamethasone in pediatric tonsillectomy?
Related Experiment Video
Updated: Mar 19, 2026
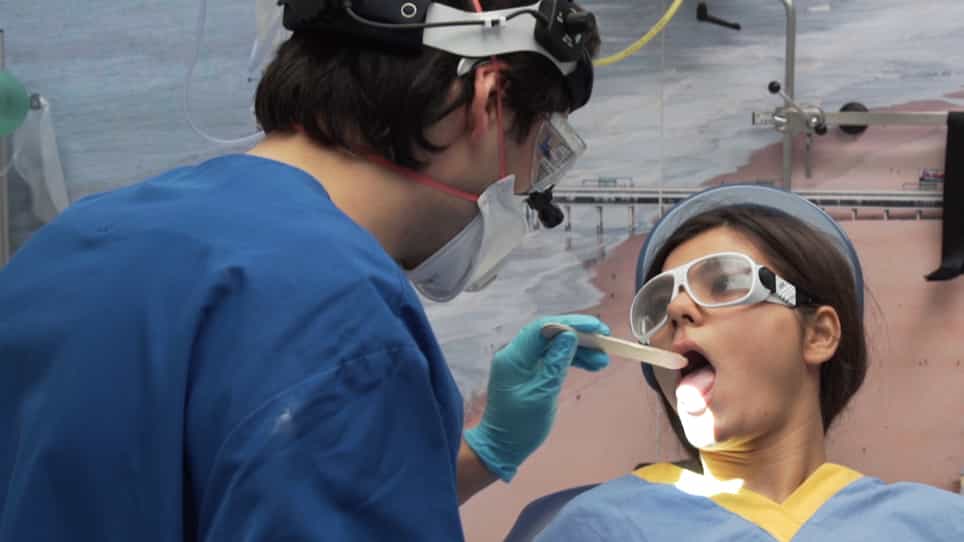
CO2-Lasertonsillotomy Under Local Anesthesia in Adults
Published on: November 6, 2019
1Anesthesia and Intensive Care Department, Faculty of Medicine, Assiut University, Asyut, Egypt.

Background:
Usage of nonpharmacological treatment contributes to an overall patient well-being, assisting in physical and emotional healing. Acupuncture has been reported to be useful in reducing early postoperative vomiting (POV) and attenuating postoperative pain.
Aim:
The aim of this study was to compare the effect of dexamethasone vs acupuncture at P6 bilaterally and CV13 on the incidence and severity of POV in children undergoing tonsillectomy with or without adenoidectomy.
Method:
One hundred and twenty children, ASA I-III aged 2-8 years undergoing elective tonsillectomy were included in this prospective randomized double-blind study. Children were randomly divided into two equal groups (60 each). At induction of anesthesia, the dexamethasone group received 0.15 mg·kg(-1) dexamethasone IV plus sham acupuncture, and the acupuncture group received acupuncture at P6 bilaterally and CV13 plus 2 ml of normal saline IV. Vomiting was recorded at 0-6, 6-24, and 0-24 h postoperatively.
Results:
There was no difference in the incidence of vomiting between the acupuncture and dexamethasone groups. The mean difference in time to first oral intake (95% CI) was 4.3 (0.5-8.6) min between dexamethasone group and acupuncture group; P = 0.426. The mean difference in time until first vomit (95% CI) was 12 (9.5-13.8) min between both groups. No significant differences between Kaplan-Meier curves for time until first vomit (log-rank test) were obtained (P = 0.697).
Conclusion:
Acupuncture at P6 bilaterally and CV13 provided similar antiemetic effect to dexamethasone in children undergoing tonsillectomy.


Related Concept Videos
 01:26
Tonsillitis II: Management
 01:31
Skeletal Muscle Relaxants: Therapeutic Uses
 01:23
Chronic Pharyngitis
Etiology
It often arises from persistent viral or bacterial infections affecting sinuses and tonsils.
Additional contributing factors include inadequate dental hygiene, mouth breathing, recurring tonsillitis, allergic rhinitis, laryngopharyngeal reflux, and exposure to smoke, chemicals, and other environmental pollutants. Allergic reactions to pollen, mold, and pet dander, chronic cough, excessive voice usage,...