Related Experiment Video
Updated: Aug 14, 2026

Endaural Endoscopic Atticoantrotomy (Retrograde Mastoidectomy) using a Constant Suction Bone-drilling Technique
Published on: May 23, 2021
Malignant external otitis and osteomyelitis of the base of the skull
1Department of Otolaryngology, University of Miami School of Medicine, Florida.

Abstract:
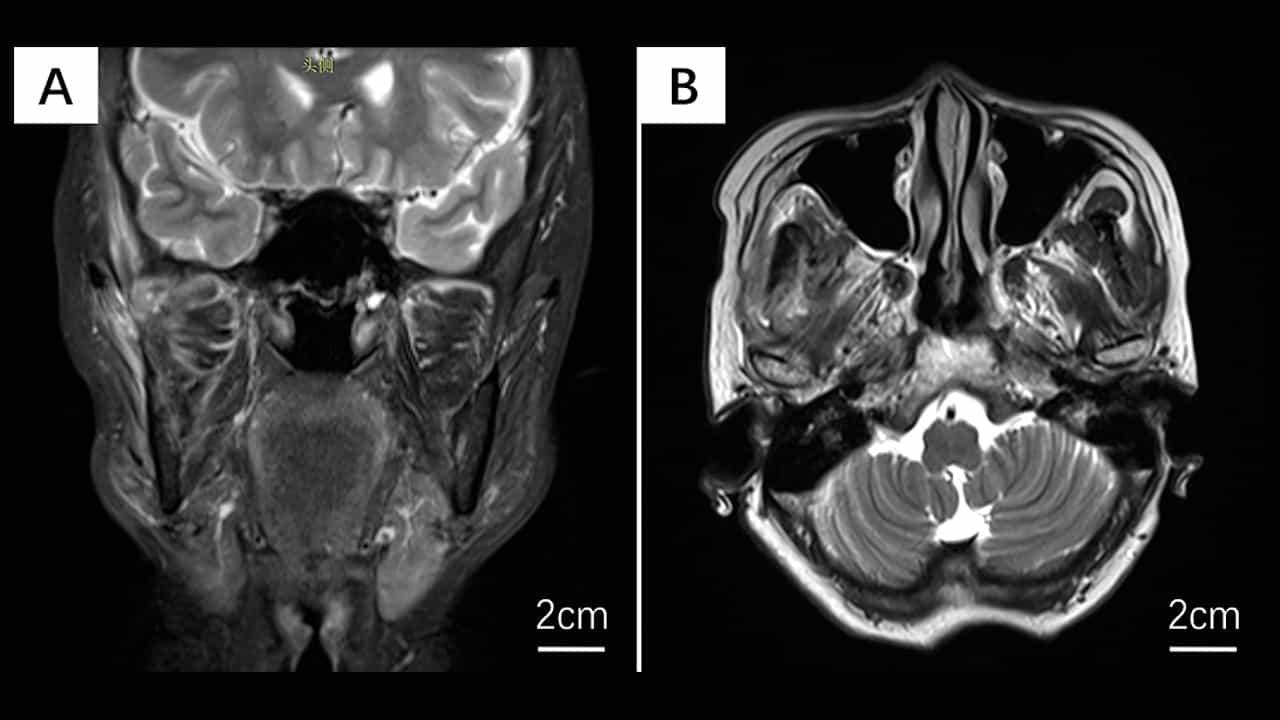
If malignant external otitis is not treated properly and until all evidence of infection has disappeared, it is likely to recur either in the external auditory canal and/or in the bone marrow at the base of the skull. Unremitting headache is the only early symptom of the latter and may occur in the absence of any signs of local ear disease. A conductive hearing loss is the most common additional symptom and is caused by fluid in the middle ear. If not diagnosed and treated adequately and properly, the infectious process in the bone marrow involves the soft tissues at the skull base and results in a progressive paralysis of the lower cranial nerves. Treatment must be vigorous and continuous until the gallium scan is normal or shows great improvement (i.e., for a minimum period of 2 months). Intravenous antibiotics with a proven record of success and effectiveness against this organism are recommended, although newer antimicrobial agents give promise of being effective when administered orally.
Insights
Malignant external otitis can recur if not fully treated, potentially causing skull base infections. Early symptoms include persistent headache and hearing loss, requiring aggressive antibiotic therapy for at least two months.
Area of Science:
- Otolaryngology
- Infectious Diseases
- Neurology
Background:
- Malignant external otitis (MEO) can recur if treatment is incomplete.
- Recurrence may involve the skull base, presenting with subtle early symptoms.
Purpose of the Study:
- To highlight the importance of complete treatment for MEO.
- To describe the potential complications and early signs of skull base involvement.
Main Methods:
- Clinical observation and case review of MEO patients.
- Emphasis on diagnostic indicators like headache and conductive hearing loss.
Main Results:
- Incomplete MEO treatment leads to recurrence in the ear canal or skull base.
- Skull base involvement may manifest as unremitting headache and progressive lower cranial nerve paralysis.
- Conductive hearing loss due to middle ear fluid is a common symptom.
Conclusions:
- Vigorous and continuous treatment is essential for MEO, aiming for resolution confirmed by gallium scans.
- Treatment duration should be a minimum of two months with intravenous antibiotics.
- Oral antimicrobial agents show promise for future treatment protocols.
Related Concept Videos
 01:14
Cranial Bones: Superior and Posterior View
The frontal bone is the single bone that forms the forehead. At its anterior midline, between the eyebrows, there is a slight depression called the glabella. The frontal bone also forms the supraorbital margin of the orbit. Near the middle of this margin is the supraorbital foramen, the opening that provides passage for a sensory nerve to the forehead. The frontal bone is thickened just above each supraorbital margin,...
 01:27
Cranial Bones: Lateral View
The temporal bone forms the lower lateral side of the skull. The temporal bone is subdivided into several regions. The flattened upper portion is the squamous portion of the temporal bone. Below this area and projecting anteriorly is the zygomatic process of the temporal bone, which forms the posterior portion of the zygomatic arch. Posteriorly is the mastoid portion of the temporal bone. Projecting...
 01:27
Cryptococcal Meningitis
 01:22
Bacterial Meningitis I: Introduction
 01:26
Bacterial Meningitis II: Pathophysiology
 01:26
Brain Abscess l: Introduction