Related Experiment Video
Updated: Mar 18, 2026
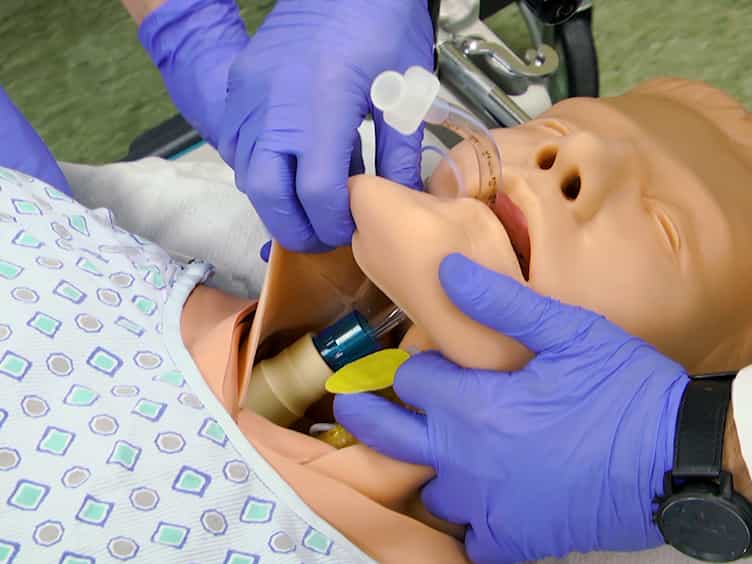
Mechanical Ventilation Boot Camp Curriculum
Published on: March 12, 2018
Retrospective Analysis of an Interdisciplinary Ventilator Care Program Intervention on Survival of Infants with
Jason Gien1, John Kinsella1, Jodi Thrasher2
1Pediatric Heart Lung Center, Department of Pediatrics, University of Colorado School of Medicine, Aurora, Colorado.

Insights
An interdisciplinary ventilator care program (VCP) significantly improved survival rates for infants with severe bronchopulmonary dysplasia (BPD) requiring mechanical ventilation. This standardized approach enhanced care and communication, leading to better outcomes.
Area of Science:
- Neonatology
- Pediatric Pulmonology
- Critical Care Medicine
Background:
- Infants with severe bronchopulmonary dysplasia (BPD) requiring mechanical ventilation present complex clinical challenges.
- Management strategies for optimizing survival and long-term outcomes in this population remain controversial.
- An interdisciplinary ventilator care program (VCP) was hypothesized to improve survival through standardized care and enhanced communication.
Purpose of the Study:
- To evaluate the impact of an interdisciplinary VCP on survival rates in ventilator-dependent infants with severe BPD.
- To assess changes in management strategies and comorbidities before and after VCP implementation.
- To determine if a standardized approach improves outcomes for critically ill infants.
Main Methods:
- Retrospective chart review of infants undergoing tracheostomy between 2000 and 2013 at Children's Hospital Colorado.
- Data collected included gestational age, age at tracheostomy, respiratory severity score (RSS), comorbidities, medication use, and age of death.
- Patients were divided into two periods: before (2000-2005) and after (2006-2013) VCP initiation; severe BPD patients without tracheostomy were excluded.
Main Results:
- Survival to discharge significantly increased from 50% to 85% after VCP implementation (p < 0.05).
- No significant differences were observed in gestational age, birth weight, or cardiorespiratory comorbidities between the two periods.
- Changes in systemic/inhaled steroid use and mucolytic use were noted between the study periods.
Conclusions:
- An interdisciplinary approach to ventilator care for infants with severe BPD can significantly improve survival rates.
- Standardized care protocols and enhanced communication within a VCP are crucial for managing this complex patient population.
- The findings support the implementation of specialized, multidisciplinary programs for ventilator-dependent infants with BPD.
Abstract:
Background The clinical needs of infants with severe bronchopulmonary dysplasia (BPD) that remain ventilator-dependent are complex, and management strategies that optimize survival and long-term outcomes controversial. We hypothesized that an interdisciplinary ventilator care program (VCP), committed to the care of this population will improve survival through standardized approaches to cardiopulmonary care and related comorbidities, enhanced communication, and continuity of care. Methods Retrospective chart reviews were performed on patients at Children's Hospital Colorado's neonatal intensive care unit, who underwent tracheostomy placement between 2000 and 2013. Data were collected for two time periods: 2000 to 2005 and 2006 to 2013, before and after initiation of the VCP. Collected data on infants with ventilator-dependent BPD included: gestational age (GA), age at tracheostomy, respiratory severity score (RSS; mean airway pressure [MAP] × fraction of inspired oxygen [FiO2]), comorbidities, medication use, and the age of death. Tracheostomy patients without severe BPD were excluded. Results Despite no difference in GA, birth weight, or cardiorespiratory comorbidities, survival to discharge increased from 50 to 85% after implementation of the VCP (p < 0.05). Between period 1 and 2, there were differences in systemic and inhaled steroid use and mucolytic use. Conclusion These findings suggest an interdisciplinary approach to the care of infants with ventilator-dependent BPD can improve survival.
More Related Videos


Related Concept Videos
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation...
 01:30
Acute Respiratory Failure-III
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...
 01:29
Acute Respiratory Failure-V
Ensure that patients are monitored continuously for their response to therapy, including changes in...