Related Experiment Video
Updated: Mar 18, 2026
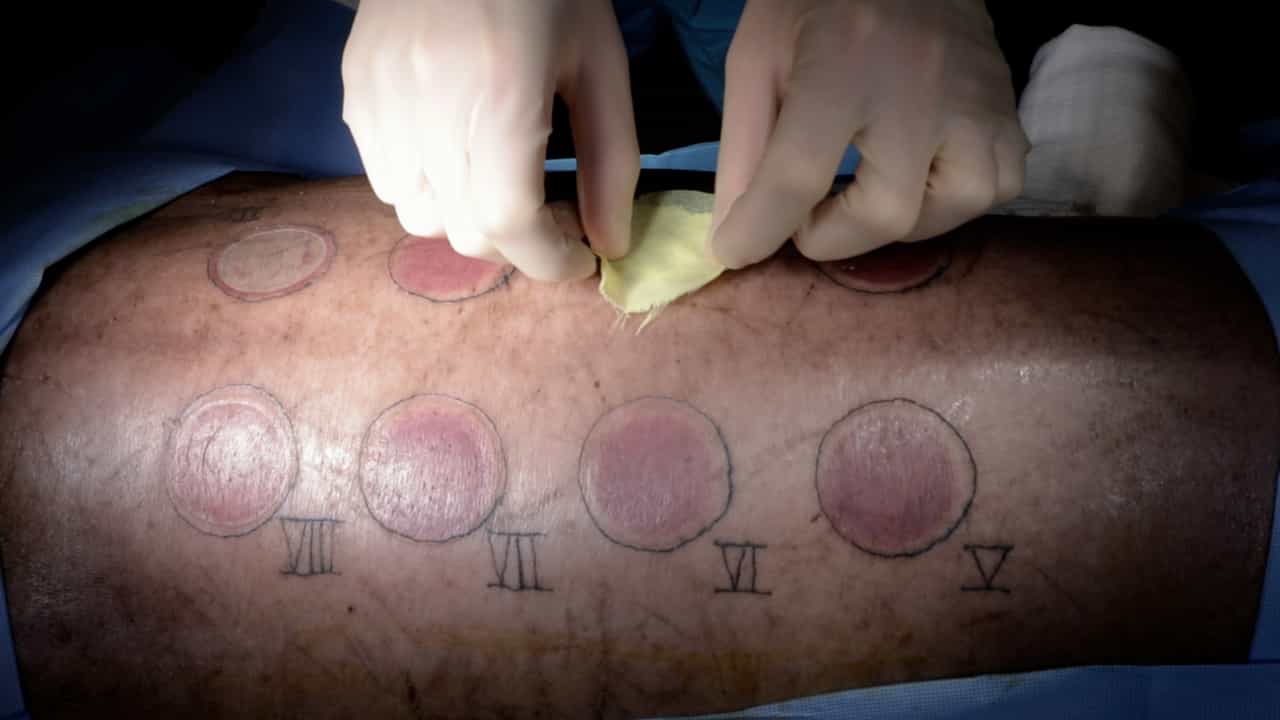

Author Spotlight: A Multi-Depth Porcine Model for Comprehensive Study of Burn Injuries and Healing Processes
Published on: February 23, 2024
Does Overestimation of Burn Size in Children Requiring Fluid Resuscitation Cause Any Harm?
Hazim Sadideen1, Federica D'Asta, Naiem Moiemen
1From the Healing Foundation Burns Research Centre, Birmingham Children's Hospital and University Hospitals Birmingham NHS Foundation Trust, Birmingham, United Kingdom.

Insights
Overestimating pediatric burn size is common but rarely causes harm. While overestimation led to more fluid prescriptions, actual fluid administration was often inadequate, with no significant adverse events observed in children transferred to a burns center.
Area of Science:
- Pediatric Emergency Medicine
- Burn Care
- Clinical Assessment
Background:
- Accurate estimation of Total Body Surface Area (TBSA) burns in children is critical for appropriate fluid resuscitation.
- Overestimation of burn size is frequently observed in pediatric cases, raising concerns about potential harm from over-resuscitation.
Purpose of the Study:
- To evaluate the accuracy of burn size estimations by non-specialist clinicians in pediatric patients.
- To determine if inaccurate burn size estimations, particularly overestimations, lead to adverse clinical outcomes or harm.
Main Methods:
- Retrospective review of 46 pediatric patients with resuscitation burns (≥10% TBSA) transferred to a tertiary burns center over 3.5 years.
- Analysis of initial TBSA estimations, prescribed fluid volumes, actual burn TBSA, fluids administered, and clinical parameters at 8 and 24 hours post-injury.
Main Results:
- 70% of pediatric burns were overestimated, 15% underestimated, and 15% accurately estimated.
- Only 11% of patients received more fluids than required, and these were within the overestimated group; however, most patients received inadequate fluids.
- No mortalities or significant clinical adverse events were recorded, regardless of estimation accuracy.
Conclusions:
- Overestimation of pediatric burn size by referring clinicians is common but does not appear to cause significant harm due to over-resuscitation.
- Despite inaccurate estimations, early transfer to a specialist burns service is crucial for optimal management and preventing potential complications.
Abstract:
Overestimation of burn size especially in children is common. It is unclear if this may cause harm. This study was designed to assess the accuracy of burn size estimation by referring non-burn clinicians and investigate whether inaccurate estimates caused any harm. Three and a half years retrospective review of pediatric resuscitation burns (ie, ≥10% TBSA) referred to a tertiary burns center from other hospitals was performed. This included basic demographics, data from referring emergency departments (initial TBSA estimations and fluid volumes prescribed), and data on arrival to the burn center (actual burn TBSA sustained, fluid volumes given prior to arrival, and actual fluid volumes required). Clinical parameters at 8 and 24 hr after injury were also examined. Forty-six patients were identified. Mean age was 3.9 years and weight 18 kg. Mean time to arrival from initial burn injury to our tertiary center was 5 hr. Thirty-two children (70%) had their burns overestimated, seven (15%) underestimated, and another seven (15%) were correctly estimated. After accurate calculations of the burn size and the required resuscitation fluids on arrival to the burns center, only five children of the entire cohort of 46 patients (11%) had received more fluids than required. These five children were in the overestimated burn size group. Only three children received the appropriate amount of fluid prior to arrival to the burns center. There were no mortalities or significant clinical adverse events in any of the children. Overestimation led to overprescription of fluid volumes, but this did not translate into over-resuscitation, and in most cases was in fact associated with inadequate fluid administration. Although 70% of the children in our cohort had the burn size overestimated, only 11% had actually received more fluids than required before arrival. None of these children went on to have any significant complications as a result of overestimation. Training and education is essential for clinicians in emergency departments. However, estimation of size in pediatric burns, in particular scalds, is challenging and the importance of early transfer to a specialist service cannot be overemphasized.
More Related Videos
Related Concept Videos
 01:22
Burn Injuries
The damage results in the death of skin cells, which can lead to a massive loss of fluid. Dehydration, electrolyte imbalance, and renal and circulatory failure follow, which can be fatal. Burn patients are treated with intravenous fluids to offset...
 01:29
Drug Dosing: Infants and Children
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation:
 01:22
Acute Kidney Injury VI: Nursing Management
 01:29
Acute Respiratory Failure-V
Ensure that patients are monitored continuously for their response to therapy, including changes in...
 01:21
Cardiopulmonary Resuscitation I: Adult