Related Experiment Video For PCOS
Updated: Mar 18, 2026


Establishment of Rat Models Mimicking Gender-affirming Hormone Therapies
Published on: January 10, 2025
Androgen excess: Investigations and management
Daria Lizneva1, Larisa Gavrilova-Jordan2, Walidah Walker2
1Department of Obstetrics and Gynecology, Medical College of Georgia, Augusta State University, 1120 15th Street, 30912 Augusta, GA, USA; Medical Company IDK, ul. Entuziastov 29, 443067 Samara, Russian Federation; Department of Reproductive Health Protection, Scientific Center of Family Health and Human Reproduction, ul. Timiryazeva 16, 664003 Irkutsk, Russian Federation.

Abstract:
Androgen excess (AE) is a key feature of polycystic ovary syndrome (PCOS) and results in, or contributes to, the clinical phenotype of these patients. Although AE will contribute to the ovulatory and menstrual dysfunction of these patients, the most recognizable sign of AE includes hirsutism, acne, and androgenic alopecia or female pattern hair loss (FPHL). Evaluation includes not only scoring facial and body terminal hair growth using the modified Ferriman-Gallwey method but also recording and possibly scoring acne and alopecia. Moreover, assessment of biochemical hyperandrogenism is necessary, particularly in patients with unclear or absent hirsutism, and will include assessing total and free testosterone (T), and possibly dehydroepiandrosterone sulfate (DHEAS) and androstenedione, although these latter contribute limitedly to the diagnosis. Assessment of T requires use of the highest quality assays available, generally radioimmunoassays with extraction and chromatography or mass spectrometry preceded by liquid or gas chromatography. Management of clinical hyperandrogenism involves primarily either androgen suppression, with a hormonal combination contraceptive, or androgen blockade, as with an androgen receptor blocker or a 5α-reductase inhibitor, or a combination of the two. Medical treatment should be combined with cosmetic treatment including topical eflornithine hydrochloride and short-term (shaving, chemical depilation, plucking, threading, waxing, and bleaching) and long-term (electrolysis, laser therapy, and intense pulse light therapy) cosmetic treatments. Generally, acne responds to therapy relatively rapidly, whereas hirsutism is slower to respond, with improvements observed as early as 3 months, but routinely only after 6 or 8 months of therapy. Finally, FPHL is the slowest to respond to therapy, if it will at all, and it may take 12 to 18 months of therapy for an observable response.


Related Concept Videos
 01:27
Adrenal Gland Disorders
Adrenal insufficiency, characterized by insufficient cortisol and aldosterone production, leads to conditions like Addison's disease. This disorder, affecting the adrenal cortex, exhibits symptoms such as skin bronzing, dehydration, low blood pressure, fatigue, and weight loss. Congenital adrenal hyperplasia, a genetic ailment causing...
 01:20
Disorders of the Male Reproductive System
Prostate disorders are another major concern. These conditions can impair urinary flow due to the prostate's location around the urethra....
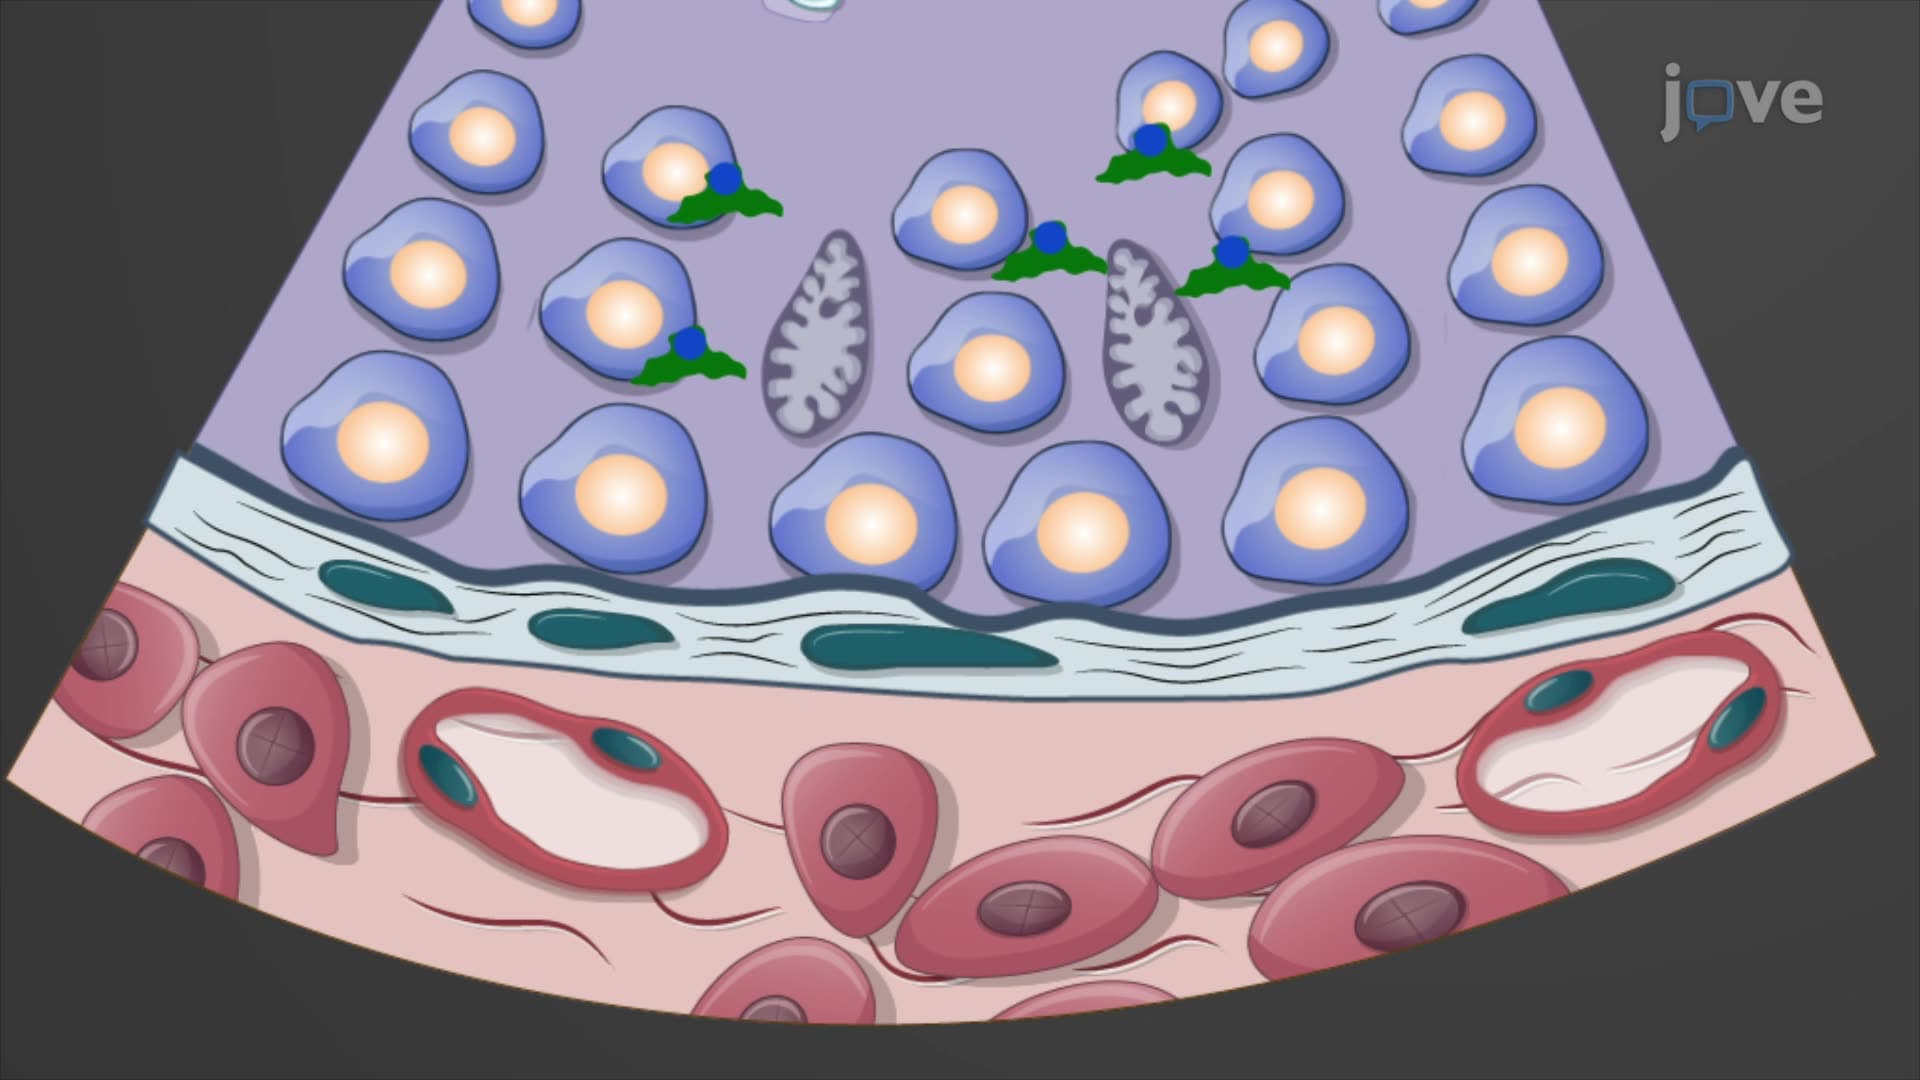 01:26
Testosterone: Functions and Regulation
 01:27
Major Hormones and Their Functions
Oxytocin, produced in the hypothalamus and released by the pituitary gland, plays a role in social bonding, childbirth, and...
 01:26
Nephrotic Syndrome II : Assessment and Medical Management
 01:27
Signs of Puberty