Metastatic right ventricular mass with intracavitary obliteration
Related Experiment Video
Updated: Mar 18, 2026
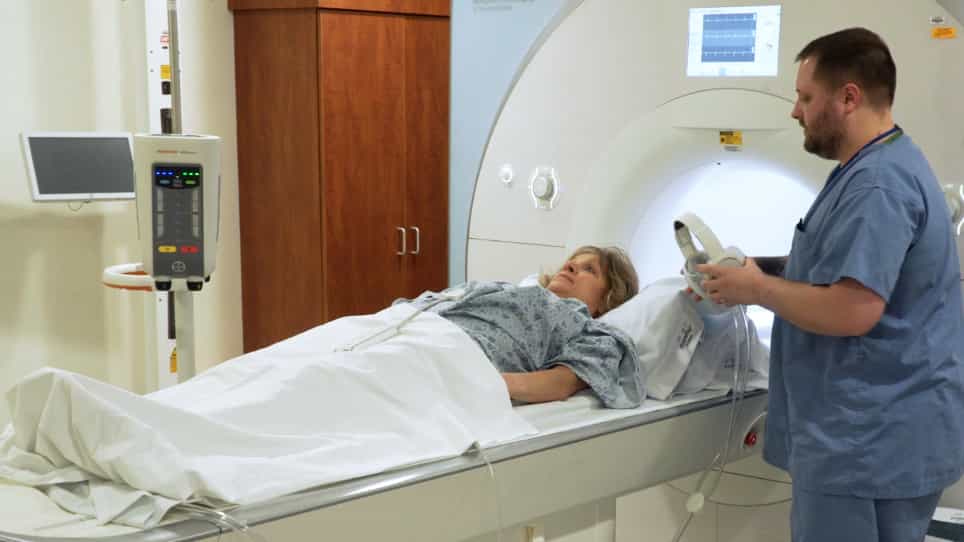
Cardiac Magnetic Resonance for the Evaluation of Suspected Cardiac Thrombus: Conventional and Emerging Techniques
Published on: June 11, 2019
Kavitha Kalvakuri1,2, Sandeep Banga1,3, Nalinee Upalakalin4
1Division of Cardiovascular Medicine, University of Illinois College of Medicine at Peoria, OSF Saint Francis Medical Center, Peoria, IL, USA.

Insights
Metastatic cervical cancer rarely spreads to the heart. This case highlights a large right ventricular tumor, initially misdiagnosed as pulmonary embolism, emphasizing the need for advanced imaging in complex cardiac cases.
Area of Science:
- Cardiology
- Oncology
- Radiology
Background:
- Metastatic cardiac tumors are more frequent than primary ones, with right-sided and intramural spread being common.
- Cervical cancer typically metastasizes to lungs, liver, bones, and lymph nodes, rarely to the heart.
Observation:
- A 49-year-old woman presented with chest pain and respiratory distress post-flight, initially diagnosed with pulmonary embolism.
- Despite heparin treatment, her condition did not improve, prompting further investigation.
Findings:
- Multimodality imaging, including echocardiography and CT, revealed a large right ventricular intracavitary mass.
- Biopsies confirmed metastatic squamous cell carcinoma originating from the cervix.
Implications:
- This case underscores the importance of considering metastatic disease in cardiac masses, especially when clinical presentation is atypical.
- Advanced imaging modalities are crucial for accurate diagnosis and management planning of cardiac tumors, differentiating them from thrombi.
- Early and accurate diagnosis of metastatic cardiac tumors can lead to timely and appropriate treatment strategies, improving patient outcomes.
Abstract:
Metastatic cardiac tumors are more common than the primary cardiac tumors. Cervical cancer metastasizing outside of the pelvis is commonly spread to the lungs, liver, bones and lymph nodes than to the heart. Right-sided metastasis to the heart is more common than to the left side. Intramural spread is more common than intracavitary growth of metastatic cardiac tumors leading to delayed clinical presentation. Intracavitary mass can be confused with intracavitary thrombus which can be seen in the setting of pulmonary embolism. Transthoracic echocardiography plays a major role in the decision making and management of pulmonary embolism, and this modality can also be used to diagnose cardiac masses. Other modalities like TEE, cardiac CT, cardiac MRI and PET-CT scan have further utility in delineating these masses. This may help to plan appropriate management of the right ventricular mass particularly in cases where the patient history and CT pulmonary angiography results favor the diagnosis of pulmonary embolism. We present the case of a 49-year-old woman with a history of supracervical hysterectomy and salpingo-oophorectomy on oral estrogen therapy who was admitted with complaints of pleuritic chest pain and respiratory insufficiency after a long flight. Initial work-up showed sub-segmental pulmonary embolus in the right posterior lower lobe pulmonary artery, and the patient was managed on intravenous heparin. Lack of appropriate response to standard therapy led to further evaluation. Multimodality imaging and biopsies revealed a large right intracavitary ventricular metastatic squamous cell tumor, with the cervix as the primary source.
Related Concept Videos
 01:20
Mitral Regurgitation I: Introduction
 01:22
Mitral Stenosis I: Introduction
 01:23
Mitral Stenosis II: Clinical features and Diagnostic Tests
 01:29
Cardiomyopathy IV: Restrictive Cardiomyopathy
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 01:22
Aortic Regurgitation II: Clinical Features and Diagnostic Tests