Related Experiment Video
Updated: Mar 17, 2026


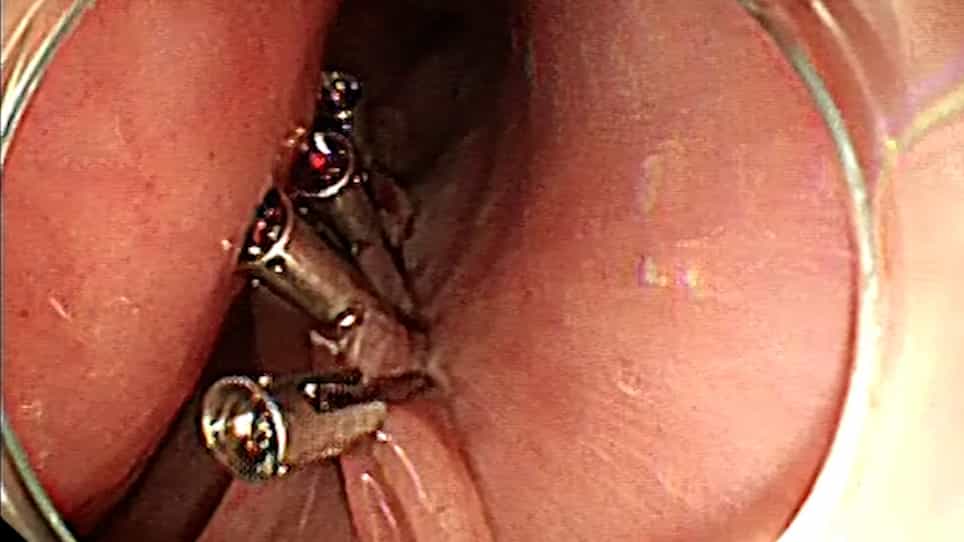
Robotic Myotomy and Partial Fundoplication for Achalasia
Published on: August 11, 2023
Achalasia: Outcome in children
Anell Meyer1,2, Anthony Catto-Smith1,3,4,5, Joe Crameri6
1Department of Gastroenterology and Clinical Nutrition, Australia.

Insights
Pediatric achalasia often requires multiple treatments, with many children experiencing symptom relapse and long-term quality of life impacts. Triple A syndrome variants present earlier but face delayed diagnosis and nutritional challenges.
Area of Science:
- Pediatric Gastroenterology
- Rare Diseases
- Surgical Outcomes
Background:
- Oesophageal achalasia is rare in children, sometimes presenting as "triple A" syndrome (adrenal insufficiency, alacrima).
- Current treatments are not curative, necessitating further interventions and ongoing research for improved management.
- The long-term outcomes for syndromic achalasia variants remain largely unknown.
Purpose of the Study:
- To evaluate the effectiveness of various treatments for pediatric achalasia.
- To compare outcomes between children with and without triple A syndrome.
- To assess the long-term impact of achalasia on children's quality of life.
Main Methods:
- Retrospective analysis of 42 pediatric achalasia cases over 30 years.
- Review of patient presentation, treatment interventions, and outcomes.
- Long-term quality of life assessment via questionnaires.
Main Results:
- Six of 42 children had triple A syndrome; they presented earlier but had delayed diagnosis and lower weight.
- Initial Heller myotomy required further interventions in 65%; 85% of botulinum toxin treatments eventually led to myotomy.
- 29% of patients undergoing myotomy needed repeat procedures, with persistent symptoms impacting quality of life.
Conclusions:
- Pediatric achalasia frequently relapses post-treatment, leading to multiple procedures and persistent symptoms.
- Triple A syndrome in children is associated with earlier symptom onset but delayed diagnosis and significant nutritional impact.
- Achalasia significantly affects the long-term quality of life for affected children and their families.
Background:
Oesophageal achalasia is well-recognized but relatively rare in children, occasionally appearing as the "triple A" syndrome (with adrenal insufficiency and alacrima). Treatment modalities, as in adult practice, are not curative, often needing further interventions and spurring the search for better management. The outcome for syndromic variants is unknown. We sought to define the efficacy of treatments for children with achalasia with and without triple A syndrome.
Methods:
We conducted a retrospective analysis of presentation and outcomes for 42 children with achalasia presenting over three decades to a major pediatric referral center. Long term impact of the diagnosis was assessed by questionnaire.
Results:
We identified 42 children including six with triple A syndrome. The median overall age at diagnosis was 10.8 years and median follow-up 1593 days. Initial Heller myotomy in 17 required further interventions in 11 (65%), while initial treatment with botulinum toxin (n = 20) was ultimately followed by myotomy in 17 (85%). Ten out of 35 patients who underwent myotomy required a repeat myotomy (29%). Patients with triple A syndrome developed symptoms earlier, but had delayed diagnosis, were more underweight at diagnosis and at last follow up. Questionnaire results suggested a significant long term deleterious impact on the quality of life of children and their families.
Conclusion:
Many children with achalasia relapse after initial treatment, undergoing multiple, different procedures, despite which symptoms persist and impact on quality of life. Symptoms develop earlier in patients with triple A syndrome, but the diagnosis is delayed and this has substantial nutritional impact.
Related Concept Videos
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure...
 01:20
Myasthenia Gravis: Overview and Treatment
These antibodies interfere with the function of the nicotinic receptors in three ways: by binding to the receptor and disrupting acetylcholine binding; by causing cross-linking of receptors which...
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol...