Related Experiment Video
Updated: Mar 17, 2026
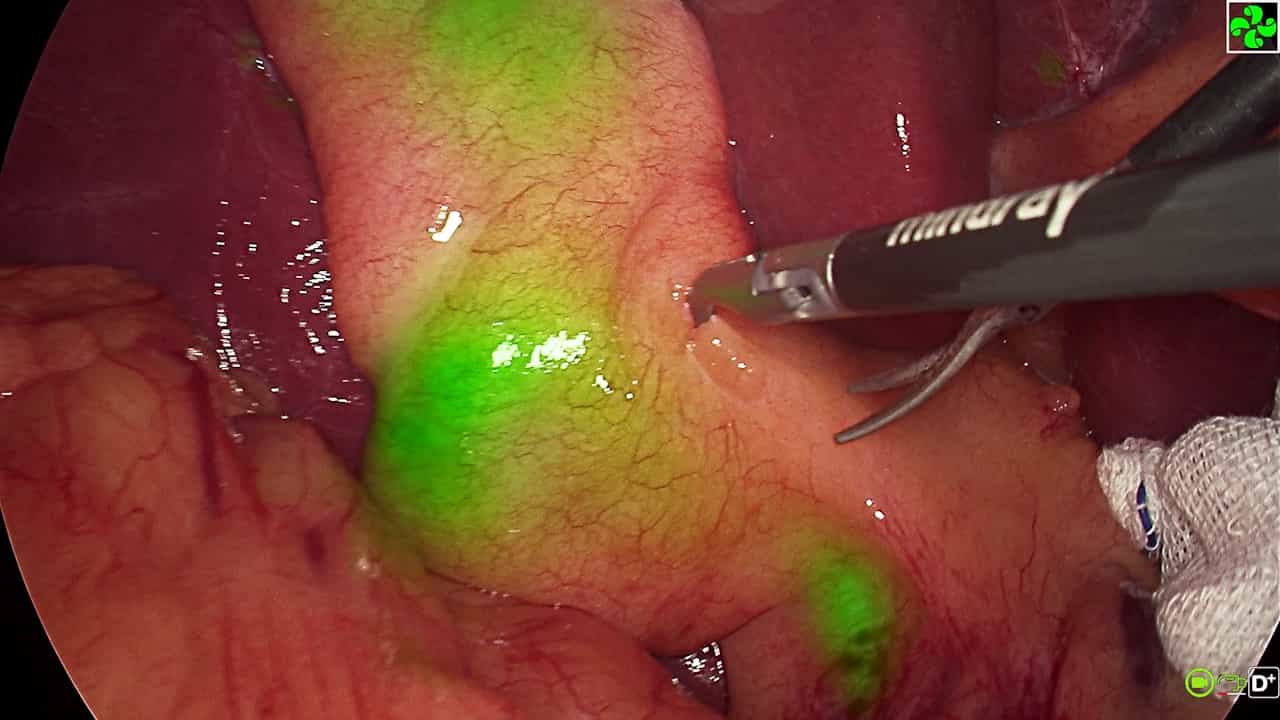

Laparoscopic Cholecystectomy with Indocyanine Green Fluorescence: Choledochoscopic Stone Extraction and Primary Duct Suture
Published on: November 25, 2025
Management of acute cholecystitis
Prabhava Bagla1, Juan C Sarria, Taylor S Riall
1aDivision of Infectious Diseases, Department of Internal Medicine, University of Texas Medical Branch, Galveston, Texas bDivision of General Surgery and Surgical Oncology, Department of Surgery, University of Arizona, Banner University Medical Center, Tucson, Arizona, USA.

Purpose Of Review:
Various aspects of the management of acute calculous cholecystitis, including type and timing of surgery, role of antibiotics, and nonoperative management, remain controversial. This review focuses on recently published studies addressing the timing of cholecystectomy, use of cholecystostomy tubes, and role of antibiotics in this condition.
Recent Findings:
In most cases, the diagnosis of acute cholecystitis can be initially confirmed with an abdominal ultrasound. Early laparoscopic cholecystectomy (within 24-72 h of symptom onset) is better than delayed surgery (>7 days) for most patients with grade I and II diseases. Percutaneous cholecystostomy and novel endoscopic gallbladder drainage interventions may be used as a temporizing measure or as definitive therapy in those who are too sick to undergo surgery. Studies are conflicting as to whether antibiotics are required for the treatment of uncomplicated cases.
Summary:
Cholecystectomy remains the only definitive therapy for acute cholecystitis. Current guidelines recommend treatment on the basis of disease severity at presentation. Antibiotics and a variety of minimally invasive nonsurgical interventions, although not definitive, play an adjunctive role in the management of the disease.
Related Concept Videos
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment:
 01:29
Appendicitis-II: Diagnostic Studies and Management
Diagnosing Appendicitis
It requires a multifaceted approach, starting with a detailed physical examination to pinpoint the location and nature of the pain and identify any associated symptoms. Laboratory tests play a crucial role. A complete Blood Count (CBC) typically reveals leukocytosis (an increased number of...
 01:23
Gastritis III: Clinical Manifestations and Management
Clinical manifestations of acute gastritis
The patient with acute gastritis may have a rapid onset of symptoms, such as epigastric pain or discomfort, dyspepsia, anorexia, hiccups, or nausea and vomiting, which can last from a few hours to a few days. Erosive or hemorrhagic gastritis may cause bleeding, which may manifest as blood in vomit or as...
 01:28
Acute Coronary Syndrome IV: Interprofessional Care
 01:17
Chronic Bowel Disorders: Introduction
Irritable Bowel Syndrome (IBS) is a common disorder affecting the gastrointestinal tract. The distinctive feature is recurrent abdominal pain associated with altered bowel movements, manifesting as constipation, diarrhea, or fluctuating between both. The...