Related Experiment Video
Updated: Mar 17, 2026
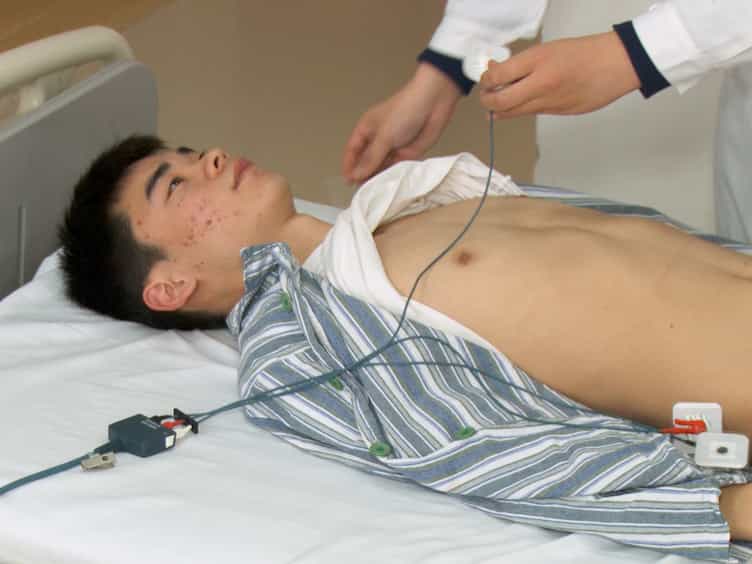

Measuring the Carotid to Femoral Pulse Wave Velocity Cf-PWV to Evaluate Arterial Stiffness
Published on: May 3, 2018
Carotid and Aortic Stiffness in Patients with Heterozygous Familial Hypercholesterolemia
Alexandra I Ershova1, Alexey N Meshkov1, Tatyana A Rozhkova2
1Department of clinical cardiology and molecular genetics, National Research Center for Preventive Medicine, Moscow, Russia.

Insights
Patients with familial hypercholesterolemia (FH) exhibit stiffer carotid arteries but not aortic stiffness compared to relatives. Arterial elasticity reduces earlier in the carotid arteries than the aorta in FH patients.
Area of Science:
- Cardiovascular Medicine
- Arterial Physiology
- Lipid Metabolism Disorders
Background:
- The impact of high plasma cholesterol on arterial health is not fully understood.
- Familial hypercholesterolemia (FH) presents an opportunity to study cholesterol's effects on arterial function.
- Arterial stiffness is a key indicator of cardiovascular health.
Purpose of the Study:
- To evaluate arterial stiffness in treatment-naive patients with heterozygous FH.
- To compare local carotid artery stiffness and aortic stiffness between FH patients and their relatives.
- To investigate the age-related changes in arterial elasticity in FH.
Main Methods:
- Utilized high-resolution echo-tracking for local common carotid artery stiffness assessment.
- Measured aortic stiffness using carotid-femoral pulse wave velocity (PWV).
- Included 66 FH patients and 57 non-FH relatives, assessing carotid stiffness parameters (β-index, Peterson elastic modulus, local PWV).
Main Results:
- FH patients demonstrated significantly higher carotid artery stiffness (β-index, Ep, local PWV).
- No significant difference in aortic stiffness (carotid-femoral PWV) was observed between FH patients and controls.
- Carotid arteries and aorta stiffened with age in FH patients, with more pronounced carotid stiffening after age 30.
Conclusions:
- Treatment-naive FH patients exhibit increased carotid artery stiffness compared to relatives.
- Aortic stiffness does not differ between FH patients and their relatives.
- The decline in arterial elasticity occurs earlier in the carotid arteries than in the aorta in individuals with FH.
Background:
The role of plasma cholesterol in impairing arterial function and elasticity remains unclear. We evaluated arterial stiffness, measured locally in the common carotid artery by high-resolution echo-tracking, and aortic stiffness, using carotid-femoral pulse wave velocity (PWV) (the "gold-standard" measurement of arterial stiffness), in treatment-naive patients with heterozygous familial hypercholesterolemia (FH).
Methods:
The study included 66 patients with FH (10-66 years old) and 57 first-degree relatives without FH (11-61 years old). Carotid-femoral PWV was determined by SphygmoCor (AtCor, Australia). The parameters of carotid stiffness β-index, Peterson elastic modulus and local PWV were assessed with regard to the common carotid artery at a distance of 1cm from the bifurcation (AlokaProsound Alpha7, Japan).
Results:
FH patients showed significantly higher β-index (6.3(4.8-8.2) vs. 5.2(4.2-6.4), p = 0.005), Ep (78(53-111) kPa vs. 62(48-79) kPa, p = 0.006), local PWV (5.4(4.5-6.4) m/c vs. 4.7(4.2-5.4) m/c, p = 0.005), but comparable values of carotid-femoral PWV (6.76(7.0-7.92) m/c vs. 6.48(6.16-7.12) m/c, p = 0.138). Carotid arteries and the aorta stiffened with age in patients with FH, but after 30 years, carotid arteries stiffened more significantly than the aorta.
Conclusions:
Our study demonstrated that treatment-naive patients with FH had stiffer carotid arteries than their relatives, but showed no difference in aortic stiffness. We also found out that the rate of reduction of elasticity of the aorta and carotid arteries in FH patients varies: it is observed earlier in carotid arteries than in the aorta.
Related Concept Videos
 01:27
Atherosclerosis II: Clinical Manifestations and Diagnostic Tests
 01:26
Atherosclerosis III: Management
 01:30
Atherosclerosis I: Introduction
 01:26
Coronary Artery Disease II: Pathophysiology
 01:23
Atherosclerosis IV: Nursing Management
 01:29
Cholesterol: Significance and Regulation
Considering cholesterol and...