Related Experiment Video
Updated: Mar 16, 2026
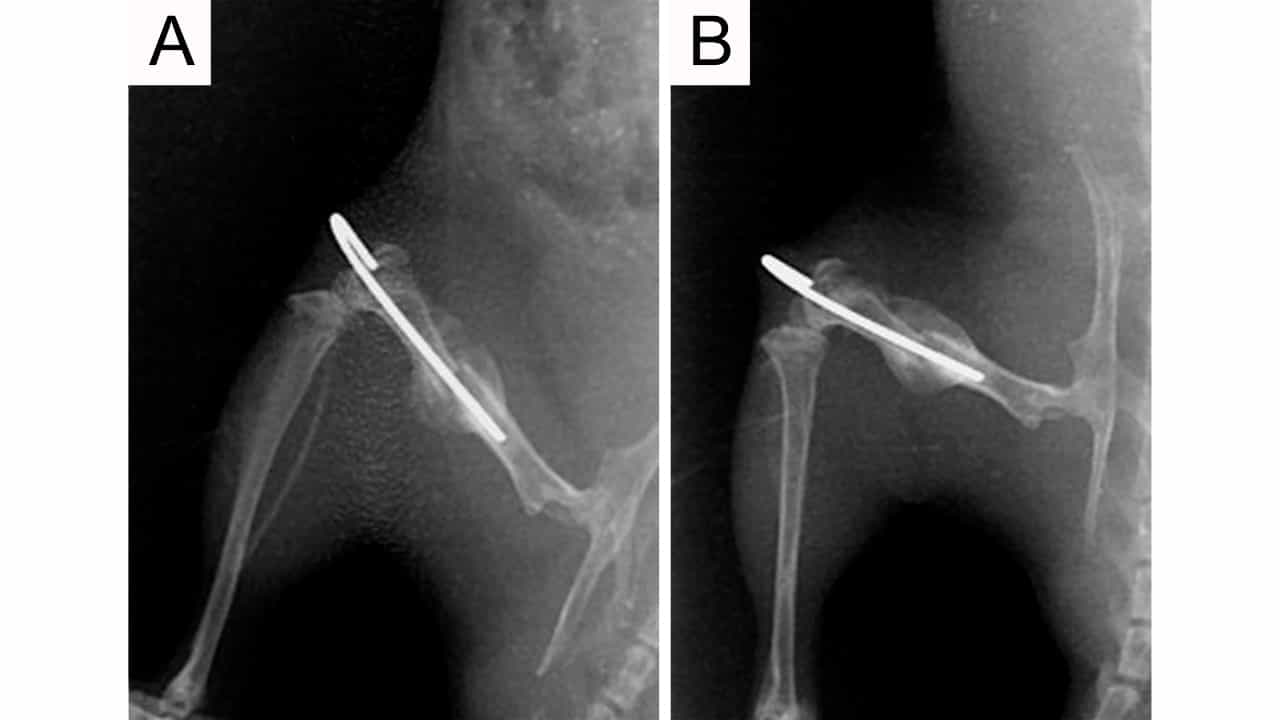

Establishing a Diaphyseal Femur Fracture Model in Mice
Published on: December 9, 2022
Biological Risk Factors for Nonunion of Bone Fracture
Robert Zura1, Samir Mehta2, Gregory J Della Rocca3
1Department of Orthopaedics, Louisiana State University Health Sciences Center, New Orleans, LA.

Abstract:
Many risk factors for fracture nonunion are well supported in the orthopaedic literature, including location of the fracture site, surgical treatment, bone displacement, type of fixation, treatment delay, comminution, inadequate treatment, and wound infection. However, evidence from a systematic review suggests that patient-related or biological causes of nonunion may not be as well understood. Understanding the biological causes of nonunion is important for several reasons. Risk factors might identify patients prone to nonunion who could benefit from more aggressive intervention, and a clear idea of nonunion risk could be important when choosing between competing therapeutic options. Risk factors also can inform the design of clinical trials and clarify patient inclusion and exclusion criteria, so that small studies can yield more definitive answers. Finally, an understanding of patient risk profiles may enable clinicians to counsel patients more effectively and to set appropriate expectations for success. Patient age appears to be a strong risk factor for nonunion in some bones, a weak risk factor for nonunion in other bones, and perhaps not a significant risk factor for nonunion in certain bones. This observation suggests that there can be substantial bone-to-bone variation in nonunion risk. Age also may be a surrogate for the prevalence of risk factors that potentially increase with age, such as smoking, diabetes, obesity, or nonsteroidal anti-inflammatory drug (NSAID) use. Smoking has been replicated as a risk factor for nonunion only in retrospective studies involving the humerus and tibia. Smoking appears to have an important effect on nonunion, yet the incremental risk may be rather small, except in context with additional risk factors. Diabetes has been confirmed as a risk factor for nonunion only in retrospective studies involving the foot and ankle. Nonunion risk from diabetes alone may be small and the context of additional risk factors crucial; this could account for why it has been so difficult to predict nonunion in the individual patient. Prediction of fracture nonunion in the individual patient is a difficult problem. Fracture nonunion may be influenced by complex interactions between biological and surgical risk factors, and the nonunion rate varies from bone to bone. A randomized clinical trial may not appropriately control for all potential correlates and confounders and may require impractical sample sizes. A large claims-based study of real-world fracture-healing outcomes is needed to provide guidance for randomized clinical trials that can test risk factors more rigorously.

Related Concept Videos
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the...
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...
 01:31
Bone Remodeling and Repair
 01:29
Blood and Nerve Supply to the Bones
Nutrient Artery
The nutrient artery is the main blood vessel that enters the diaphysis via the nutrient foramen. While most long bones have only one nutrient foramen, large bones, such as the femur, may have two. This...