Related Experiment Video
Updated: Mar 16, 2026


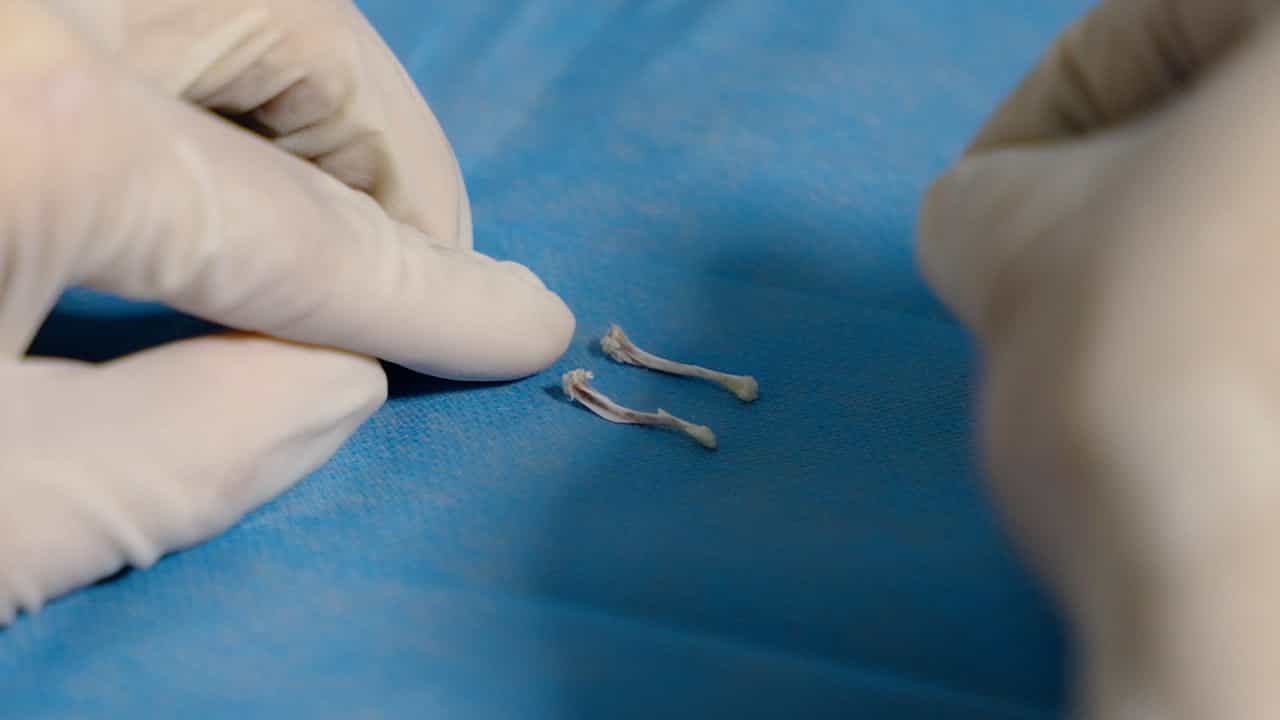
Scanning Skeletal Remains for Bone Mineral Density in Forensic Contexts
Published on: January 29, 2018
Bone mineral density in anorexia nervosa: Only weight and menses recovery?
Ignacio Jáuregui-Lobera1, Patricia Bolaños-Ríos2, Juan Sabaté3
1Area of Nutrition and Food Sciences, Department of Molecular Biology and Biochemical Engineering, Universidad Pablo de Olavide, Seville, Spain; Behavioural Sciences Institute, Seville, Spain.

Introduction:
The study objectives were to analyze the presence of reduced bone mass in a sample of patients with anorexia nervosa (AN) and amenorrhea, to assess Bone Mineral Density (BMD) recovery after having a normal weight is reached and regular menses are resumed, and to predict BMD after a treatment period considering different variables (baseline BMD, baseline and final body mass index (BMI), treatment duration).
Material & Methods:
35 patients with AN (mean age 20.57±5.77) were studied at treatment start (T0) and after they had recovered their normal weight and regular menses (T1) in order to measure their BMD using quantitative computed tomography (QCT) of the lumbar spine (L2-L4).
Results:
At T0, 2.86% of patients had normal BMD, while a reduced bone mass consistent with osteopenia or with osteoporosis was found in 22.86% and 74.28% of patients respectively. At T1, the percentages were 20%, 20%, and 60% respectively. No significant differences were seen in L2-L3 and mean BMD (L2-L4). A significant difference was however found for L4 (p<0.05). A positive relationship was seen between final body mass index (BMI) and final BMD in patients with T0-T1>11 months, but not when the time period was ≤11 months.
Conclusions:
This follow-up study of changes not only in BMD but also in BMI and recovery of menses has clinical relevance from the viewpoint of the day-by-day treatment process. Use of QCT makes the study more relevant because this is a more advanced technique that allows for differentiating trabecular and cortical bone.
More Related Videos
 07:12
Semiautomated Longitudinal Microcomputed Tomography-based Quantitative Structural Analysis of a Nude Rat Osteoporosis-related Vertebral Fracture Model
Published on: September 28, 2017
 06:59
Author Spotlight: An Economic and Efficient Method for Quantitative Evaluation of Bone Microarchitecture in a Murine Osteoporosis Model
Published on: September 8, 2023
Related Concept Videos
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...
 01:40
Bone Remodeling
 01:28
Anorexia Nervosa
Symptoms and Physical Effects
Individuals with anorexia nervosa commonly exhibit extreme...
 01:30
Bulimia Nervosa
 01:17
Hormones and Bone Tissue
Hormones That Influence Osteoblasts and/or Maintain the Matrix
Several hormones are necessary for controlling bone growth and maintaining the bone matrix. The pituitary gland secretes growth hormone (GH), which, as its name implies, controls bone growth. This happens in several ways: first, it triggers chondrocyte...
 01:22
Hormonal Regulation of the Menstrual Cycle
At puberty, GnRH begins a pulsatile release pattern, which triggers the anterior pituitary gland to secrete follicle-stimulating hormone (FSH) and luteinizing hormone (LH). The frequency and amplitude of GnRH pulses vary across the menstrual cycle, with faster pulses favoring LH release and slower pulses favoring FSH...