Related Experiment Video
Updated: Mar 16, 2026


Modeling Encephalopathy of Prematurity Using Prenatal Hypoxia-ischemia with Intra-amniotic Lipopolysaccharide in Rats
Published on: November 20, 2015
Birth defects and neonatal morbidity caused by teratogen exposure after the embryonic period
Angela E Scheuerle1, Arthur S Aylsworth2
1Department of Pediatrics, University of Texas Southwestern Medical Center, Dallas, Texas.

Background:
Pharmaceutical pregnancy exposure registries seek to evaluate temporal associations between drug exposures and adverse outcomes, particularly congenital anomalies. These registries record observed associations that may or may not be causally-related to the exposure. Most major congenital malformations (i.e., structural birth defects) result from abnormal development during embryogenesis. A standardized catalog of defects of concern (colloquially the "BPA Codes") is used both in public health surveillance programs and pregnancy exposure registries. There are, however, some anomalies that cause significant morbidity and mortality for which isolated second or third trimester exposures may be pathogenically significant. There currently exists no standardized list of defects for which exposure limited to the fetal period may be problematic.
Methods:
The six-digit-code list was used to determine anomalies that might result from medication exposures limited to the fetal period.
Results:
Defects with documented first trimester pathogenesis (e.g., anencephaly, heterotaxy) were eliminated from consideration, as were chromosomal and single gene disorders (e.g., trisomy 21, achondroplasia). The remaining defects include the following: (1) those that are known to or could reasonably originate or manifest after the embryonic period (e.g., porencephaly, cataracts); (2) those for which pathogenesis is unclear or variable enough that exposure at any gestational age might be considered relevant (e.g., club foot, microcephaly); and (3) those that include some component of abnormal growth (e.g., hemihyperplasia). "Unspecified" defects (e.g., "abnormality of the leg") were included by default because there is insufficient information to assume first trimester embryogenesis.
Conclusion:
The final result is a list of major and minor anomalies in 11 organ system categories that may be caused by teratogen exposure during the fetal period. Birth Defects Research (Part A) 106:935-939, 2016. © 2016 Wiley Periodicals, Inc.
Insights
A new list identifies birth defects potentially linked to fetal period drug exposure. This helps pregnancy registries assess risks beyond the first trimester, improving safety for developing babies.
Area of Science:
- Teratology and developmental toxicology
- Reproductive and perinatal epidemiology
- Public health surveillance
Background:
- Pregnancy registries assess drug exposure risks for congenital anomalies.
- Most major birth defects arise during early embryogenesis.
- No standardized list exists for defects potentially caused by fetal period exposures.
Purpose of the Study:
- To create a standardized list of anomalies potentially caused by drug exposure limited to the fetal period.
- To aid pregnancy exposure registries in evaluating risks beyond the first trimester.
Main Methods:
- Utilized a six-digit-code list to identify relevant anomalies.
- Excluded defects with documented first-trimester pathogenesis, chromosomal, or single-gene disorders.
- Included defects originating/manifesting post-embryonic period, those with unclear pathogenesis, or growth components.
Main Results:
- Identified anomalies potentially linked to fetal period teratogen exposure.
- Included defects like porencephaly, cataracts, club foot, microcephaly, and hemihyperplasia.
- Included unspecified defects due to insufficient information on embryogenesis.
Conclusions:
- A comprehensive list of major and minor anomalies across 11 organ systems was developed.
- This list may be caused by teratogen exposure during the fetal period.
- Facilitates more accurate risk assessment in pharmaceutical pregnancy exposure registries.

Related Concept Videos
 01:07
Teratogenicity
 02:57
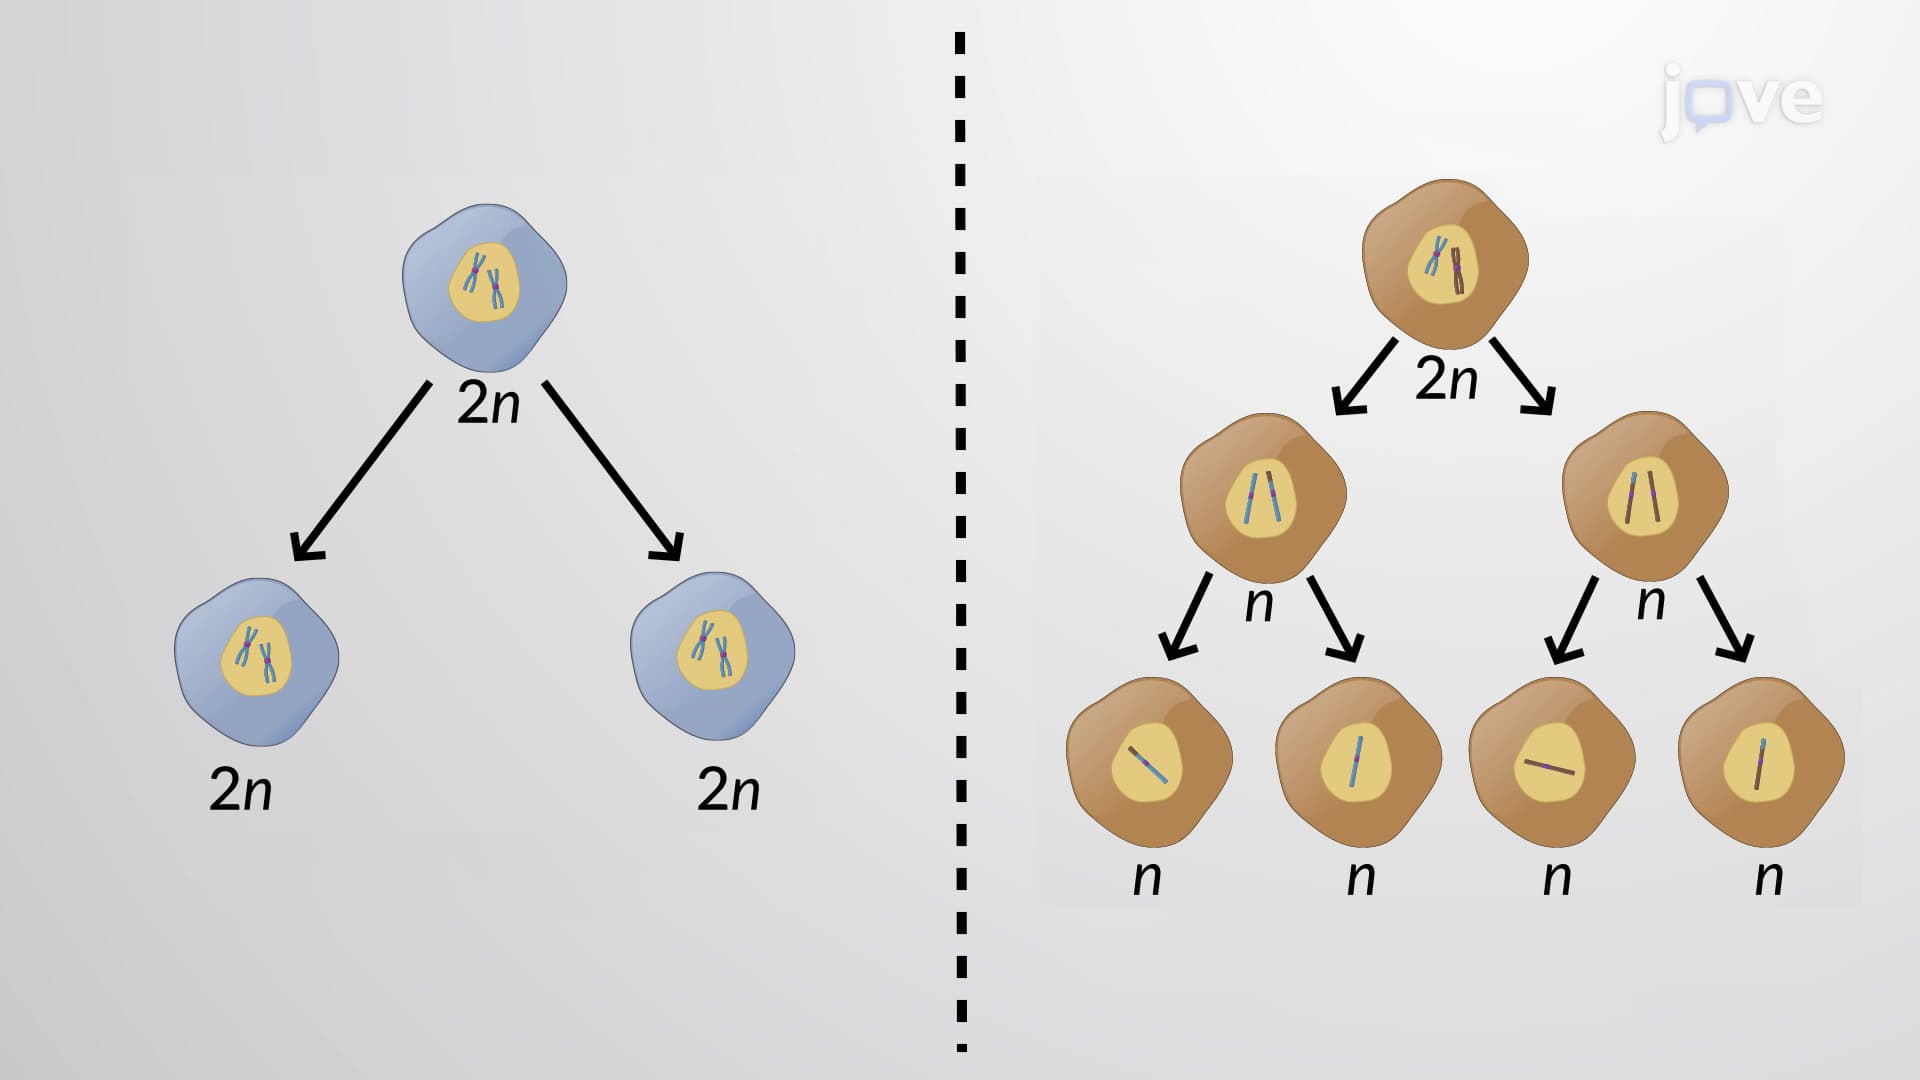
Meiosis vs. Mitosis
Before the start of mitosis and meiosis I, the cell synthesizes DNA, resulting in two homologous copies of each chromosome. DNA synthesis is...
 01:22
Development of Immunocompetence
The initial cells that migrate from the fetal thymus settle within the skin and epithelial tissues lining the mouth, digestive tract, and in females, the uterus and vagina. These cells, including skin-based dendritic cells, serve as antigen-presenting cells, playing a key role in T cell activation.
Subsequent T...
 01:20
Pathophysiology of Diabetes
Type 1 diabetes is characterized by autoimmune-mediated destruction of pancreatic β cells, with environmental factors potentially triggering this process in genetically susceptible individuals. Despite many not having a family history, certain genes increase susceptibility,...
 01:24
Drug Toxicity: Dose-Dependent Reactions
 01:24
Drug Toxicity: Risk factors