Related Experiment Video
Updated: Mar 16, 2026

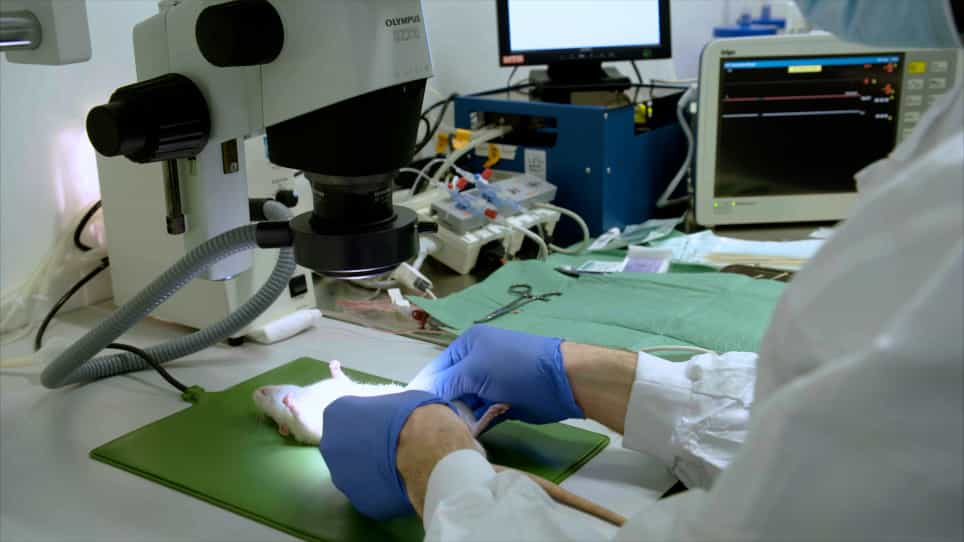
Standardized Colon Ascendens Stent Peritonitis in Rats - a Simple, Feasible Animal Model to Induce Septic Acute Kidney Injury
Published on: February 15, 2022
Systemic over-release of interleukin-17 in acute kidney injury after septic shock: Clinical and experimental evidence
Panagiota Maravitsa1, Maria Adamopoulou2, Aikaterini Pistiki1
14th Department of Internal Medicine, National and Kapodistrian University of Athens, Greece.

In order to investigate the role of T-helper 17 (Th17) cell activation in acute kidney injury (AKI) after septic shock, a two-stage approach was used. Firstly, peripheral blood mononuclear cells (PBMCs) and CD4-lymphocytes were isolated the first 24h after septic shock from 26 patients with AKI and 18 patients with chronic renal disease (CRD) without AKI and stimulated for the release of tumour necrosis factor-alpha (TNFα), interleukin (IL)-10, IL-17, IL-22 and interferon-gamma (IFNγ). Results were compared with 15 healthy volunteers and 13 patients with uncomplicated sepsis. Secondly, a murine model of multiple organ dysfunction (MODS) complicated with AKI and bacterial gut translocation was studied, and IL-10, IL-17, IL-22 and IFNγ were measured in kidney homogenates. IL-17 was the only cytokine produced at greater quantities from PBMCs and CD4-lymphocytes of patients with septic shock and AKI than comparators. When PBMCs of patients with septic shock and AKI were ex-vivo stimulated, intracellular staining for IL-17 was greater in CD3(+)/CD4(+)/CD196(+) cells compared to patients with septic shock and CRD. IL-17 was released at greater amounts from PBMCs of non-survivors by septic shock and AKI but not of septic shock and CRD. In the murine model of MODS, a gradual decrease of IL-17, but not of IL-10, IL-22 and IFNγ, of kidney homogenates was found indicating over-consumption. These results suggest that AKI after septic shock is driven through IL-17 release by Th17 cells; this is gradually consumed in the kidney.
In order to investigate the role of T-helper 17 (Th17) cell activation in acute kidney injury (AKI) after septic shock, a two-stage approach was used. Firstly, peripheral blood mononuclear cells (PBMCs) and CD4-lymphocytes were isolated the first 24h after septic shock from 26 patients with AKI and 18 patients with chronic renal disease (CRD) without AKI and stimulated for the release of tumour necrosis factor-alpha (TNFα), interleukin (IL)-10, IL-17, IL-22 and interferon-gamma (IFNγ). Results were compared with 15 healthy volunteers and 13 patients with uncomplicated sepsis. Secondly, a murine model of multiple organ dysfunction (MODS) complicated with AKI and bacterial gut translocation was studied, and IL-10, IL-17, IL-22 and IFNγ were measured in kidney homogenates. IL-17 was the only cytokine produced at greater quantities from PBMCs and CD4-lymphocytes of patients with septic shock and AKI than comparators. When PBMCs of patients with septic shock and AKI were ex-vivo stimulated, intracellular staining for IL-17 was greater in CD3(+)/CD4(+)/CD196(+) cells compared to patients with septic shock and CRD. IL-17 was released at greater amounts from PBMCs of non-survivors by septic shock and AKI but not of septic shock and CRD. In the murine model of MODS, a gradual decrease of IL-17, but not of IL-10, IL-22 and IFNγ, of kidney homogenates was found indicating over-consumption. These results suggest that AKI after septic shock is driven through IL-17 release by Th17 cells; this is gradually consumed in the kidney.

Related Concept Videos
 01:29
Acute Kidney Injury II: Pathophysiology
 01:22
Acute Kidney Injury I: Introduction
 01:29
Acute Kidney Injury III: Clinical Manifestations
 01:30
Acute Kidney Injury IV: Diagnostic Studies and Prevention
 01:20
Acute Kidney Injury V: Interprofessional Care
 01:22
Acute Kidney Injury VI: Nursing Management