Related Experiment Video
Updated: Mar 16, 2026
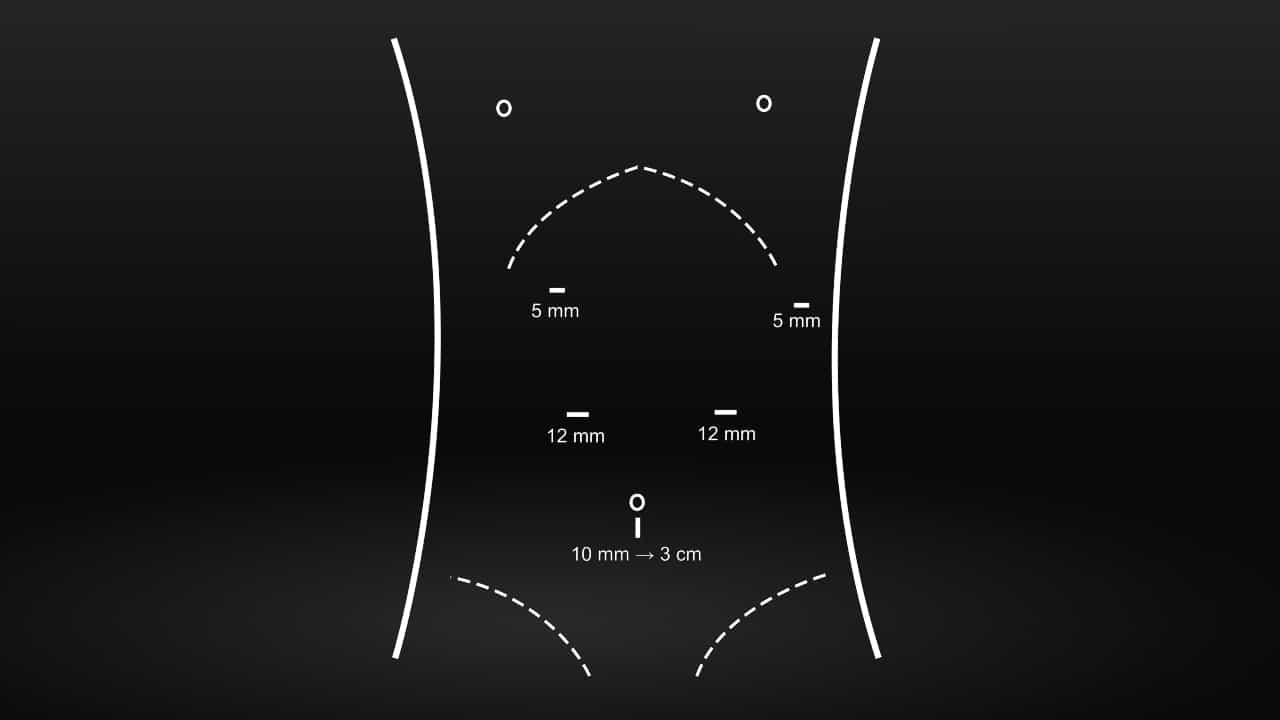

Laparoscopic Splenectomy with Pericardial Devascularization for Hypersplenism and Esophageal Variceal Hemorrhage Due to Portal Hypertension
Published on: November 15, 2024
Surgical Management of Peripheral Vascular Manifestations of Loeys-Dietz Syndrome
Robert J Beaulieu1, Jennifer Lue2, Bryan A Ehlert3
1Department of Surgery, Johns Hopkins Medical Institutes, Baltimore, MD.

Background:
Loeys-Dietz syndrome (LDS) is characterized by a triad of aortic aneurysm, vessel tortuosity, and hypertelorism. LDS patients often harbor additional aneurysms and dissections throughout their vasculature. The optimal management of these additional lesions is poorly understood. Accordingly, we sought to analyze our experience with the peripheral arterial manifestations of LDS.
Methods:
Adult and pediatric LDS patients who sought treatment at a single institution from 2005 to 2015 were retrospectively reviewed. Patients were included if radiographic or clinically documented evidence existed of peripheral artery aneurysm or dissection. Standard univariate analyses were performed.
Results:
Eighteen LDS patients (aged 1.3-59.3 years, mean age 27.8 years at diagnosis) with aortic (not including root, ascending, or arch) vascular abnormalities were identified. Average follow-up was 5.2 ± 3.8 years. Fourteen (77.8%) patients had peripheral aneurysms, occurring most frequently in the carotid (35.7%), subclavian (35.7%), and visceral (28.6%) segments. Most patients had multiple peripheral segments involved (average 2, range 1-6). Nine (64%) patients with peripheral involvement underwent repair, for a total of 17 operations (average 1.89 operations per patient, range 1-4). Endovascular techniques were used in 4 operations (23.5%), without technical failures. Among patients requiring surgical repair, a history of abdominal aortic repairs was present in 77.8%, yielding a total of 36 vascular repairs (average 4, range 2-7). Perioperative morbidity was 11.8%, with no reported mortalities. Prior aortic dissection was not associated with peripheral surgical repairs (P = 0.58).
Conclusions:
LDS is an aggressive vasculopathy which commonly affects the peripheral vasculature. Our data suggest that open and endovascular procedures may be safe and effective in the LDS periphery and multiple operations are common. As prior aortic dissection did not predict peripheral arterial involvement in LDS, vigilant peripheral arterial surveillance of LDS is warranted regardless of aortic disease state and may be key to early identification and our treatment success.
Related Concept Videos
 01:27
Peripheral Artery Disease III: Interprofessional Care
 01:23
Peripheral Artery Disease V: Postoperative Nursing Management
 01:26
Varicose Veins II: Diagnostic Studies and Interprofessional Care
 01:26
Peripheral Artery Disease IV: Nursing Management
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol...