Related Experiment Video
Updated: Sep 29, 2026


Programmed Electrical Stimulation in Mice
Published on: May 26, 2010
The excitable gap in atrioventricular nodal reentrant tachycardia. Characterization with ventricular extrastimuli and
C D Schuger1, R T Steinman, M H Lehmann
1Electrophysiology Laboratory, Wayne State University, Detroit, Michigan.

Abstract:
Our purpose was to characterize the excitable gap during atrioventricular nodal reentrant tachycardia (AVNRT) to elucidate the electrophysiologic substrate of this clinically familiar microreentrant arrhythmia. Accordingly, in 11 patients with classic slow-fast AVNRT (mean cycle length, 342 +/- 41 msec), a single ventricular extrastimulus (V2) was periodically delivered after a spontaneous tachycardia beat (V1) until ventricular refractoriness was reached. With this technique, an excitable gap was considered present when atrial preexcitation of at least 20 msec could be achieved along with tachycardia resetting (noncompensatory pause after V2). The range of V1V2 intervals that resulted in atrial preexcitation constituted the preexcitation zone. Five patients (45%) showed evidence of an excitable gap at baseline, with a maximal atrial preexcitation achievable of 33 +/- 6 msec, representing 9 +/- 1% of the tachycardia cycle length. Verapamil was then administered to all 11 patients with the purpose of slowing the anterograde tachycardia wavefront before arrival of V2. This resulted in widening of the preexcitation zone in three patients by a mean of 50 +/- 37 msec, with a corresponding increase in maximal atrial preexcitation to 70 +/- 32 msec, or 16 +/- 4% of AVNRT cycle length, and the appearance of atrial preexcitation in two patients who lacked it during baseline. In the remaining six patients, AVNRT was not sustained after verapamil or was too unstable for evaluation. During baseline, V2A2 conduction time increased by only 5 +/- 3 msec throughout the preexcitation zone, with values at the outer border unchanged after verapamil, implying a fully excitable gap in the retrograde limb. In all patients with a preexcitation zone, AVNRT was consistently reset by V2, both at baseline and after verapamil, with a "flat" but mainly "increasing" response pattern as V1V2 was shortened. Hence, a significant number of patients with AVNRT have evidence of an excitable gap whose demonstrability can be facilitated by pharmacologic intervention; documentation of an increasing resetting response pattern, most apparent after verapamil, provides new evidence for a reentrant mechanism in AVNRT; and while not definitively proven, the presence of a fully excitable gap during AVNRT is most consistent with a microreentry circuit that incorporates an anatomic obstacle.


Related Concept Videos
 01:19
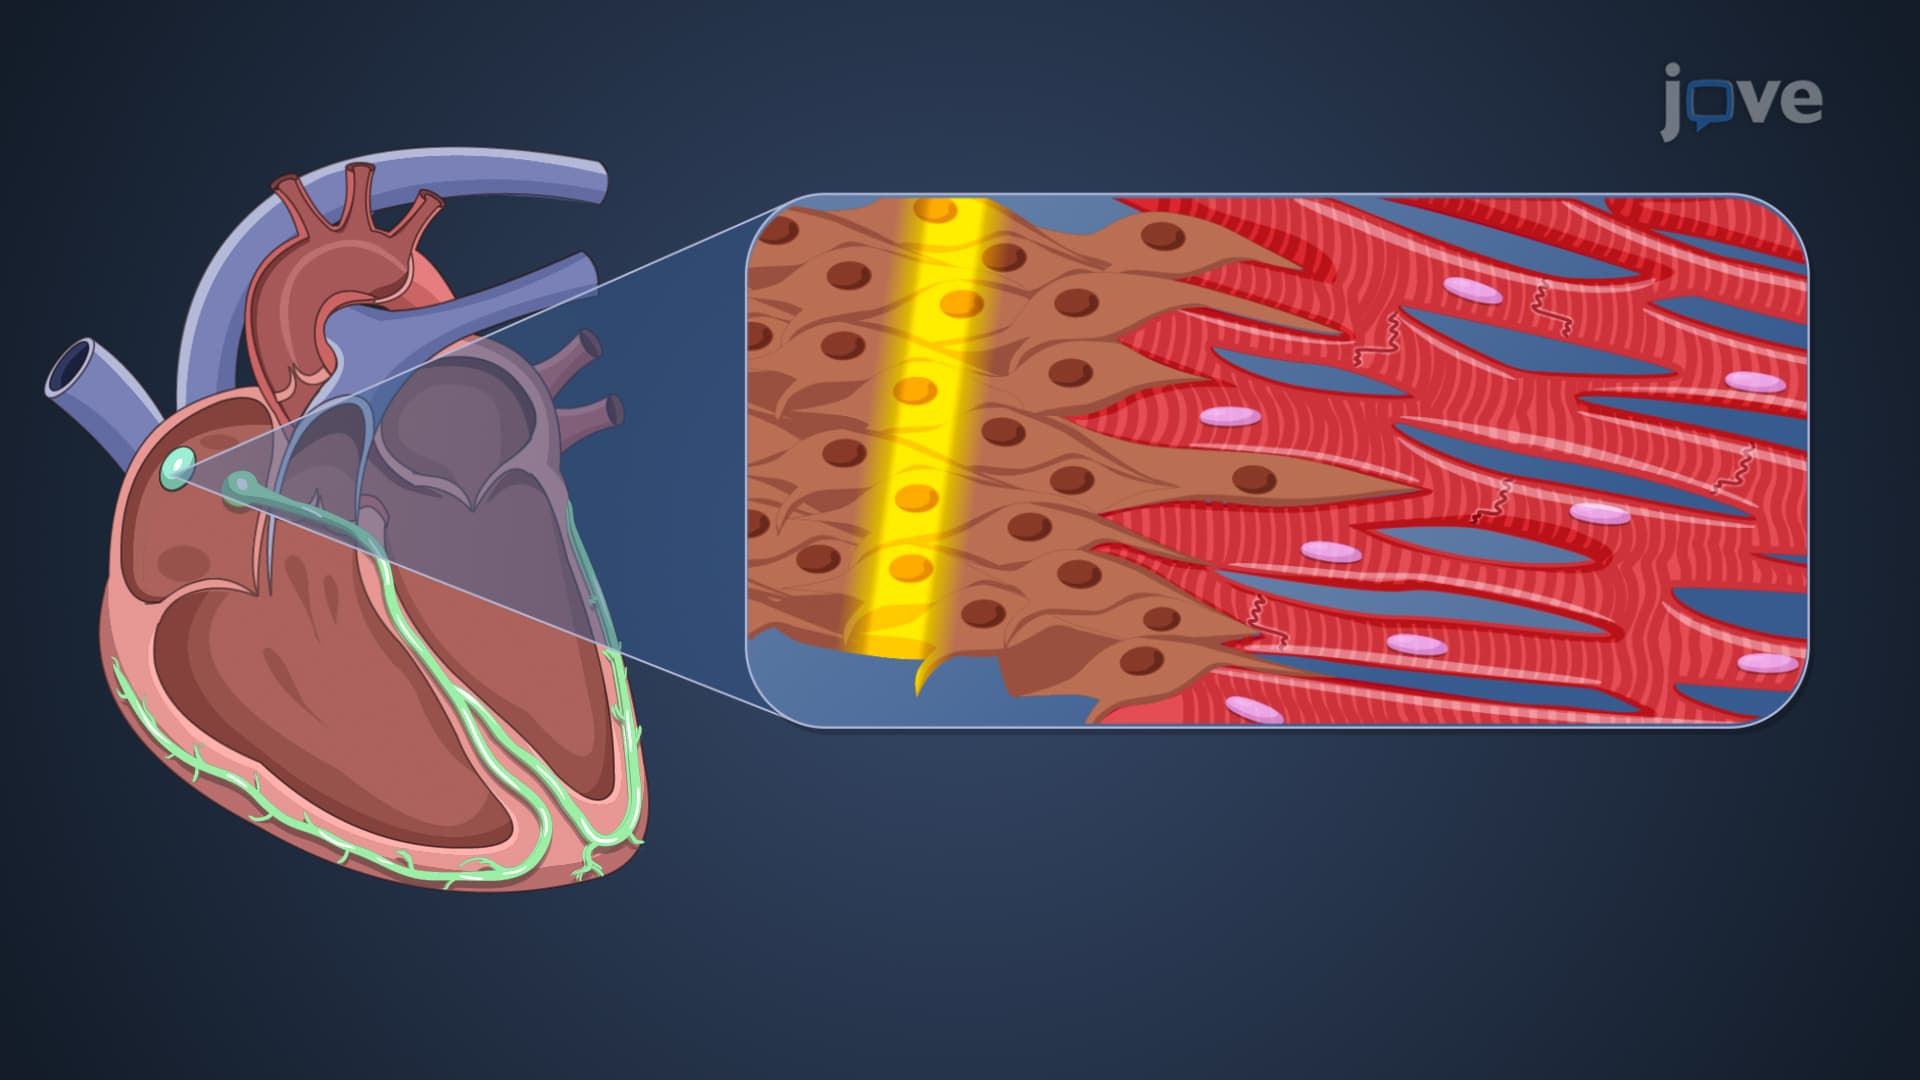
Electrophysiology of Normal Cardiac Rhythm
 01:20
Antiarrhythmic Drugs: Class IV Agents as Calcium Channel Blockers
Verapamil, a calcium channel blocker, inhibits calcium movement across myocardial cell membranes and vascular smooth muscle. This results in the dilation of coronary and...
 01:30
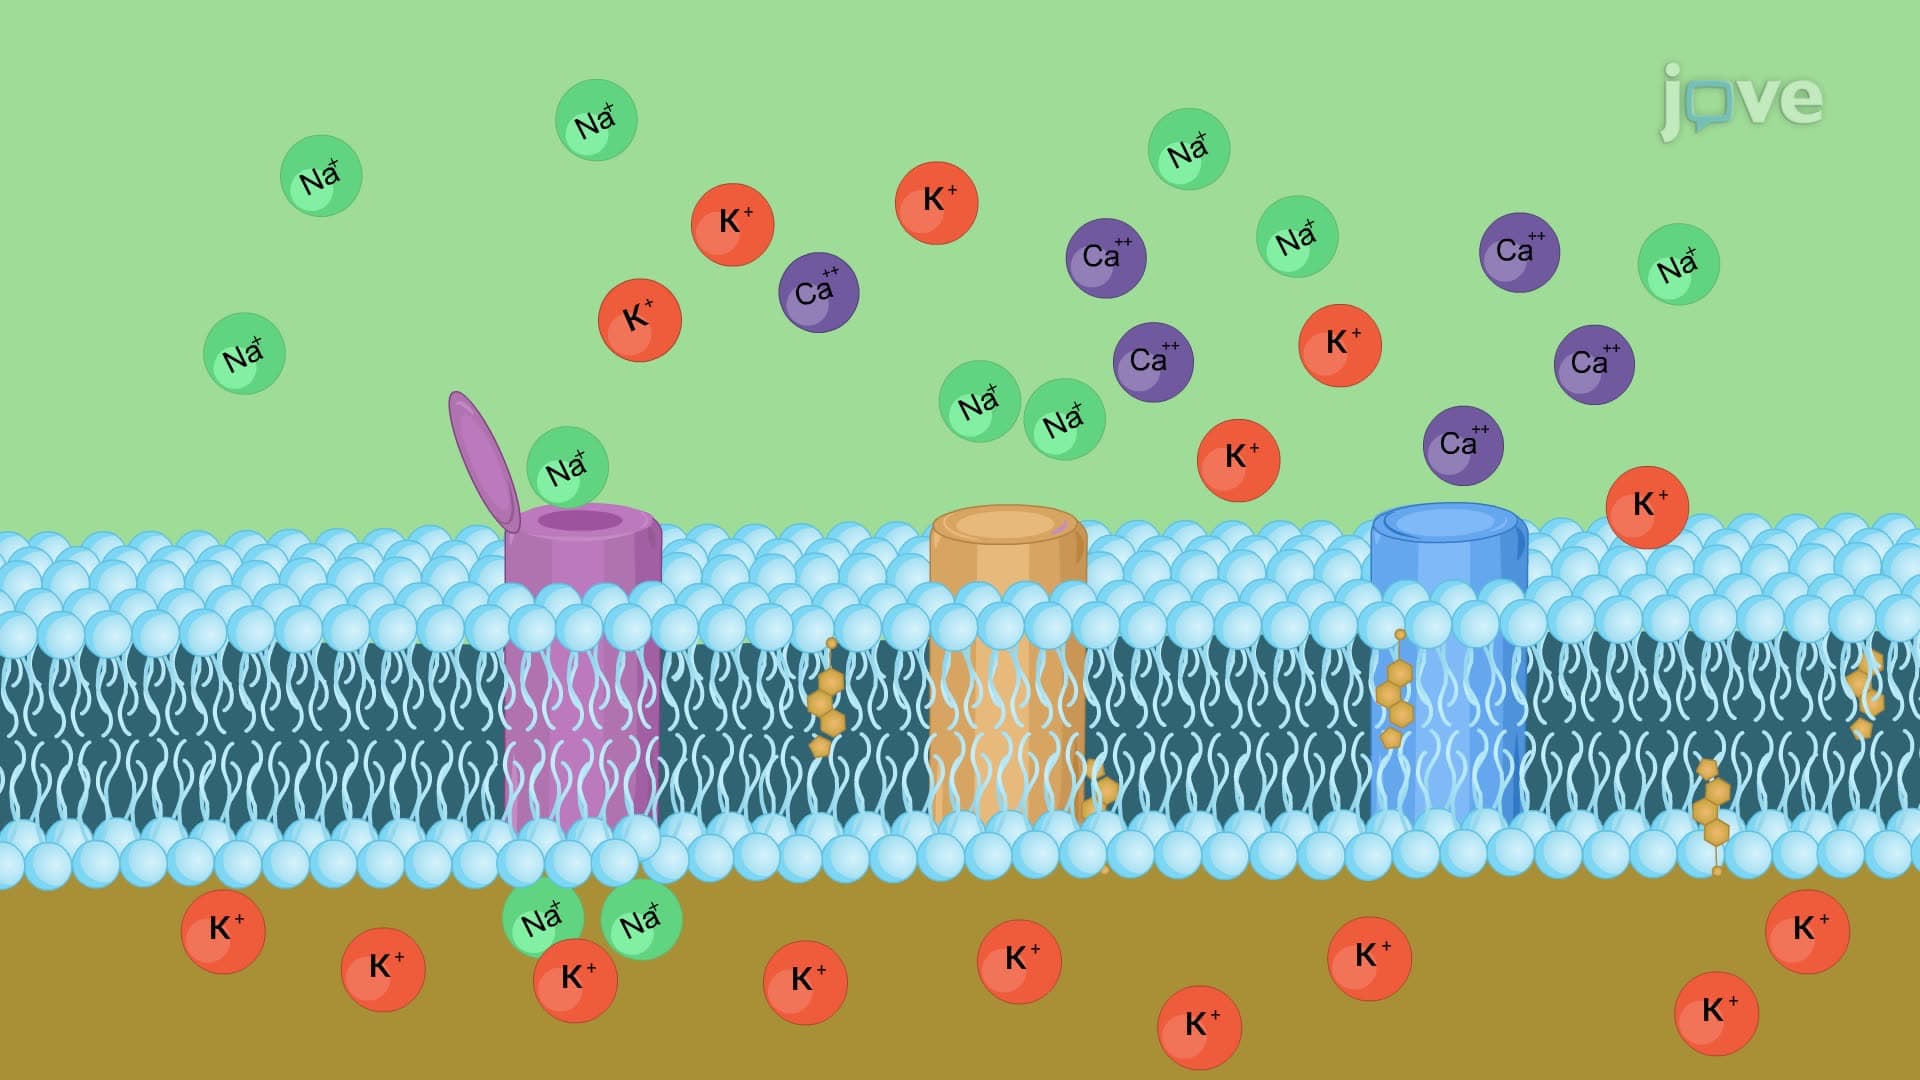
Cardiac Action Potential
The cardiac action potential process involves a series of phases characterized by the movement of ions across the cardiac cell membranes, leading to the depolarization and repolarization of the cardiac myocytes.
Ionic Basis of Cardiac Action Potentials
 01:29
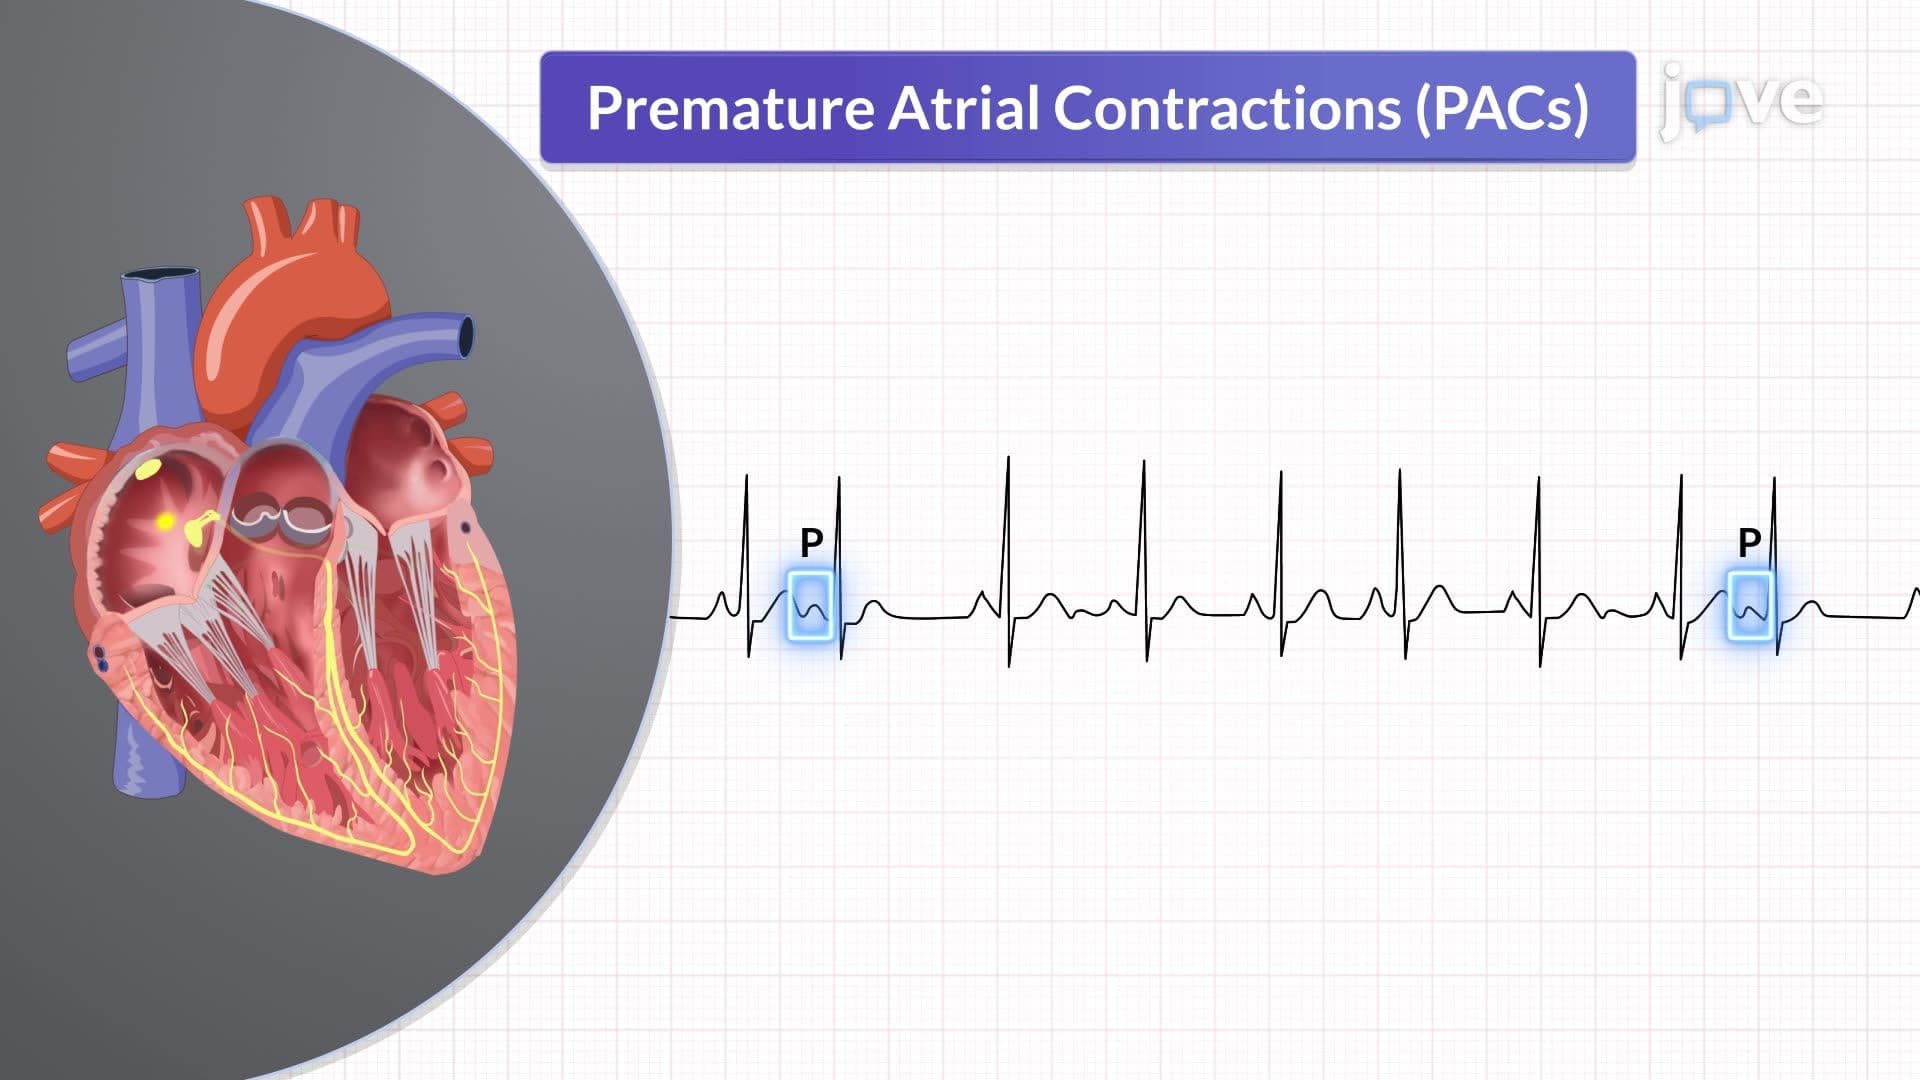
Dysrhythmias III: Characteristics of Dysrhythmias
 01:25
Dysrhythmias VI: Management of Dysrhythmias
 01:25
ECG Interpretation of Arrhythmias II: Atrial, Junctional and Ventricular Arrhythmias