Related Experiment Video
Updated: Mar 16, 2026
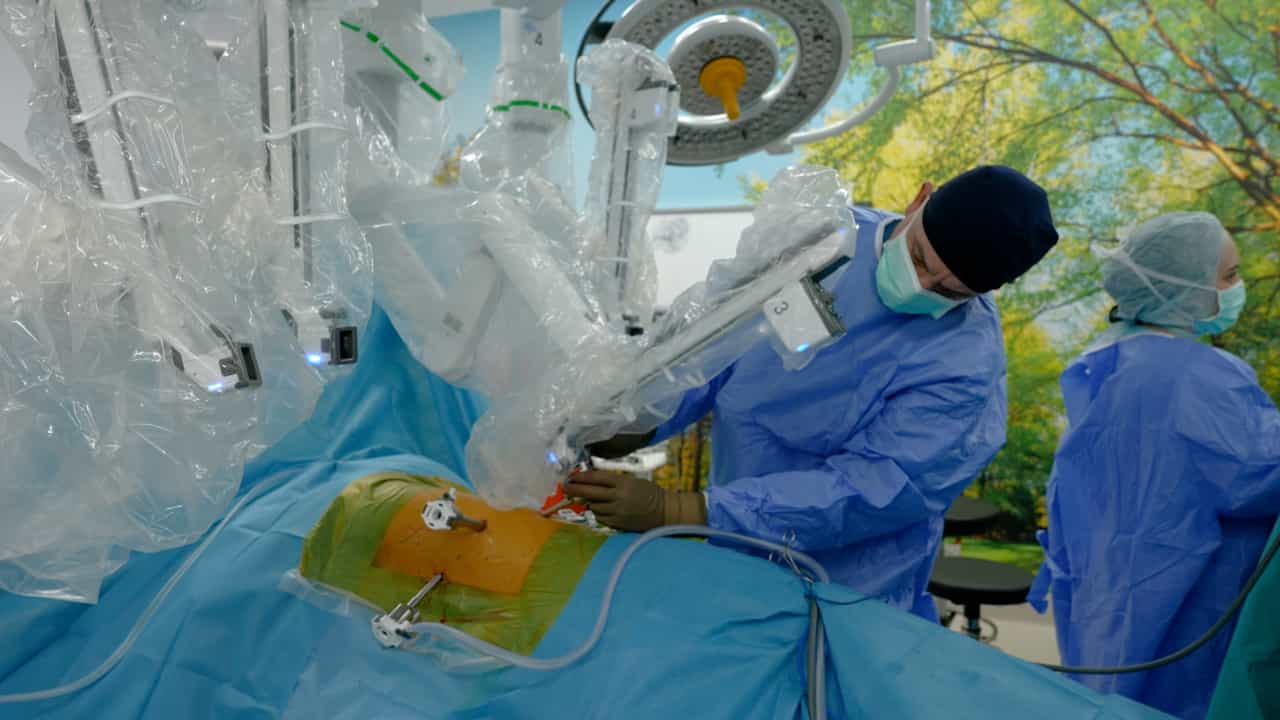
Subcostal Specimen Removal in Completely Portal Robotic Lobectomy
Published on: April 19, 2024
The Influence of Reconstructive Technique on Perioperative Pulmonary and Infectious Outcomes Following Chest Wall
Jonathan D Spicer1, Jitesh B Shewale2, Mara B Antonoff2
1Department of Thoracic Surgery, McGill University, Montreal, Quebec, Canada.

Background:
Emerging technologies for prosthetic reconstruction after chest wall resection have yielded a wide variety of reconstructive options for thoracic surgeons. The ideal chest wall reconstruction and its impact on perioperative outcomes has not been well defined. Our goal was to determine whether mesh characteristics such as rigidity or absorbability altered perioperative pulmonary and infectious outcomes.
Methods:
Our institutional database was queried for patients who underwent chest wall resection and reconstruction for primary or secondary chest wall tumors between the years 1998 and 2013. A focused chart review supplied clinical and perioperative variables. The main study outcomes focused on perioperative pulmonary and wound/implant infectious complications. Univariate and multivariate analyses were performed to identify variables associated with outcome.
Results:
We identified 1,096 patients who underwent chest wall resection during the study period, of which 427 required chest wall reconstruction. Pulmonary complications occurred in 24% (n = 102 of 427) of patients. We observed no significant difference in pulmonary complications between those that had a rigid versus flexible chest wall reconstruction (p = 0.401; OR, 1.43; 95% CI, 0.83-2.43). The odds of pulmonary complications increased with each additional resected rib (OR, 1.43; 95% CI, 1.2-1.71). Multivariable analysis identified the number of resected ribs (OR, 1.26; 95% CI, 1.00-1.59) and concomitant lobectomy (OR, 3.59; 95% CI, 1.62-7.92) as variables associated with perioperative pulmonary morbidity. Infectious complications occurred in 13 patients and were not predicted by the use of permanent versus absorbable prosthetic materials (p = 0.575).
Conclusions:
The type of reconstructive material, whether with rigid, flexible, permanent, or biologic characteristics, does not appear to influence perioperative pulmonary or infectious wound complications. Rather, the number of resected ribs and the concomitant lung parenchymal resection predict pulmonary morbidity following chest wall resection. Depending on the circumstances, an effective chest wall reconstruction can be achieved with either rigid or flexible prosthetic material.
More Related Videos


Related Concept Videos
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:30
Endoscopic Studies I: Bronchoscopy and Thoracoscopy
Bronchoscopy
Description
Bronchoscopy is a procedure that involves direct visualization of the larynx, trachea, and bronchi for diagnostic and therapeutic purposes. A flexible fiber optic or rigid bronchoscope is used to carry out the procedure. The fiber-optic bronchoscope is more frequently used due...
 01:26
Endoscopic Studies II: Thoracocentesis
Description
Excess pleural fluid or air may accumulate in some respiratory disorders in the thoracic cavity. To treat pleural effusion, a physician conducts thoracentesis by carefully piercing the chest wall and entering...
 01:30
Pneumonia V: Nursing management and Prevention
The nurse must practice strict medical asepsis and adhere to infection control guidelines to minimize healthcare-associated infections.
Enhance airway patency
Position the patient correctly to facilitate drainage of the affected lung segments. Manual or mechanical percussion and vibration can also be employed....
 01:17
Pulmonary Cycle: Exhalation