Related Experiment Video
Updated: Mar 16, 2026
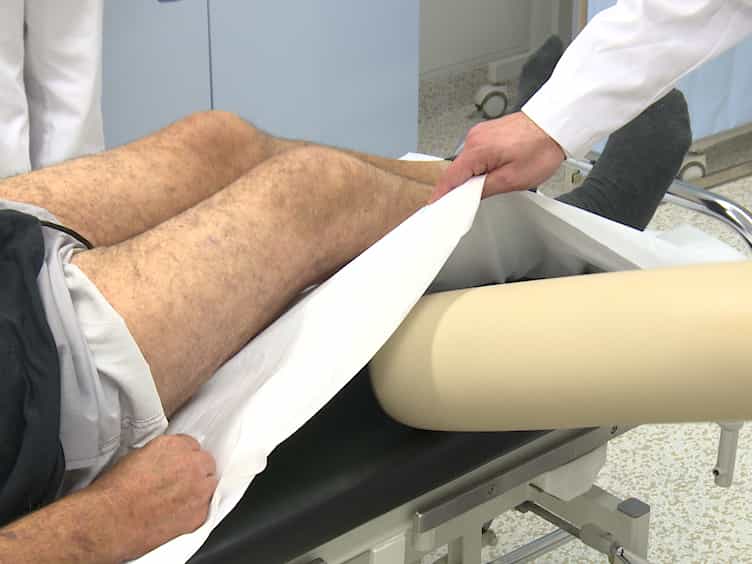

Novel Diagnostics in Revision Arthroplasty: Implant Sonication and Multiplex Polymerase Chain Reaction
Published on: December 3, 2017
[Diagnosis of Periprosthetic Infection - What's Obligation, What's Optional?]
1Orthopädische Klinik Braunschweig, Herzogin-Elisabeth-Hospital (HEH), Braunschweig.

Background:
Periprothetic infection after primary or revision arthroplasty is of increasing importance. The incidence of infection in primary arthroplasty is approximately 1 %. Revision arthroplasty has higher infection rates, which increase with the number of revision surgeries. Aim of this Paper: An overview of the current diagnosis of periprosthetic infection.
Methods:
This selective analysis is based on a lecture by the author at the DKOU 2015.
Results:
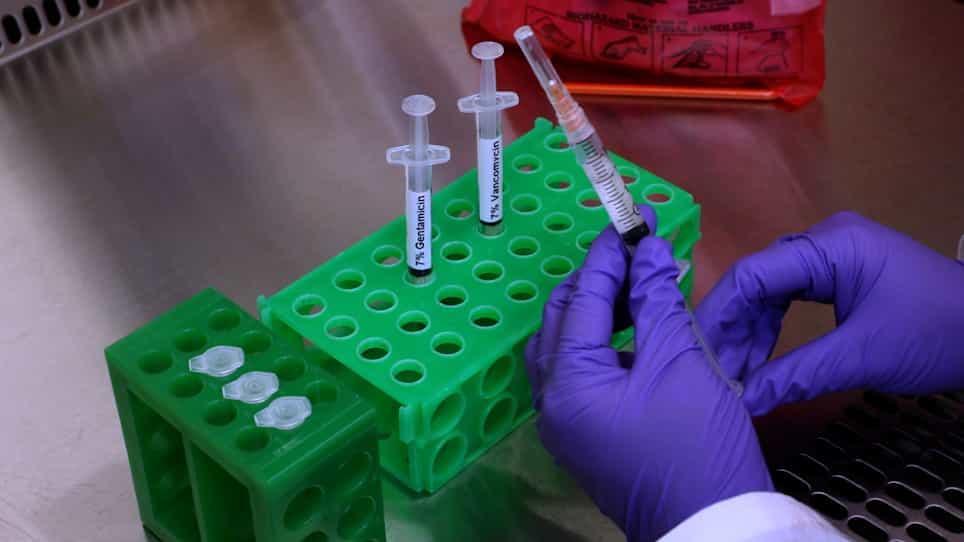
Periprosthetic infection is taken as having been demonstrated when either two periprosthetic cultures contain the same microorganism, or if there is a fistula communicating with a joint. If only minor criteria are met, the detection of an infection is more difficult. The medical history only provides supporting evidence, especially as regards the course of the pain. Physical examination is more helpful, especially if there is redness, swelling, heat or wound dehiscence. Radiological pathologies, such as osteolysis or bone resorption can only be found in advanced infections. Nuclear medicine scans only possess acceptable sensitivity and specificity in combination with leukocyte scintigraphy. ESR, CRP and leukocyte blood count of the blood are of poor specificity. Important and targeted diagnostic steps include joint aspiration under aseptic conditions, although this exhibits a relatively high rate of false negative results. The conditions for this must be stringently observed. This is usefully complemented by cytological examinations and biopsies for tissue culture. Sensitivity and specificity are then increased. Sonication can significantly enhance the detection of an infection. The leukocyte esterase test is inexpensive and easy to perform and is therefore very much in vogue at the moment; however it is useless if there is contamination with blood. Recent studies indicate that the alpha-defensin test possesses high sensitivity and specificity, but has the disadvantage of being expensive.
Conclusions:
In patients with suspected periprosthetic infection, the primary aim is either to exclude an infection, or to detect a pathogen. The essential components are careful evaluation of the medical history, accompanied by imaging and laboratory tests. A critical approach is essential. Joint aspiration has become the gold standard in detecting periprosthetic infections. This should be performed in conjunction with a cytological analysis of the synovial fluid. An improvement in sensitivity and specificity can be archived by taking tissue samples. Sonication significantly improves the results. The latter method, the leukocyte esterase test and the alpha-defensin test are optional. The essential components are a rigorous evaluation, a clear algorithm and interdisciplinary collaboration with microbiologists and possibly infectiologists.
Insights
Diagnosing periprosthetic joint infection requires a comprehensive approach, combining medical history, imaging, and laboratory tests. Joint aspiration with synovial fluid analysis is the gold standard for pathogen detection.
Area of Science:
- Orthopedic Surgery
- Infectious Diseases
- Diagnostic Microbiology
Background:
- Periprosthetic joint infection (PJI) is a significant complication following primary and revision arthroplasty.
- Infection rates increase with the complexity and number of revision surgeries.
- Accurate diagnosis of PJI is crucial for effective treatment and patient outcomes.
Purpose of the Study:
- To provide an overview of current diagnostic methods for periprosthetic joint infection.
- To highlight key diagnostic criteria and emerging techniques for PJI detection.
- To emphasize the importance of a structured diagnostic approach.
Main Methods:
- Selective analysis based on a lecture presented at DKOU 2015.
- Review of diagnostic criteria including clinical presentation, imaging, and laboratory tests.
- Evaluation of joint aspiration, tissue sampling, and newer diagnostic markers.
Main Results:
- Periprosthetic infection is confirmed by positive cultures from two periprosthetic samples or a fistula.
- Clinical examination and medical history provide supportive, but not definitive, evidence.
- Radiological findings and basic blood tests (ESR, CRP) have limited specificity for early infection detection.
- Joint aspiration with cytological analysis and tissue cultures significantly increase diagnostic accuracy.
- Leukocyte scintigraphy, sonication, leukocyte esterase, and alpha-defensin tests offer additional diagnostic value with varying costs and specificities.
Conclusions:
- A definitive diagnosis of PJI relies on a combination of clinical evaluation, imaging, and microbiological testing.
- Joint aspiration with synovial fluid cytology is considered the gold standard, ideally complemented by tissue sampling.
- While newer tests like alpha-defensin show promise, a rigorous, algorithm-driven approach with interdisciplinary collaboration is essential for accurate PJI diagnosis.

Related Concept Videos
 01:28
Acute Pyelonephritis II: Diagnostic Studies and Management
 01:30
Urinary Tract Infection III: Diagnostic Studies and Interprofessional Care
 01:18
Endocarditis III: Medical Management
 01:29
Appendicitis-II: Diagnostic Studies and Management
Diagnosing Appendicitis
It requires a multifaceted approach, starting with a detailed physical examination to pinpoint the location and nature of the pain and identify any associated symptoms. Laboratory tests play a crucial role. A complete Blood Count (CBC) typically reveals leukocytosis (an increased number of...
 01:30
Pneumonia III: Complications and Assessment
 01:26
Urine Studies II: Urine Culture and Sensitivity Test