Related Experiment Video
Updated: Mar 16, 2026


Drug Treatment and In Vivo Imaging of Osteoblast-Osteoclast Interactions in a Medaka Fish Osteoporosis Model
Published on: January 1, 2017
Effectiveness of alendronate for bone disorder after gastrectomy for gastric cancer
Yosuke Atsumi1, Yasushi Rino2, Tsutomu Sato3
1Department of Surgery, Yokohama City University, 3-9, Fukuura, Kanazawa-ku, Yokohama, Japan; Department of Gastrointestinal Surgery, Kanagawa Cancer Center, 2-3-2, Nakao, Asahi-ku, Yokohama, Japan.

Background:
Routine therapy of metabolic bone disorder (MBD) after gastrectomy for gastric cancer has not been established yet. We have reported that administering an active vitamin D3 agent to patients who had undergone gastrectomy for gastric cancer improved MBD. Recently, the usefulness of alendronate, an osteoclast inhibitor, has been reported for MBD. Here we report the effects of alendronate for MBD after gastrectomy for gastric cancer.
Methods:
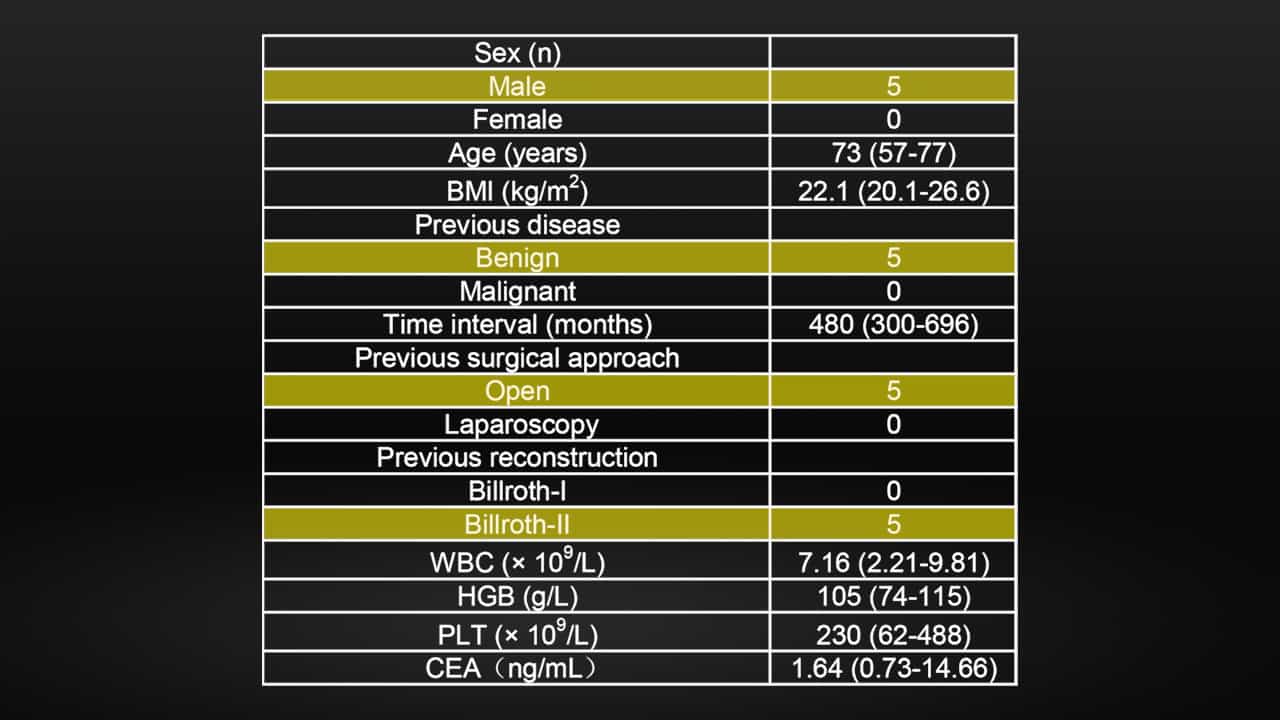
Dual energy X-ray absorptiometry was performed consequently in 14 patients, who had been gastrectomized for gastric cancer and survived more than 5 years without recurrence, to evaluate the MBD and compared before and after treatment. The 14 patients were divided into two groups: in group VD3, 1 μg/d of alfacalcidol, an active vitamin D3 agent, was administered; and in group ALN, 5 mg/d or 35 mg/wk of alendronate or both alfacalcidol and alendronate were administered. These drugs had been administered to the patients for > 2 years, and the patients were followed up.
Results:
After 12 months, dual energy X-ray absorptiometry revealed that bone mineral density and T score were significantly increased in group ALN. Changes in serum bone-specific alkaline phosphatase after 24 months were -9.1 μg/L in the ALN group and 3.75 μg/L in the VD3 group, showing a significant difference (p = 0.02). No serious adverse events were observed in either group.
Conclusion:
These results showed the usefulness of alendronate and alendronate+activated vitamin D3 combination therapy, suggesting that these treatments might prevent postgastrectomic MBD.
Related Concept Videos
 01:26
Peptic Ulcer Disease IV: Management
The therapeutic approach involves ensuring adequate rest, implementing drug therapy, promoting smoking cessation, making dietary modifications, and emphasizing long-term follow-up care.
Pharmacological management
The prevailing therapy for peptic ulcers involves a combination of managing the patient's current...
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:15
Enteral Nutrition II: Nasointestinal and Gastrostomy Feeding
Nasointestinal Feeding
Nasointestinal feeding involves placing a tube...
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...
 01:31
Acid Suppressive Drugs for Peptic Ulcer Disease: Antacids
However, this neutralization reaction between...
 01:24
Drugs for Peptic Ulcer Disease: Sucralfate as Mucosal Protective Agents
In this scenario, mucosal protective agents like sucralfate play an essential role. Sucralfate, a complex of sulfated sucrose and aluminum hydroxide, demonstrates its usefulness in acidic conditions,...