Related Experiment Video
Updated: Mar 15, 2026
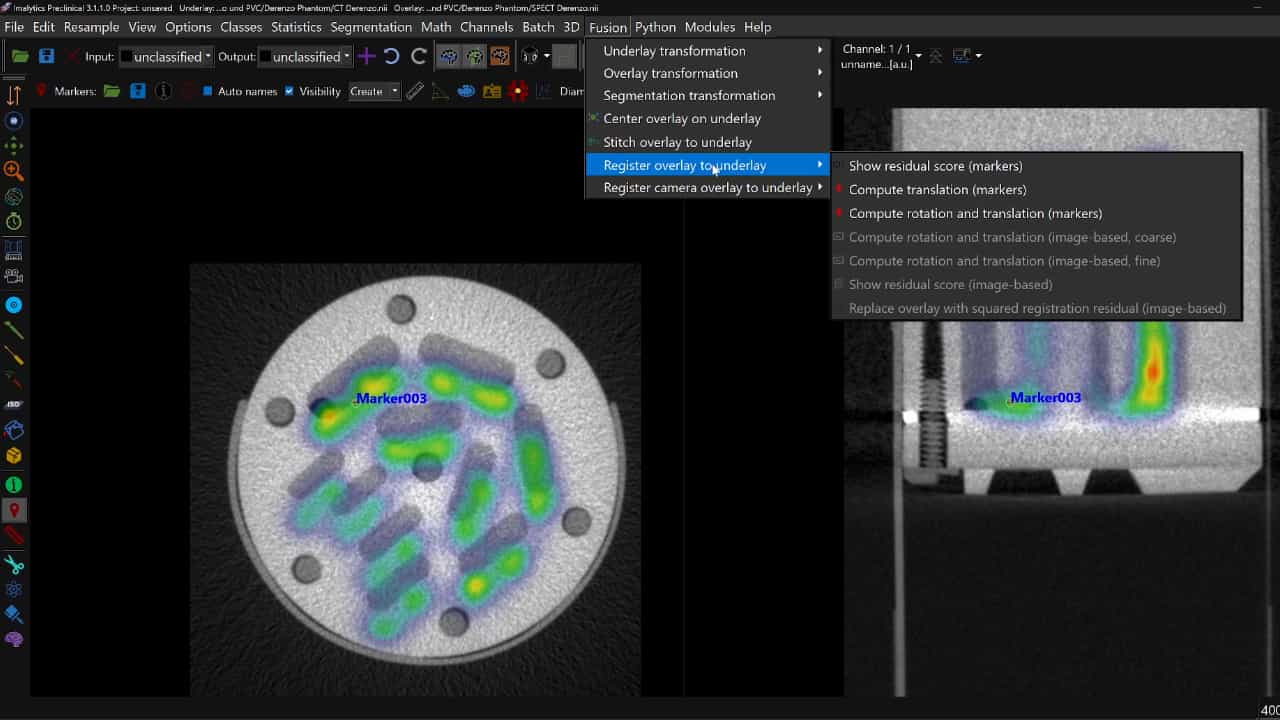

Author Spotlight: An Efficient and Robust Software for Automated Fusion of Multiple Preclinical Imaging Modalities
Published on: October 27, 2023
Interobserver agreement in CTG interpretation using the 2015 FIGO guidelines for intrapartum fetal monitoring
Mariana Rei1, Sara Tavares2, Pedro Pinto3
1Department of Obstetrics and Gynecology, Medical School, University of Porto, Portugal; S. Joao Hospital, Porto, Portugal; Institute of Biomedical Engineering (INEB), Porto, Portugal; Instituto de Investigação e Inovação em Saúde (i3s), Porto, Portugal.

Background:
Visual analysis of cardiotocographic (CTG) tracings has been shown to be prone to poor intra- and interobserver agreement when several interpretation guidelines are used, and this may have an important impact on the technology's performance.
Objectives:
The aim of this study was to evaluate agreement in CTG interpretation using the new 2015 FIGO guidelines on intrapartum fetal monitoring.
Study Design:
A pre-existing database of intrapartum CTG tracings was used to sequentially select 151 cases acquired with a fetal electrode, with duration exceeding 60minutes, and signal loss less than 15%. These tracings were presented to six clinicians, three with more than 5 years' experience in the labor ward, and three with 5 or less years' experience. Observers were asked to evaluate tracings independently, to assess basic CTG features: baseline, variability, accelerations, decelerations, sinusoidal pattern, tachysystole, and to classify each tracing as normal, suspicious or pathologic, according to the 2015 FIGO guidelines on intrapartum fetal monitoring. Agreement between observers was evaluated using the proportions of agreement (Pa), with 95% confidence intervals (95%CI).
Results:
A good interobserver agreement was found in the evaluation of most CTG features, but not bradycardia, reduced variability, saltatory pattern, absence of accelerations and absence of decelerations. For baseline classification Pa was 0.85 [0.82-0.90], for variability 0.82 [0.78-0.85], for accelerations 0.72 [0.68-0.75], for tachysystole 0.77 [0.74-0.81], for decelerations 0.92 [0.90-0.95], for variable decelerations 0.62 [0.58-0.65], for late decelerations 0.63 [0.59-0.66], for repetitive decelerations 0.73 [0.69-0.78], and for prolonged decelerations 0.81 [0.77-0.85]. For overall CTG classification, Pa were 0.60 [0.56-0.64], for classification as normal 0.67 [0.61-0.72], for suspicious 0.54 [0.48-0.60] and for pathologic 0.59 [0.51-0.66]. No differences in agreement according to the level of expertise were observed, except in the identification of accelerations, where it was better in the more experienced group.
Conclusions:
A good interobserver agreement was found in evaluation of most CTG features and in overall tracing classification. Results were better than those reported in previous studies evaluating agreement in overall tracing classification. Observer experience did not appear to play a role in agreement.


Related Concept Videos
 01:27
Imaging Studies III: Computed Tomography
 01:14
Imaging Studies I: CT and MRI
Description of the Procedures
Computed Tomography (CT) scan:
Computed Tomography (CT) scans use X-ray technology to generate detailed images of bones, organs, and tissues. During the scan, the patient lies on a moving table...
 01:28
Imaging Studies for Cardiovascular System V: CT
 01:25
Imaging Studies for Cardiovascular System VI: Calcium -Scoring CT
 01:10
Computed Tomography
The technique was invented in the 1970s and is based on the principle that as X-rays pass through the body, they are absorbed or reflected at different levels. In the technique, a patient lies on a motorized platform while a computerized axial tomography (CAT) scanner rotates...
 01:30
Radiological Investigation I: X-ray and CT