Related Experiment Video
Updated: Aug 18, 2026
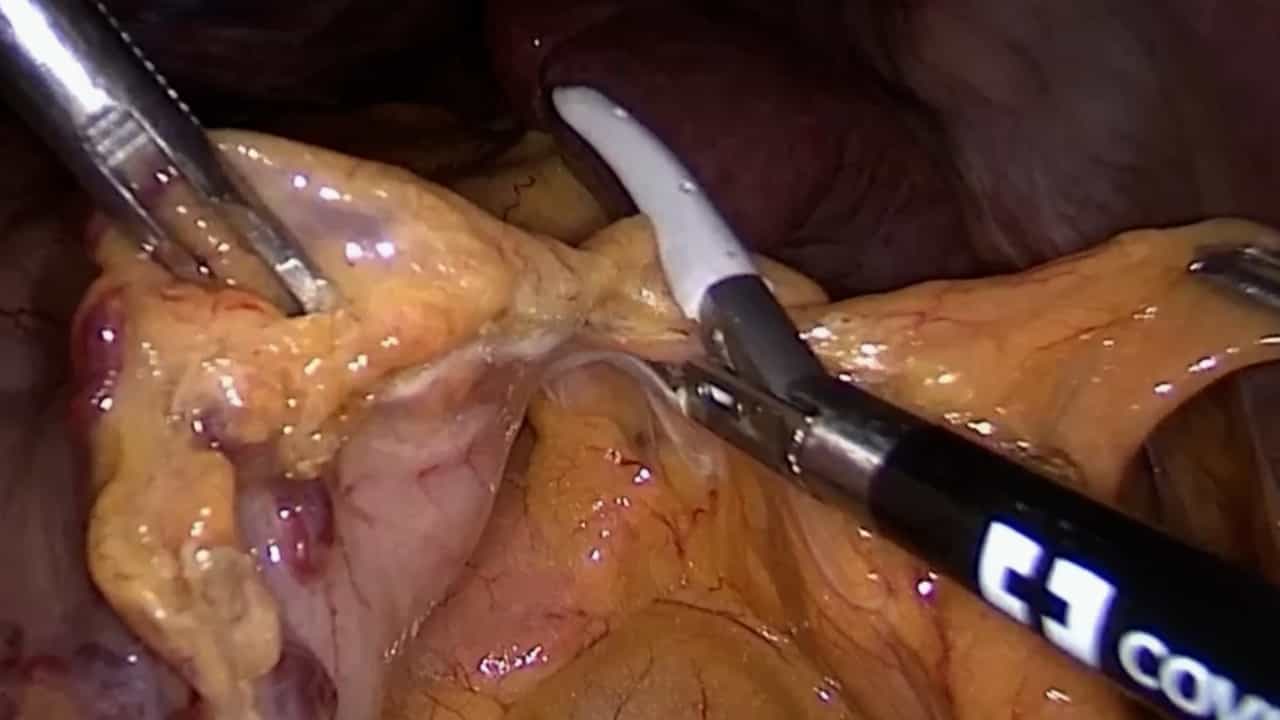

Application of Laparoscopic Partial Splenectomy with Total Blood Flow Occlusion in Benign Splenic Lesions
Published on: December 20, 2024
Laparoscopic azygoportal disconnection with and without splenectomy for portal hypertension
Dou-Sheng Bai1, Jian-Jun Qian1, Ping Chen1
1Department of Hepatobiliary Surgery, Clinical Medical College of Yangzhou University, 98 West Nantong Rd, Yangzhou, Jiangsu 225000, China.

Introduction:
Laparoscopic splenectomy and azygoportal disconnection (LSD) has been reported to be safe, feasible, and minimally invasive for cirrhotic patients with portal hypertension. There is still controversy as to whether it is necessary to perform synchronous splenectomy for patients with moderate hypersplenism who undergo azygoportal disconnection for esophagogastric variceal hemorrhage (EGVB).
Methods:
We retrospectively evaluated the outcomes in 51 cirrhotic patients with EGVB and moderate hypersplenism (PLT ≥50 × 109/L) who underwent LSD (n = 28) or laparoscopic azygoportal disconnection (LD) (n = 23) between January 2014 and October 2015. Their demographic, intraoperative, and postoperative variables were compared.
Results:
LSD and LD were successful in all the patients. When compared with LSD, LD had a significantly shorter operation time, less intraoperative blood loss, shorter postoperative hospital stay, fewer days of postoperative body temperature >38.0 °C, lower rate of fever postoperatively, and lower C-reactive protein concentration and procalcitonin concentration on postoperative day (POD) 7 (all P < 0.05). The incidences of portal vein system thrombosis in the LD group on PODs 7, 30, and 90 were significantly lower than those in the LSD group at all the time points (all P < 0.05). According to the postoperative serum proportions of CD4+ and CD8+ and the CD4+/CD8+ ratio (all P < 0.05), the LSD group had significantly lower immune function than the LD group on POD 90.
Conclusions:
LD is safe and effective for EGVB with moderate hypersplenism secondary to portal hypertension in selected patients.


