Related Experiment Video
Updated: Mar 15, 2026


Growing a Cystic Fibrosis-Relevant Polymicrobial Biofilm to Probe Community Phenotypes
Published on: April 19, 2024
Bayesian Estimation of Tobramycin Exposure in Patients with Cystic Fibrosis
Michael A Barras1,2, David Serisier3, Stefanie Hennig2
1Pharmacy Department, Mater Health Services, South Brisbane, Queensland, Australia michael.barras@health.qld.gov.au.

Abstract:
Fixed tobramycin (mg/kg) dosing is often inappropriate in patients with cystic fibrosis (CF), as pharmacokinetics are highly variable. The area under the concentration-time curve (AUC) is an exposure metric suited to monitoring in this population. Bayesian strategies to estimate AUC have been available for over 20 years but are not standard practice in the clinical setting. To assess their suitability for use in clinical practice, three AUC estimation methods using limited sampling were compared to measured true exposure by using intensive sampling tobramycin data. Adults prescribed once daily intravenous tobramycin had eight concentrations taken over 24 h. An estimate of true exposure within one dosing interval was calculated using the trapezoidal method and compared to three alternate estimates determined using (i) a two-sample log-linear regression (LLR) method (local hospital practice); (ii) a Bayesian estimate using one concentration (AUC1); and (iii) a Bayesian estimate using two concentrations (AUC2). Each method was evaluated against the true measured exposure by a Bland-Altman analysis. Twelve patients with a median (range) age and weight of 25 (18 to 36) years and 66.5 (51 to 76) kg, respectively, were recruited. There was good agreement between the true exposure and the three alternate estimates of AUC, with a mean AUC bias of <10 mg/liter · h in each case, i.e., -8.2 (LLR), 3.8 (AUC1), and 1.0 (AUC2). Bayesian analysis-based and LLR estimation methods of tobramycin AUC are equivalent to true exposure estimation. All three methods may be suitable for use in the clinical setting; however, a one-sample Bayesian method may be most useful in ambulatory patients for which coordinating blood samples is difficult. Suitably powered, randomized clinical trials are required to assess patient outcomes.
More Related Videos
 09:26
Antibiotic Efficacy Testing in an Ex vivo Model of Pseudomonas aeruginosa and Staphylococcus aureus Biofilms in the Cystic Fibrosis Lung
Published on: January 22, 2021
 07:16
Development of a Polymicrobial Colony Biofilm Model to Test Antimicrobials in Cystic Fibrosis
Published on: September 20, 2024
Related Concept Videos
 01:15
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
 01:28
Pulmonary Tuberculosis V
Latent tuberculosis infection occurs when TB bacteria are present in a person's body, but are not causing illness or symptoms. It is not contagious, and preventive treatment is crucial to avoid the...
 01:20
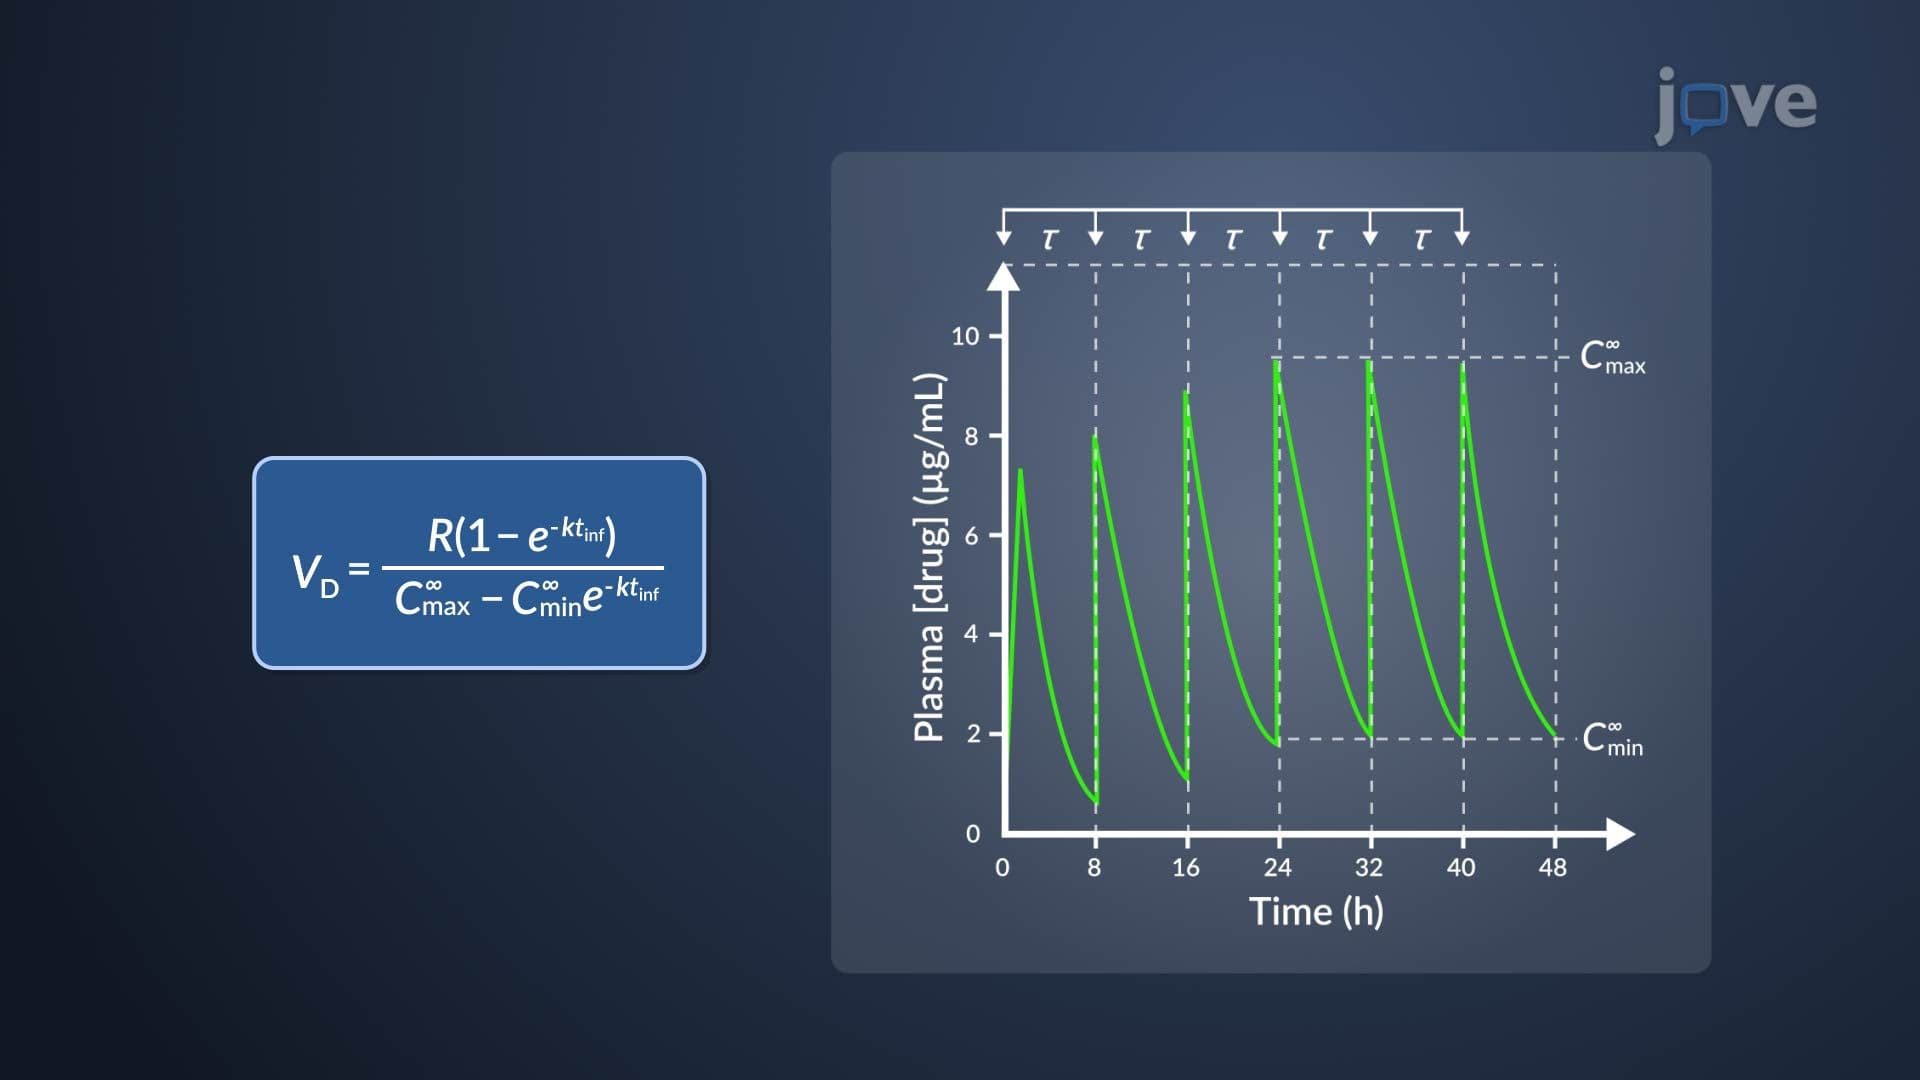
Estimation of k and VD of Aminoglycosides
 01:01
Dosage Regimens: Partial Pharmacokinetic Parameters
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...
 01:24
Cystic Fibrosis: Management
Sinus disease and chronic...