Related Experiment Video
Updated: Mar 15, 2026
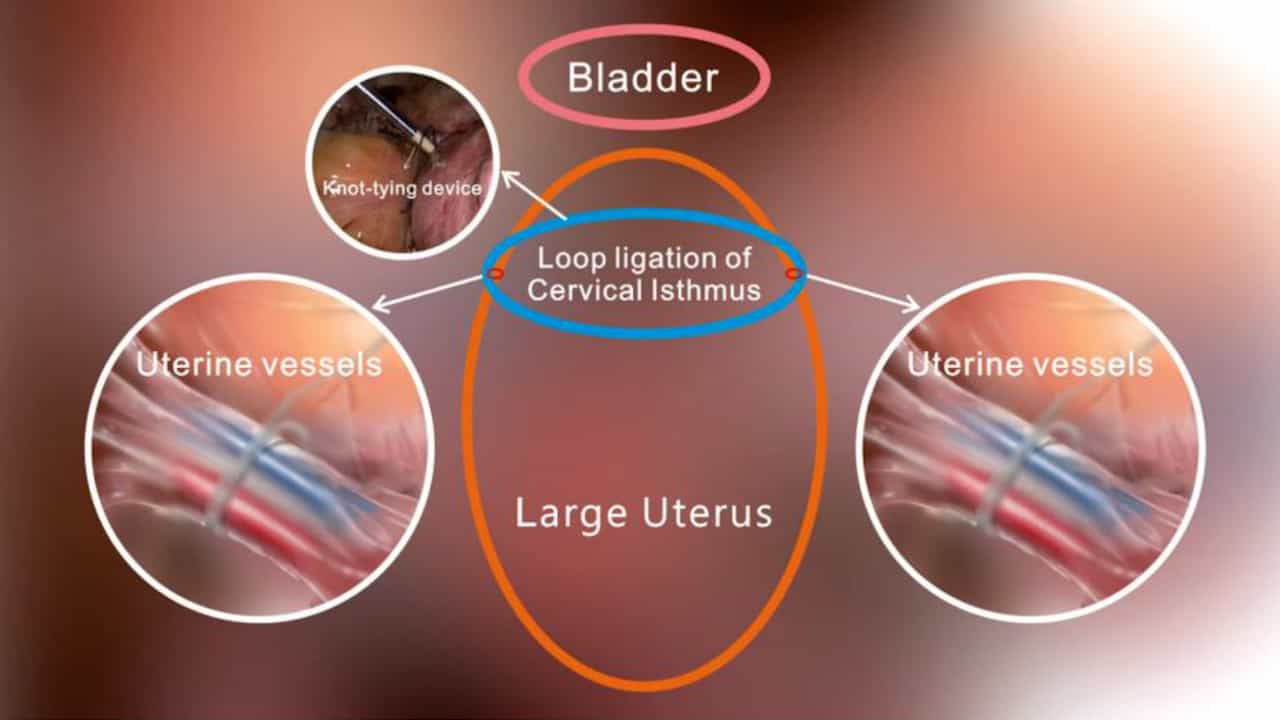

Laparoscopic Extracorporeal Knot-Tying for Uterine Vessel Occlusion during Hysterectomy with Cervical Cerclage in Large Uteri
Published on: September 12, 2025
Major obstetric hemorrhage
1Department of Anesthesia and Intensive Care, Hôpital Antoine-Beclere, Université Paris-Sud, AP-HP, 157, rue de la Porte-de-Trivaux, BP 405, 92141 Clamart cedex, France.

Abstract:
Major obstetric hemorrhage is a challenge for anesthesiologists because it remains responsible for over 10% of maternal deaths in high-income countries. A standardized multidisciplinary management, described in locally validated protocols and based on international guidelines is mandatory to prevent these deaths. The first difficulty relies on the systematic underestimation of the bleeding. Collection bags must be used to facilitate the diagnosis and therefore rapid management. The etiologies in antenatal or postpartum must be well-known in order to be treated adequately. A rapid recourse to prostaglandins (sulprostone in France) may reverse uterine atony. Invasive approach with surgery or radiology should be promptly implemented (uterine artery or internal iliac artery ligations±uterus plication) and hysterectomy should then be timely considered. Simultaneously, early and aggressive resuscitation with large-bore venous accesses should be implemented for rapid and massive transfusion (4:4:1 RBC:FFP:platelets ratio), along with an early use of fibrinogen concentrates and tranexamic acid. This transfusion strategy may be then guided by thromboelastography or thromboelastometry and bedside hemoglobin measurements. Activated factor VII remains indicated only before or after hysterectomy in case of uncontrolled bleeding. Management of placentation abnormalities (placenta previa, accreta, increta, percreta) must be well mastered as these etiologies may generate cataclysmic hemorrhages that can be and have to be anticipated.
Related Concept Videos
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol...
 01:24
Blood Pressure Imbalances and Circulatory Shock
Blood Pressure: Hypertension and Hypotension
Normal blood pressure is 120/80 mm Hg. Elevated blood pressure is 120-129/under 80 mm Hg. Hypertension, warranting treatment at 130/80 mm Hg, is often asymptomatic and can lead to severe cardiovascular events, aneurysms, peripheral arterial disease, chronic renal disease, or cardiac...
 01:24
Disorders of Hemostasis
Thromboembolic Disorders
Two factors primarily cause thromboembolic conditions.
 01:17
Measurement of Blood Pressure
 01:30
Epistaxis
Etiology
Possible causes of this condition include high blood pressure, trauma, low humidity, upper respiratory tract infections, allergies, foreign bodies, nasal inhalation of corticosteroids or illicit drugs, excessive use of decongestant nasal sprays, facial or nasal surgery, anatomic malformation, tumors, or systemic...
 01:24
Esophageal Varices-I: Introduction