Related Experiment Video
Updated: Mar 15, 2026
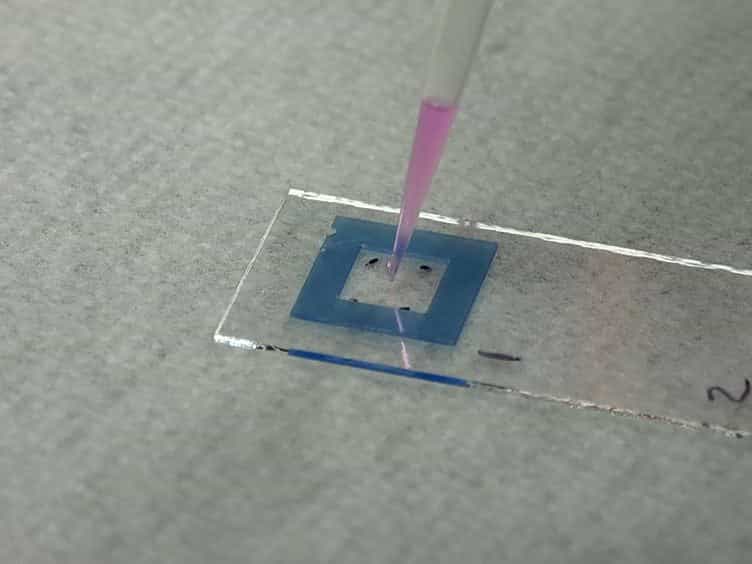

Demonstrating a Multi-drug Resistant Mycobacterium tuberculosis Amplification Microarray
Published on: April 25, 2014
In vivo Mycobacterium tuberculosis fluoroquinolone resistance emergence: a complex phenomenon poorly detected by
Christine Bernard1,2, Alexandra Aubry1,2, Aurélie Chauffour1
1Sorbonne Universités, UPMC Univ Paris 06, Inserm, Centre d'Immunologie et des Maladies Infectieuses, UMR 1135, 91 Bld de l'hôpital, F-75013 Paris, France.

Objectives:
Heteroresistance, described both in terms of various point mutations resulting in different levels of resistance and in terms of a mixture of mutant and WT bacilli, is identified in up to one-third of fluoroquinolone (FQ)-resistant Mycobacterium tuberculosis isolates. Heteroresistance is a challenge for current phenotypic and genotypic susceptibility testing (DST) regimes. We aimed to compare the performances of different phenotypic and genotypic DST in the context of FQ heteroresistance by mimicking, in a murine model, the course of selection of FQ resistance during treatment.
Methods:
The capacity of different phenotypic DST [Lowenstein-Jensen (LJ) medium containing either 2 mg/L ofloxacin or 0.5, 1 or 2 mg/L moxifloxacin] and genotypic DST (gyrA/B Sanger sequencing) to detect FQ resistance was analysed.
Results:
Ninety-seven percent of mice harboured a heterogeneous population. The proportion of mice in which FQ resistance was detected varied according to the medium used (97% for 0.5 mg/L moxifloxacin, 80% for 2 mg/L ofloxacin, 47% for 1 mg/L moxifloxacin and 25% for 2 mg/L moxifloxacin). Compared with phenotypic DST, genotypic DST had a low sensitivity for detection of resistance (33%).
Conclusions:
Our study shows the in vivo complexity of FQ resistance emergence and the poor sensitivity of Sanger DNA sequencing for detection of heteroresistance. Our data support the use of 0.5 mg/L moxifloxacin in LJ for detection of FQ resistance, but not the recent increase in the ofloxacin critical concentration from 2 to 4 mg/L given in the WHO recommendations.

Related Concept Videos
 01:30
Development of Antibiotic Resistance
 01:26
Pulmonary Tuberculosis IV
Several diagnostic approaches are used to detect TB. The conventional method is the Tuberculin Skin Test (TST), also known as the Mantoux test. However, this method has...
 01:28
Pulmonary Tuberculosis II
Here is a detailed explanation of its pathophysiology:
Transmission: The process begins when a person inhales droplet nuclei containing M. tuberculosis. These are typically released into the air when an individual with pulmonary or...
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...
 01:28
Pulmonary Tuberculosis V
Latent tuberculosis infection occurs when TB bacteria are present in a person's body, but are not causing illness or symptoms. It is not contagious, and preventive treatment is crucial to avoid the...
 01:31
Pulmonary Tuberculosis III
The first classification is based on the development of the disease, and it includes the following categories: