Related Experiment Video
Updated: Mar 15, 2026
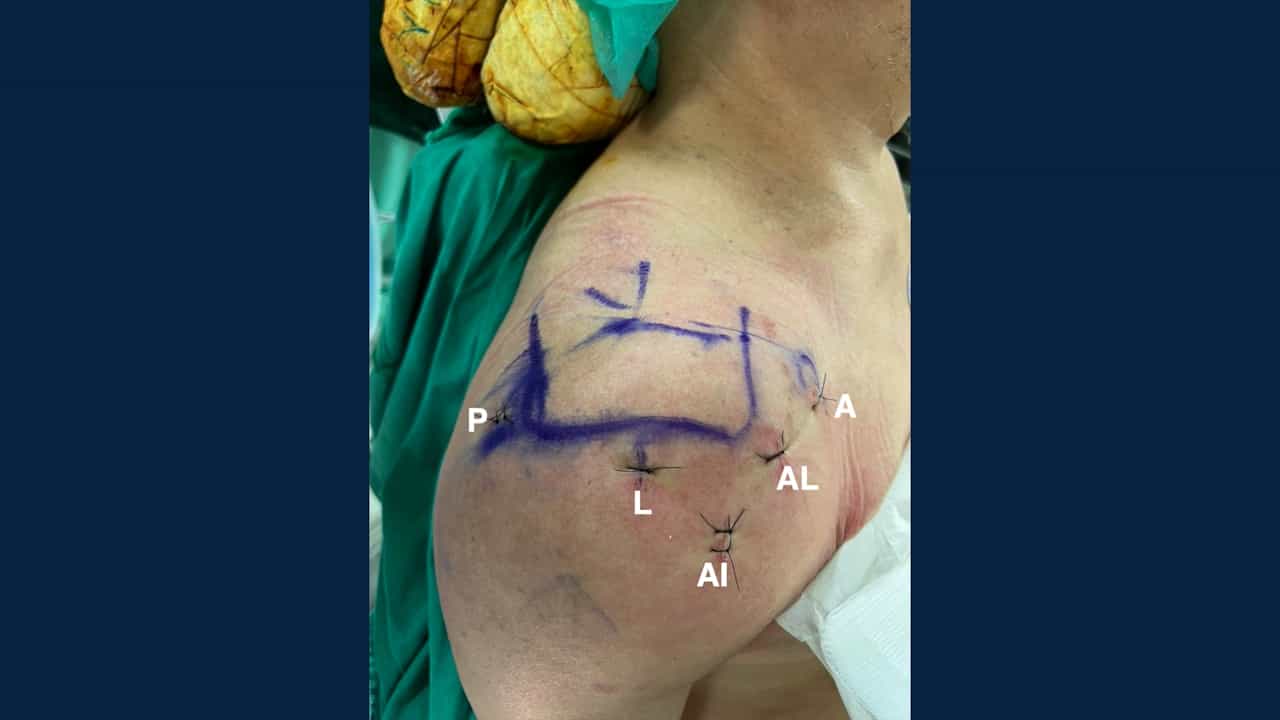

Knotless Independent Double-Row Repair and Biceps Augmentation for Anterosuperior Rotator Cuff Tears
Published on: January 23, 2026
Nonoperative Treatment of Type IIA Supracondylar Humerus Fractures: Comparing 2 Modalities
Lauren Roberts1, Jason Strelzow1, Emily K Schaeffer1,2
1Department of Orthopaedics, University of British Columbia.

Background:
Although the recommended treatment for Gartland types I and III supracondylar humeral fractures is well-established, the optimal treatment for type II fractures without rotational malalignment remains controversial, involving circumferential casting or closed reduction and pinning. Our institution uses pronated flexion-taping for Gartland type IIA fractures. This theoretically removes external pressure secondary to circumferential casting, potentially decreasing risks of compartment syndrome and mitigating loss of reduction with extension while maintaining optimal flexion position for reduction. To our knowledge, these modalities have not yet been compared.
Methods:
A retrospective chart review was performed to compare flexion-taping with cuff-and-collar immobilization versus traditional above-elbow casting at 90 to 100 degrees. It was hypothesized that closed reduction and flexion-taping of type IIA supracondylar fractures under sedation in the emergency department would result in comparable, if not superior, maintenance of reduction measured radiographically using Baumann angle and the lateral humeral capitellar angle (LHCA). Charts from 2010 to 2015 were reviewed for all patients between 2 and 8 years of age with type IIA fractures treated with cast or taping.
Results:
A total of 39 patients were included with 16 in the cast group and 23 in the tape group. Mean age was 4.08±1.72 years across both groups. No significant change in either measure was seen at termination of immobilization (3 to 4 wk postreduction). Final lateral humeral capitellar angle in the taping group was 32.14±5.90 degrees compared with 28.23±7.27 degrees in the casting group (P=0.81). Final Baumann angle was 73.41±4.03 degrees in the taping group compared with 73.75±6.46 degrees (P=0.96). The only complication was a self-limiting rash experienced by 1 patient in the taping group.
Conclusions:
Both techniques were able to achieve and maintain adequate reduction in all cases with no significant difference in outcome measures. There were no major complications or conversions to surgical treatment. In this cohort, taping resulted in adequate reduction and safe immobilization for type IIA fractures comparable to cast immobilization. Further research will investigate clinical/radiographic outcomes on these patients to assess remodeling and function.
Level Of Evidence:
Level III-retrospective comparative study.
More Related Videos
 04:41
Treatment with Locking Intramedullary Nailing for Intertrochanteric Fracture of the Femur Utilizing a New Awl with a Distal Positioner
Published on: June 6, 2025
 04:19
Minimally Invasive Treatment for Thoracolumbar Burst Fracture Using Sagittal Alignment Screws and A Trauma Reduction Device
Published on: November 8, 2024
Related Concept Videos
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the...
 01:19
Bones of the Upper Limb: Humerus
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History: