Related Experiment Video
Updated: Mar 15, 2026


Establishment and Characterization of Three Afatinib-resistant Lung Adenocarcinoma PC-9 Cell Lines Developed with Increasing Doses of Afatinib
Published on: June 26, 2019
EGFR-Co-Mutated Advanced NSCLC and Response to EGFR Tyrosine Kinase Inhibitors
Megan B Barnet1, Sandra O'Toole2, Lisa G Horvath1
1Sydney Medical School, University of Sydney, Sydney, New South Wales, Australia; Department of Medical Oncology, Chris O'Brien Lifehouse, Camperdown, New South Wales, Australia.

Objectives:
The evolution of EGFR tyrosine kinase inhibitors (TKIs) has changed the landscape of disease for a subset of patients with NSCLC. Most patients with an EGFR mutation respond to these drugs; however, a proportion show limited or no tumor response. We explored the impact of co-mutation (double or multiple mutation), compared with a single mutation, of the EGFR gene on response to TKIs in a series of patients with metastatic NSCLC.
Methods:
We retrospectively analyzed the mutation profiles of nonsquamous NSCLC tested at Royal Prince Alfred Hospital between 2012 and 2015 by MassArray using the OncoCarta v1.0 panel. Patients with metastatic disease whose tumors had sensitizing EGFR mutation(s) were included. The primary end point was progression-free survival (PFS). We used the Kaplan-Meier method for PFS and overall survival; the log rank test was used to compare groups with and without co-mutation. Multivariable analysis was done for PFS; response rate was assessed using chi-square and logistic regression analysis.
Results:
A total of 62 patients were included, and of these, eight (12.9%) had a co-mutation. The median PFS and overall survival times were 11.5 and 26.3 months, respectively. Patients with EGFR co-mutation had a significantly shorter median PFS than those with a single mutation (5.7 months versus 12.3 months, p = 0.02). The response rate to TKIs was significantly worse in those with co-mutation compared with in those without co-mutation (38% versus 89%, p < 0.001).
Conclusions:
Taking into account the small number of patients in this study, PFS in patients with EGFR co-mutation appeared significantly shorter, and response rate significantly lower, than in patients with a single mutation. Data from multipanel testing may identify subgroups of patients who are likely to respond poorly to standard treatment. Clarification of these subgroups may improve patient care.
Insights
EGFR co-mutations in non-small cell lung cancer (NSCLC) significantly reduce response to tyrosine kinase inhibitors (TKIs). Patients with EGFR co-mutation experienced shorter progression-free survival and lower response rates compared to those with single EGFR mutations.
Area of Science:
- Oncology
- Genetics
- Pharmacology
Background:
- Tyrosine kinase inhibitors (TKIs) targeting EGFR mutations have improved outcomes for non-small cell lung cancer (NSCLC) patients.
- However, a subset of patients exhibits limited or no response to these targeted therapies.
Purpose of the Study:
- To investigate the impact of EGFR co-mutations (multiple genetic alterations) versus single EGFR mutations on TKI treatment response in metastatic NSCLC.
- To identify patient subgroups with potentially poorer responses to standard TKI therapy.
Main Methods:
- Retrospective analysis of mutation profiles in 62 metastatic NSCLC patients with sensitizing EGFR mutations.
- Utilized MassArray OncoCarta panel for mutation testing.
- Progression-free survival (PFS) and overall survival analyzed using Kaplan-Meier and log-rank tests.
- Response rates assessed via chi-square and logistic regression.
Main Results:
- Eight patients (12.9%) presented with EGFR co-mutations.
- Patients with EGFR co-mutation showed significantly shorter median PFS (5.7 vs. 12.3 months, p=0.02) and lower response rates (38% vs. 89%, p<0.001) to TKIs.
- Median PFS and overall survival for all patients were 11.5 and 26.3 months, respectively.
Conclusions:
- EGFR co-mutation is associated with significantly poorer outcomes, including shorter PFS and reduced response rates to TKIs in NSCLC patients.
- Multipanel genetic testing can identify subgroups of patients likely to respond poorly to standard EGFR-TKI treatment.
- Clarifying these subgroups is crucial for improving patient care and treatment strategies.
More Related Videos
Related Concept Videos
 02:38
Mitogens and the Cell Cycle
 02:57
Targeted Cancer Therapies
There are several types of targeted therapies against...
 01:00
Enzyme-linked Receptors
Neurotrophin (NT) receptors are a family of RTKs, including trkA, trkB, and trkC (tropomyosin-related kinase) receptors. TrkA is specific for nerve growth factor (NGF), neurotrophin-6, and neurotrophin-7. TrkB binds...
 01:26
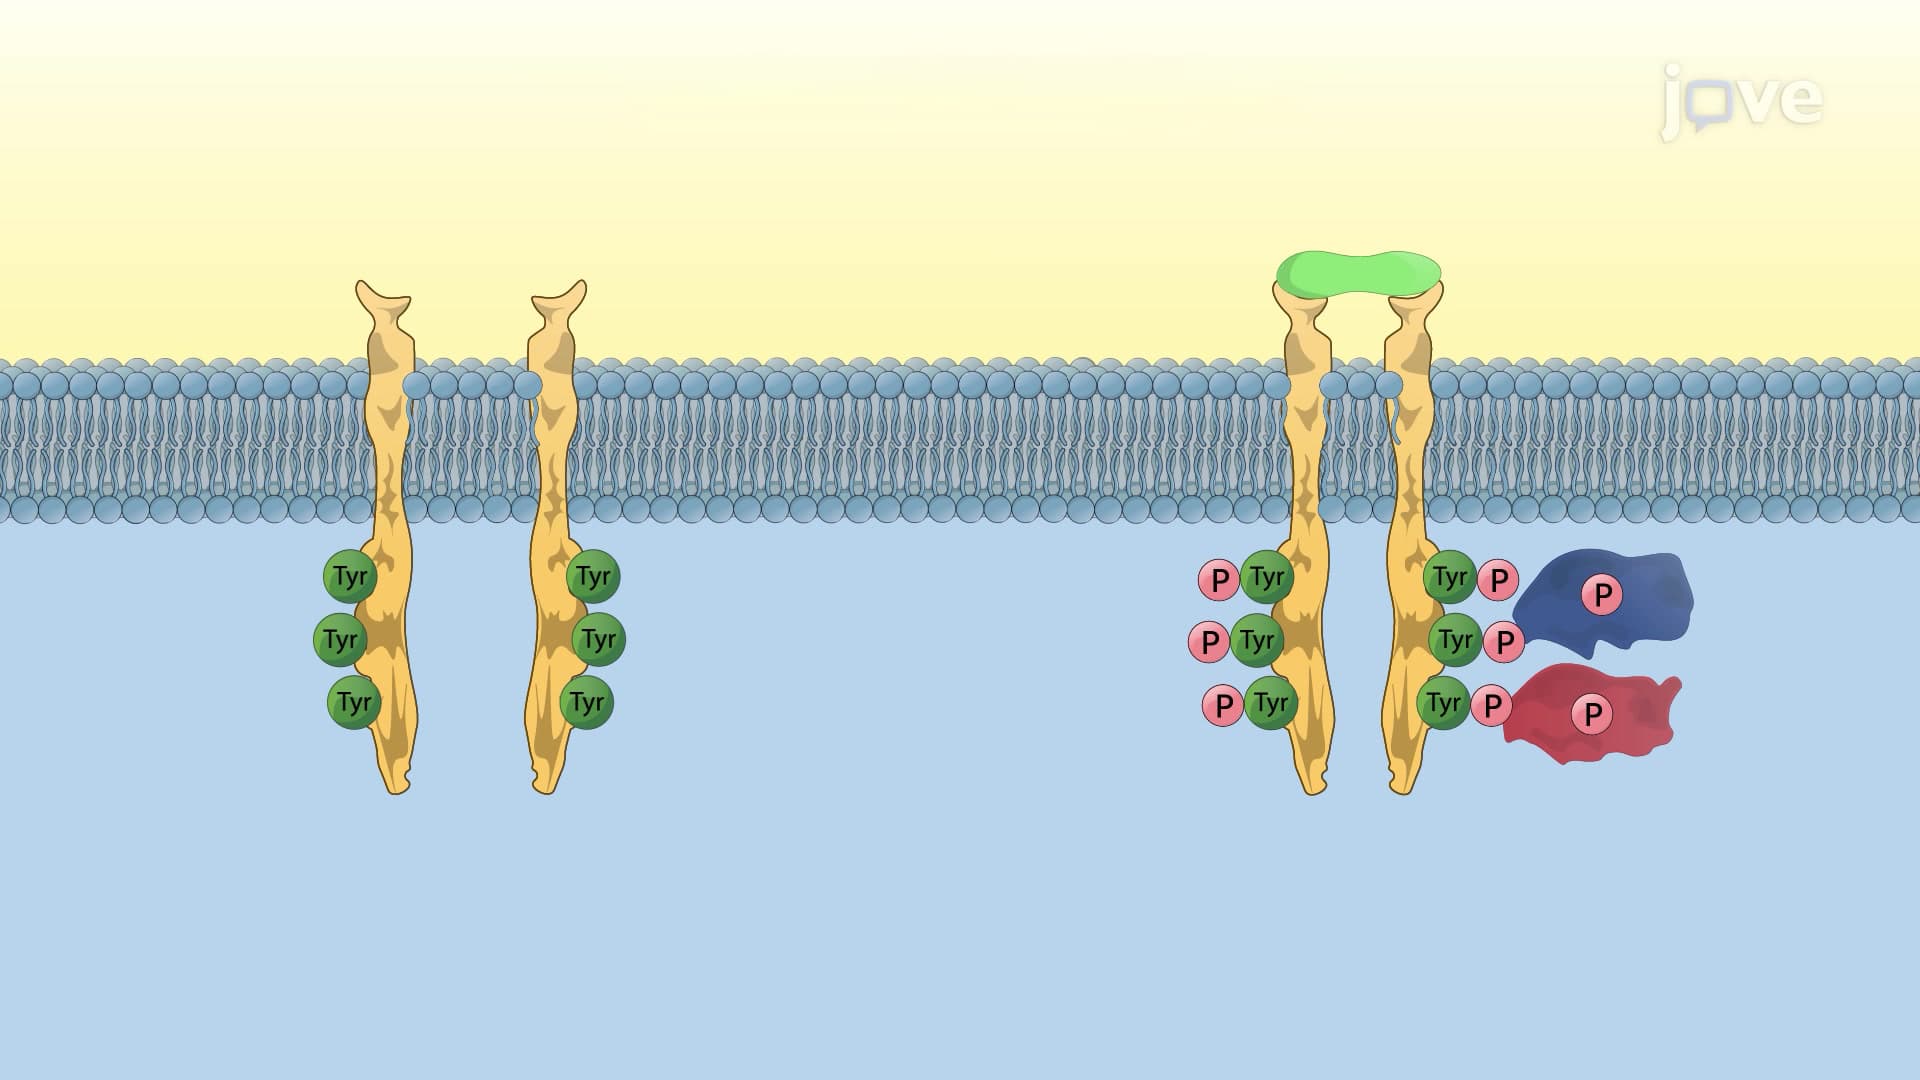
Receptor Tyrosine Kinases
 01:26
Treatment for Pulmonary Arterial Hypertension: Receptor Tyrosine Kinase Inhibitors and Calcium Channel Blockers
TKIs, such as imatinib (Gleevec), are particularly effective in tackling the growth and mitogenic factors that become upregulated in PAH patients. These factors contribute to the...
 02:18
Cancer