Related Experiment Video
Updated: Mar 14, 2026


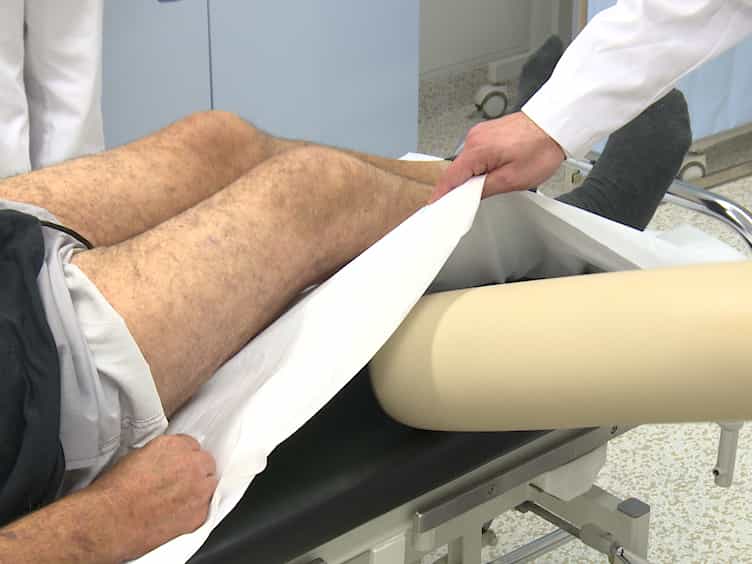
Knee Arthrocentesis in Adults
Published on: February 25, 2022
Infection-Related Death among Persons with Refractory Juvenile Idiopathic Arthritis

Insights
Children with severe juvenile idiopathic arthritis (JIA) face high mortality risks from infections. Aggressive immunosuppressive therapies, including biological DMARDs, increase susceptibility to fatal bacterial and viral infections in JIA patients.
Area of Science:
- Pediatric Rheumatology
- Infectious Diseases
- Clinical Immunology
Background:
- Juvenile idiopathic arthritis (JIA) is a chronic autoimmune disease in children.
- Refractory JIA often requires intensive immunosuppressive therapies, including biological disease-modifying antirheumatic drugs (DMARDs).
- These treatments increase the risk of severe infections and mortality in pediatric patients.
Observation:
- A study reviewed four pediatric deaths related to JIA between 1994 and 2013.
- Three deaths resulted from severe bacterial sepsis (coagulase-negative Staphylococcus, α-hemolytic Streptococcus) associated with central venous catheters.
- One death was attributed to disseminated adenovirus and Epstein-Barr virus infection.
Findings:
- All four deceased children had active, refractory JIA.
- They were undergoing long-term treatment with multiple conventional and biological DMARDs.
- Two patients died while on high-dose corticosteroids, methotrexate, and anti-tumor necrosis factor-α agents; two died during hematopoietic stem cell transplantation.
Implications:
- Severe infections pose a significant mortality risk in children with refractory JIA.
- Close monitoring for infections is crucial for children with JIA on immunosuppressive therapy.
- Accurate reporting of severe infections and deaths is vital for disease surveillance and improved patient outcomes.
Abstract:
Severe infections are emerging as major risk factors for death among children with juvenile idiopathic arthritis (JIA). In particular, children with refractory JIA treated with long-term, multiple, and often combined immunosuppressive and antiinflammatory agents, including the new biological disease-modifying antirheumatic drugs (DMARDs), are at increased risk for severe infections and death. We investigated 4 persons with JIA who died during 1994-2013, three of overwhelming central venous catheter-related bacterial sepsis caused by coagulase-negative Staphylococus or α-hemolytic Streptococcus infection and 1 of disseminated adenovirus and Epstein-Barr virus infection). All 4 had active JIA refractory to long-term therapy with multiple and combined conventional and biological DMARDs. Two died while receiving high-dose systemic corticosteroids, methotrexate, and after recent exposure to anti-tumor necrosis factor-α biological DMARDs, and 2 during hematopoietic stem cell transplantation procedure. Reporting all cases of severe infections and especially deaths in these children is of paramount importance for accurate surveillance.
More Related Videos

Related Concept Videos
 01:26
Factors Affecting the Risk of Infection
The integrity and count of the white blood cells help the body resist pathogens and fight infection. When impaired, it reduces the body's resistance to pathogens. The acidic pH levels of the gastrointestinal, genitourinary tracts, and skin...
 01:23
Rheumatic Heart Disease I: Introduction
 01:25
Immunodeficiency Diseases
There are three main causes of immunodeficiency...
 01:25
Endocarditis II: Clinical Features of Infective Endocarditis
 01:18
Endocarditis III: Medical Management
 01:25
Endocarditis I: Introduction