Related Experiment Video
Updated: Mar 14, 2026


Multiplex Therapeutic Drug Monitoring by Isotope-dilution HPLC-MS/MS of Antibiotics in Critical Illnesses
Published on: August 30, 2018
Standard dosing of piperacillin and meropenem fail to achieve adequate plasma concentrations in ICU patients
J Petersson1,2, C G Giske3,4, E Eliasson5,6
1Function Perioperative Medicine and Intensive Care, Karolinska University hospital Solna, Stockholm, Sweden. johan.petersson@karolinska.se.

Background:
Controversies remain regarding optimal dosing and the need for plasma concentration measurements when treating intensive care patients with beta-lactam antibiotics.
Methods:
We studied ICU patients treated with either antibiotic, excluding patients on renal replacement therapy. Antibiotic concentrations were measured at the mid and end of the dosing interval, and repeated after 2-3 days when feasible. Glomerular filtration rate (GFR) was estimated from plasma creatinine and cystatin C, GFR calculated from cystatin C (eGFR) and measured creatinine clearance (CrCl). Measured concentrations were compared to the clinical susceptible breakpoints for Pseudomonas aeruginosa, 16 and 2 mg/l for piperacillin and meropenem respectively.
Results:
We analysed 33 and 31 paired samples from 20 and 19 patients treated with piperacillin-tazobactam and meropenem respectively. Antibiotic concentrations at the mid and end of the dosing interval were for piperacillin, 27.0 (14.7-52.9) and 8.6 (2.7-30.3); and for meropenem, 7.5 (4.7-10.2) and 2.4 (1.0-3.5). All values median (interquartile range) and concentrations in mg/l. The percentage of measured concentrations below the breakpoint at the mid and end of the dosing interval were for piperacillin, 27% and 61%; and for meropenem, 6% and 48%. Lower estimates of GFR were associated with higher concentrations but concentrations varied greatly between patients with similar GFR. The correlation with terminal concentration half-life was similar for eGFR and CrCl.
Conclusions:
With standard doses of meropenem and piperacillin-tazobactam, plasma concentrations in ICU patients vary > 10-fold and are suboptimal in a significant percentage of patients. The variation is large also between patients with similar renal function.
Insights
Plasma concentrations of piperacillin-tazobactam and meropenem vary significantly in intensive care unit (ICU) patients. Standard dosing leads to suboptimal antibiotic levels in a substantial percentage of patients, even with similar renal function.
Area of Science:
- Pharmacokinetics
- Infectious Diseases
- Critical Care Medicine
Background:
- Optimal dosing of beta-lactam antibiotics in intensive care units (ICUs) remains debated.
- The necessity of therapeutic drug monitoring for these antibiotics in critically ill patients is unclear.
Purpose of the Study:
- To evaluate plasma concentrations of piperacillin-tazobactam and meropenem in ICU patients.
- To compare measured antibiotic concentrations against established breakpoints for Pseudomonas aeruginosa.
Main Methods:
- Studied ICU patients receiving piperacillin-tazobactam or meropenem, excluding those on renal replacement therapy.
- Measured antibiotic concentrations at mid and end-dosing intervals, estimating glomerular filtration rate (GFR) using creatinine and cystatin C.
- Compared concentrations to susceptibility breakpoints of 16 mg/l for piperacillin and 2 mg/l for meropenem.
Main Results:
- Analyzed 33 and 31 samples from 20 and 19 patients, respectively.
- Observed significant inter-patient variability in concentrations (e.g., piperacillin: 27.0 mg/l mid, 8.6 mg/l end; meropenem: 7.5 mg/l mid, 2.4 mg/l end).
- Found 27% and 61% of piperacillin, and 6% and 48% of meropenem concentrations below breakpoints at mid and end-intervals, respectively.
Conclusions:
- Standard doses of piperacillin-tazobactam and meropenem result in >10-fold variations in plasma concentrations in ICU patients.
- A significant proportion of patients exhibit suboptimal antibiotic concentrations.
- High inter-patient variability in drug levels persists even among patients with similar renal function.
More Related Videos
 09:17
A Robust Pneumonia Model in Immunocompetent Rodents to Evaluate Antibacterial Efficacy against S. pneumoniae, H. influenzae, K. pneumoniae, P. aeruginosa or A. baumannii
Published on: January 2, 2017
 07:16
Development of a Polymicrobial Colony Biofilm Model to Test Antimicrobials in Cystic Fibrosis
Published on: September 20, 2024
Related Concept Videos
 01:28
Acute Pyelonephritis II: Diagnostic Studies and Management
 01:15
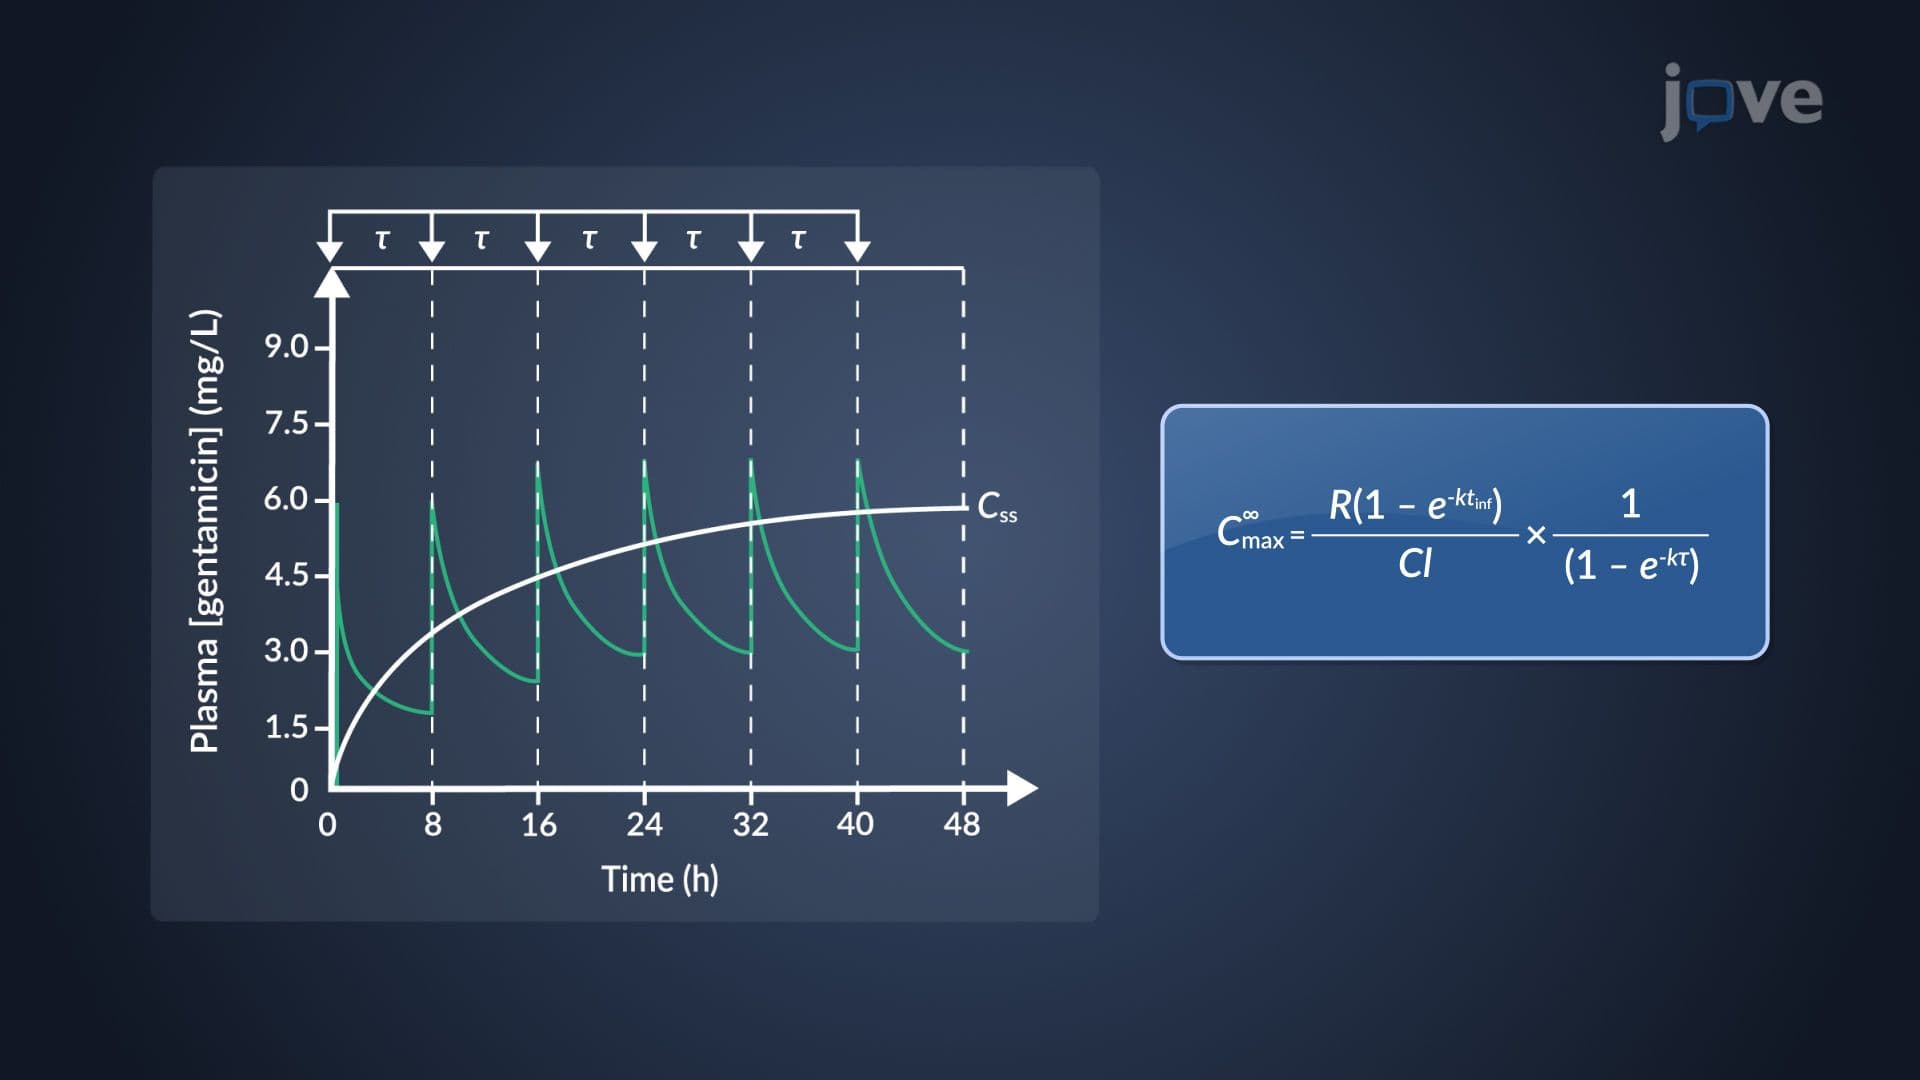
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
 01:28
Pneumonia IV: Management
Bacterial Pneumonia Treatment
For bacterial pneumonia, antibiotics serve as the cornerstone of therapy. Initial treatment often begins with empirical antibiotics, tailored to the anticipated causative organism and adjusted based on culture results. Key antibiotic choices include:
 01:24
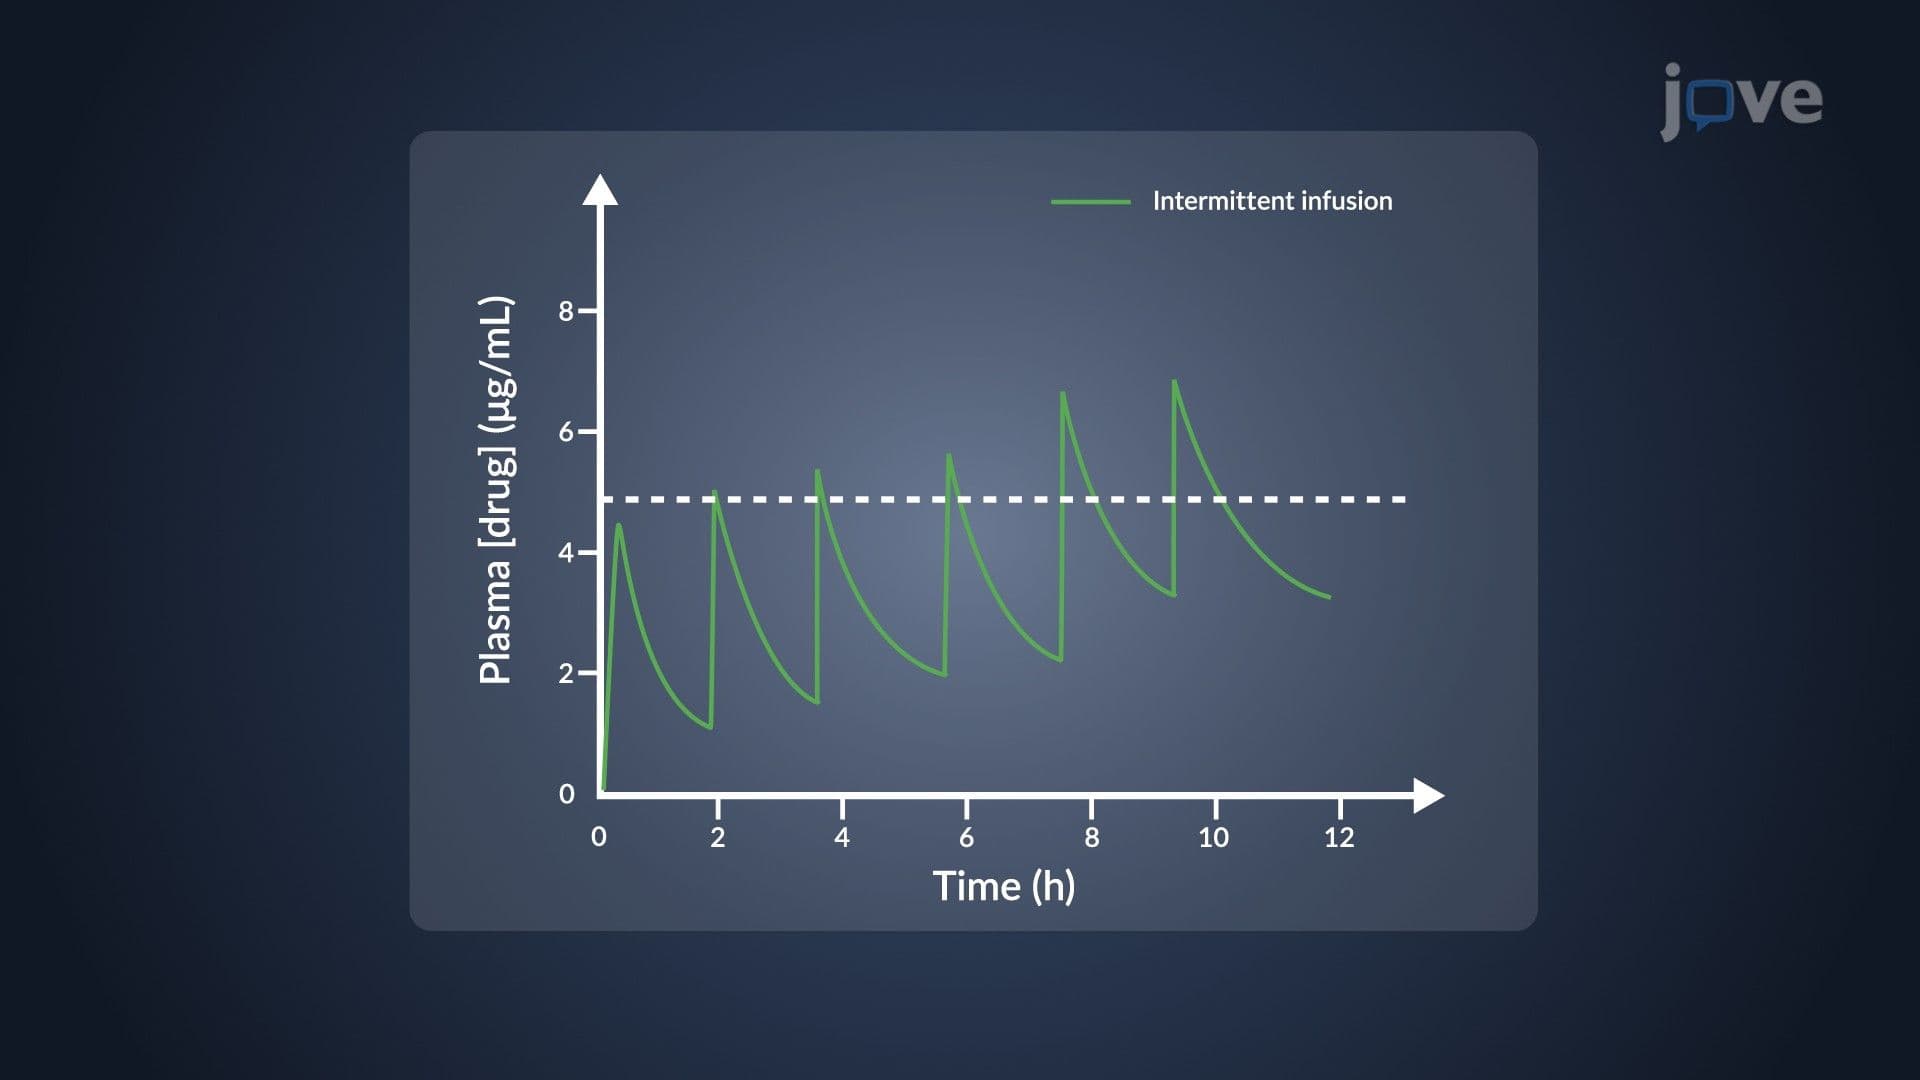
Drug Accumulation During Multiple Dosing: Intermittent IV Infusions
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
 01:19
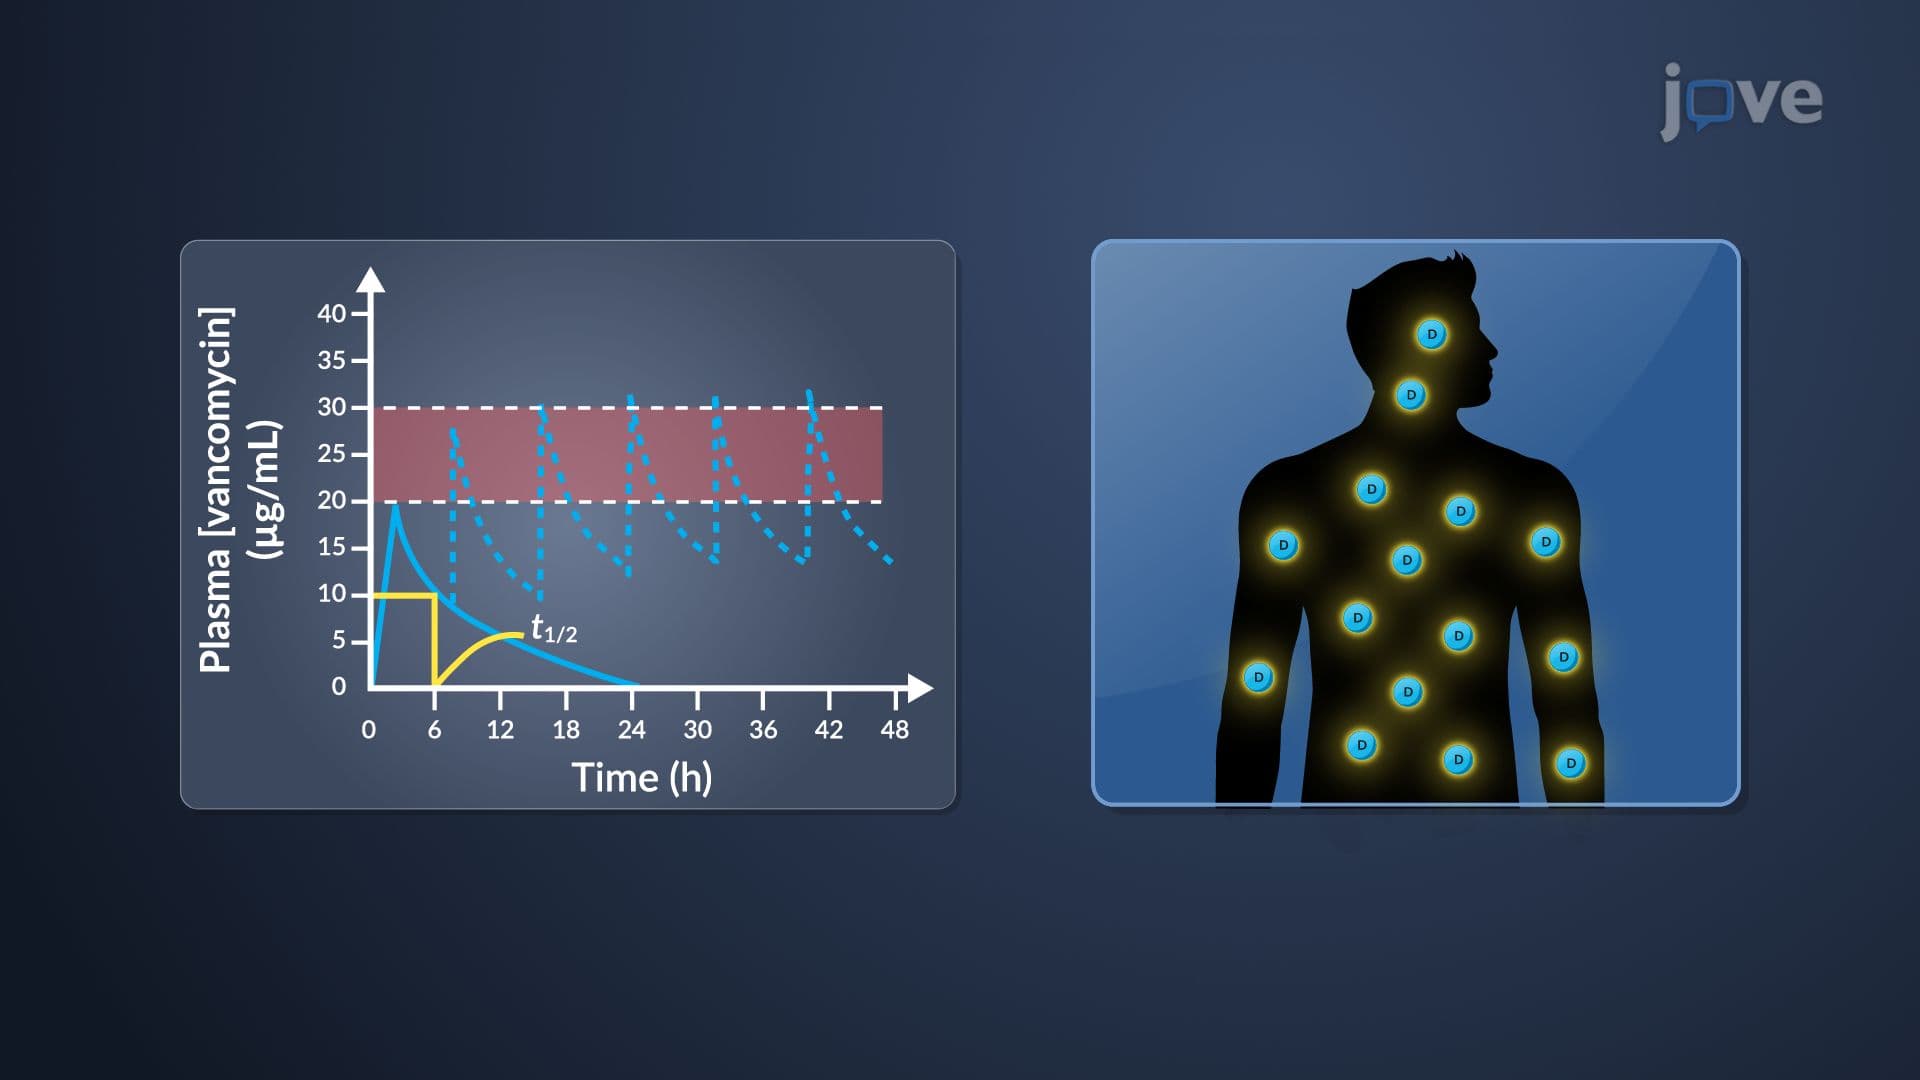
Dosage Interval and Administration Route: Determination Methods