Related Experiment Video
Updated: Mar 14, 2026
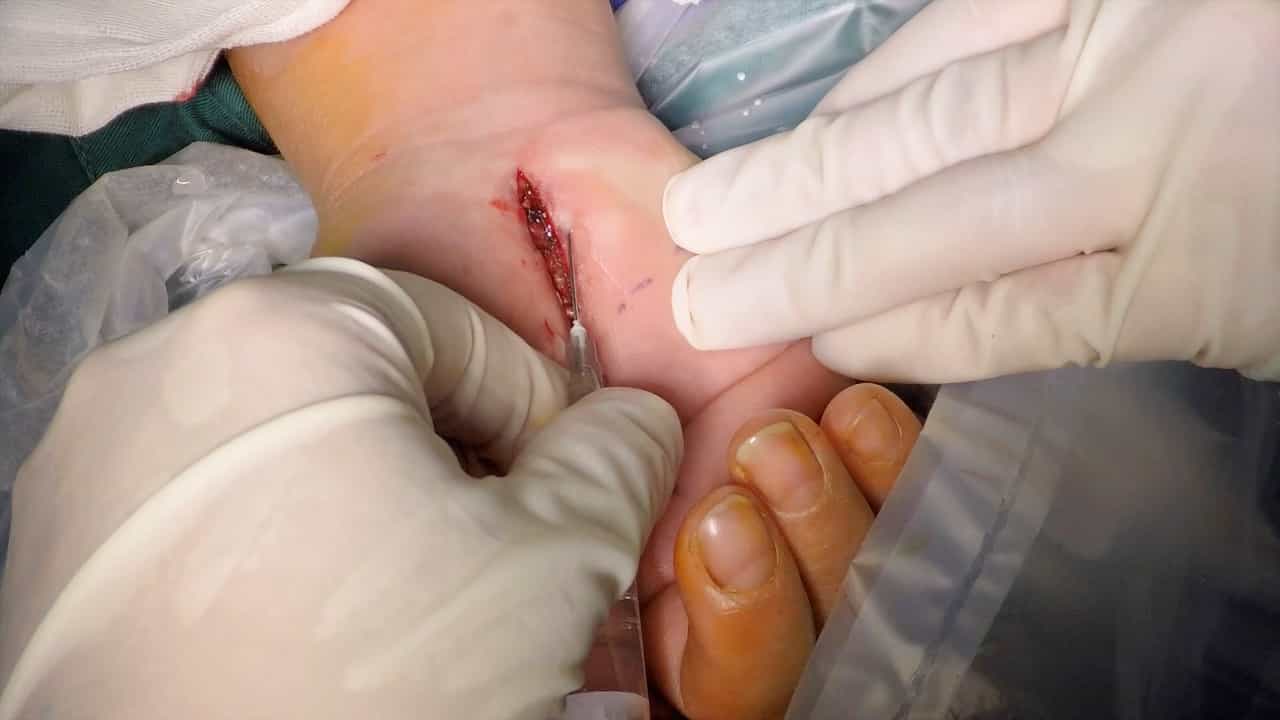

Metacarpal Small Incision for Carpal Tunnel Syndrome
Published on: April 5, 2024
An anatomical investigation of the superficial and deep palmar arches
S Singh, L Lazarus, B Z De Gama
1Department of Clinical Anatomy, School of Laboratory Medicine and Medical Sciences, College of Health Sciences, Westville Campus, University of KwaZulu Natal, Durban, South Africa, South Africa. satyapalk@ukzn.ac.za.

Background:
The superficial palmar arch (SPA) and deep palmar arch (DPA) provide the dominant vascular supply to the hand. The SPA is considered to be highly variable and can be classified as either complete or incomplete. The simplest definition states that the anastomosis between the vessels contributing to the arch represent a complete arch, while an incomplete arch is described as characterised by an absence of anastomosis between the vessels contributing to it. This study aimed to describe the anatomical landmarks, formation and branching patterns of the SPA and DPA. In this study, the SPA and DPA were dissected in 50 specimens (n = 100 adult hands), respectively.
Materials And Methods:
A complete SPA was observed in 92% of specimens and classified into three types. In Type A (44%), the SPA was formed by the anastomosis of the superficial palmar branch of the radial artery with the ulnar artery. Type B (46%) was formed by the ulnar artery alone and Type C (2%) was formed by anastomosis of the ulnar artery with the superficial palmar branch of the radial artery and the persistent median artery.
Results:
An incomplete SPA was observed in 8% of the specimens and divided into three types formed by the radial and ulnar arteries. The DPA was divided into five types viz. Type G (72%), where the DPA was formed by anastomosis of the deep palmar branch of the radial artery (DPBRA) with the deep palmar branch of the ulnar artery (DPBUA). Type H (12%), was formed by anastomosis of the DPBRA, the DBUA and the interosseous artery. Type I (8%), was formed by the anastomosis of the DPBRA with the superior and inferior DPBUA. Type J (4%), the deep ulnar artery had two branches whereby either one branch anastomosed with the DPBRA to form the DPA. Type K (4%), the DBUA exhibited two deep branches with one branch anastomosing with the DPBRA to complete the DPA.
Conclusions:
The interosseous artery anastomosed with either the DPA or the additional DPBUA. Knowledge of the variability of the SPA and DPA is crucial for safe and successful hand surgeries.
More Related Videos
 10:36
Vascularized Composite Hand Allograft Procurement and Preparation for Distal and Proximal Forearm Allotransplantation: A Stepwise Approach
Published on: May 23, 2025
 10:02
Visualization and Analysis of Pharyngeal Arch Arteries using Whole-mount Immunohistochemistry and 3D Reconstruction
Published on: March 31, 2020
Related Concept Videos
 01:16
Muscles of the Forearm that Move the Hand and Fingers
Anterior Compartment
The anterior compartment muscles originate from the humerus. They primarily function as flexors and are also known as flexor muscles. They typically insert on the carpals, metacarpals, and phalanges. The superficial layer includes the flexor carpi...
 01:12
Arteries of the Upper Limbs
 01:17
Veins of Upper Limbs
The deep venous system is primarily composed of the ulnar and radial veins. The ulnar vein, which drains the fingers through the superficial palmar venous arches, and the radial vein, which serves the palms via the deep palmar...
 01:09
Bones of the Upper Limb: Radius
The radius has a nail-shaped head, and a...
 01:10
The Arch of Aorta
Encircling the heart, the coronary arteries form a ring-like structure before...
 01:23
Assessment of the Abdomen III: Palpation