Related Experiment Video
Updated: Mar 14, 2026
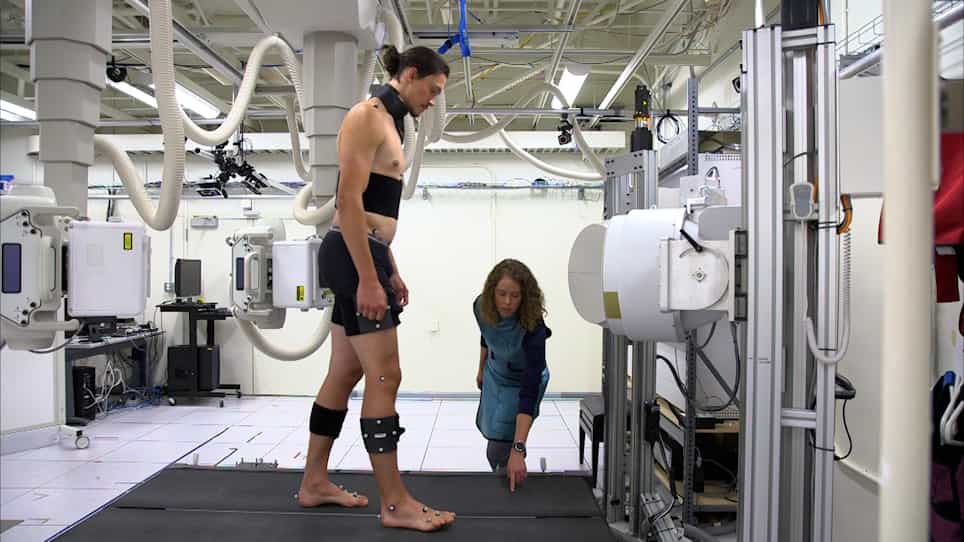

In Vivo Quantification of Hip Arthrokinematics during Dynamic Weight-bearing Activities using Dual Fluoroscopy
Published on: July 2, 2021
Hip stability during lengthening in children with congenital femoral deficiency
Mark Eidelman1, Julio J Jauregui2, Shawn C Standard3
1Ruth Children's Hospital, Rambam Health Care Campus, Haifa, Israel.

Insights
Hip instability, including subluxation and dislocation, is a significant risk during femoral lengthening for congenital femoral deficiency (CFD). Proximal femoral lengthening and acetabular dysplasia are key risk factors, necessitating careful management strategies.
Area of Science:
- Orthopedic surgery
- Pediatric orthopedics
- Limb reconstruction
Background:
- Congenital femoral deficiency (CFD) presents complex challenges in limb lengthening procedures.
- Hip instability, specifically subluxation and dislocation, poses a severe risk to hip function during femoral lengthening.
Purpose of the Study:
- To assess hip stability during femoral lengthening in children with Congenital Femoral Deficiency (CFD).
- To identify risk factors contributing to hip subluxation and dislocation in CFD patients undergoing limb lengthening.
Main Methods:
- Hip stability was evaluated in 69 children undergoing 91 femoral lengthenings for CFD (Paley types 1a and 1b).
- Pelvic osteotomies were performed in 33 patients prior to lengthening.
- Data on hip subluxation/dislocation, acetabular dysplasia, fixation methods, and surgical procedures were collected.
Main Results:
- Hip subluxation or dislocation occurred in 15% of lengthenings.
- Proximal femoral lengthening was a significant factor associated with hip subluxation.
- Patients with hip subluxation were more likely to have undergone monolateral fixation and the superhip procedure.
Conclusions:
- Key risk factors for hip instability include CFD severity, acetabular dysplasia, and proximal femoral lengthening.
- Routine pelvic osteotomy is recommended for Paley type 1b CFD patients, especially with distal lengthening, to mitigate hip instability risks.
Background:
Congenital femoral deficiency (CFD) is one of the most challenging and complex conditions for limb lengthening. We focused on the problem of hip instability during femoral lengthening because subluxation and dislocation are potentially catastrophic for hip function.
Methods:
We assessed for hip stability in 69 children (91 femoral lengthenings) who had CFD Paley type 1a (43 children) and 1b (26 children). The mean age at first lengthening was 6.4 years.
Results:
Hip subluxation/dislocation occurred during 14 (15 %) of 91 lengthenings. Thirty-three pelvic osteotomies were performed before lengthening in an attempt to stabilize hips. Thirteen patients (type 1a, eight; type 1b, five) had acetabular dysplasia at initiation of lengthening. One of the eight with type 1a experienced mild femoral head subluxation; four of the five with type 1b experienced three dislocations and one subluxation. Eight patients (type 1b) experienced hip instability although they had pelvic osteotomies. Proximal femoral lengthening was a significant factor for hip subluxation. Patients with hip subluxation more likely underwent monolateral fixation and the original superhip procedure. Age ±six years was not a contributing factor for hip instability.
Conclusions:
Important risk factors for hip instability during femoral lengthening are severity of CFD, residual acetabular dysplasia, and proximal femoral lengthening. We recommend routine performance of pelvic osteotomy for patients with Paley type 1b CFD and distal lengthening.
Level Of Evidence:
Therapeutic Level IV.
More Related Videos
 09:31
Individualized Stem-positioning in Calcar-guided Short-stem Total Hip Arthroplasty
Published on: February 27, 2018
 09:51
The Transition to an Anterior-Based Muscle Sparing Approach Improves Early Postoperative Function but is Associated with a Learning Curve
Published on: September 7, 2022
Related Concept Videos
 01:16
Bones of the Lower Limb: Femur and Patella
 01:23
Muscles that Move the Leg
Anterior Compartment
The quadriceps femoris, the most visible muscle of the anterior compartment, is integral for leg extension and thigh flexion. It is formed by merging four distinct muscles — the vastus lateralis, vastus medialis, vastus intermedius, and rectus femoris. The quadriceps tendon, a shared tendon of the four quadriceps muscles, is affixed...
 01:09
Changes in the Appendicular Skeleton with Age
Initially, the limb buds consist of a core of mesenchyme covered by a layer of ectoderm. The ectoderm at the end of the limb bud thickens to form a narrow crest called the apical ectodermal ridge. This ridge stimulates the underlying...
 01:23
Knee Joint
A total of seven ligaments support the knee joint. The patellar ligament, which is also attached to the quadriceps femoris...