Related Experiment Video
Updated: Mar 14, 2026


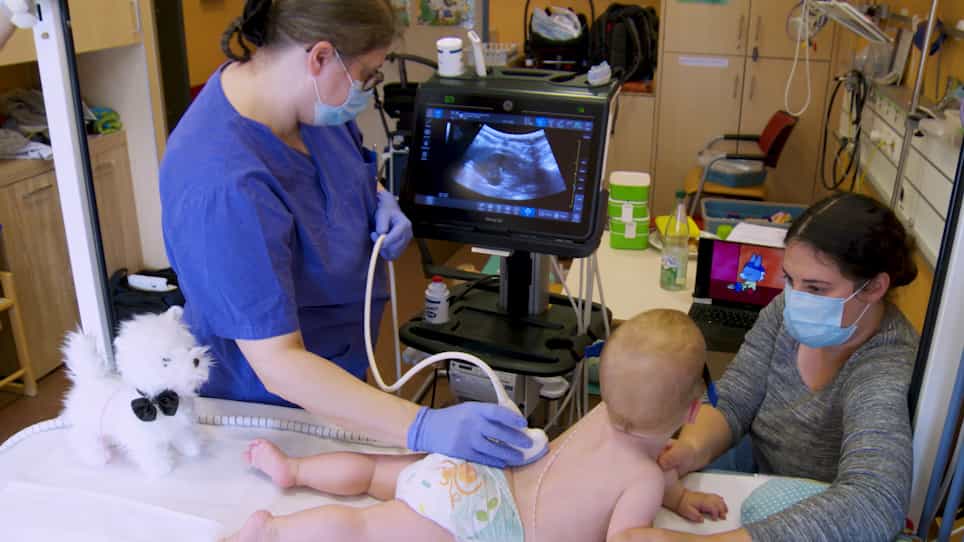
A Modified Sonographic Algorithm for Image Acquisition in Life-Threatening Emergencies in the Critically Ill Newborn
Published on: April 7, 2023
Current State of Pediatric Intensive Care and High Dependency Care in Nepal
Aayush Khanal1, Arun Sharma, Sangita Basnet
11Department of Pediatrics, Institute of Medicine, Tribhuvan University Teaching Hospital, Kathmandu, Nepal.2Division of Critical Care, Department of Pediatrics, Southern Illinois University School of Medicine, Springfield, IL.

Objectives:
To describe the state of pediatric intensive care and high dependency care in Nepal. Pediatric intensive care is now a recognized specialty in high-income nations, but there are few reports from low-income countries. With the large number of critically ill children in Nepal, the importance of pediatric intensive care is increasingly recognized but little is known about its current state.
Design:
Survey.
Setting:
All hospitals in Nepal that have separate physical facilities for PICU and high dependency care.
Patients:
All children admitted to these facilities.
Interventions:
None.
Measurements And Main Results:
A questionnaire survey was sent to the chief of each facility. Eighteen hospitals were eligible and 16 responded. Two thirds of the 16 units were established in the last 5 years; they had a total of 93 beds, with median of 5 (range, 2-10) beds per unit. All 16 units had a monitor for each bed but only 75% could manage central venous catheters and only 75% had a blood gas analyzer. Thirty two percent had only one functioning mechanical ventilator and another 38% had two ventilators, the other units had 3-6 ventilators. Six PICUs (38%) had a nurse-to-patient ratio of 1:2 and the others had 1:3 to 1:6. Only one institution had a pediatric intensive care specialist. The majority of patients (88%) came from families with an income of just over a dollar per day. All patients were self funded with a median cost of PICU bed being $25 U.S. dollars (interquartile range, 15-31) per day. The median stay was 6 (interquartile range, 4.8-7) days. The most common age group was 1-5. Sixty percent of units reported respiratory distress/failure as their primary cause for admission. Mortality was 25% (interquartile range, 20-35%) with mechanical ventilation and 1% (interquartile range, 0-5%) without mechanical ventilation.
Conclusions:
Pediatric intensive care in Nepal is still in its infancy, and there is a need for improved organization, services, and training.

Related Concept Videos
 01:30
Specialized Care Centers and Settings-II
Rural health centers are specialized care facilities in remote locations with very few medical personnel. The primary care providers who run the centers are mostly Registered Nurse Practitioners. Here, emergency treatment is provided to critically ill or injured patients before they are transferred to the closest hospital. Fortunately, due to advancement in technology, many rural healthcare facilities and professionals have easy access to diagnostic and treatment...
 01:30
Specialized Care Centers and Settings-I
Daycare centers
They provide several functions. Some facilities care for healthy newborns and children whose parents work, while others are medically focused and care for...
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
 01:21
Tertiary Healthcare System
 01:20
Acute Kidney Injury V: Interprofessional Care
 00:59
Hospitals-II
Nurses that work in...