Noninvasive ventilation during spontaneous breathing anesthesia: an observational study using electrical impedance tomography
Related Experiment Video
Updated: Mar 14, 2026
Monitoring Lung Function with Electrical Impedance Tomography in the Intensive Care Unit
Published on: September 6, 2024
Julien Bordes1, Philippe Goutorbe1, Pierre Julien Cungi1
1Department of Anesthesia and Intensive Care, Sainte Anne Military Teaching Hospital, Toulon, France.

Study Objective:
To assess the effects of noninvasive ventilation (NIV) during spontaneous breathing anesthesia on functional residual capacity and ventilation distribution.
Design:
Prospective and observational study.
Setting:
Operating room, military teaching hospital.
Patients:
Eighteen adult patients submitted to digestive endoscopic procedures under spontaneous breathing anesthesia.
Interventions:
Anesthetic management was standardized. Patients were submitted to combined digestive endoscopic procedures (gastric fibroscopy and colonoscopy) under spontaneous breathing anesthesia in lateral decubitus position. Anesthesia was induced with propofol intravenous 1 mg/kg. Repeated boluses of propofol were administered according to the patients' clinical needs during endoscopic procedures. Ventilation distribution and functional residual capacity were assessed by electrical impedance tomography.
Measurements:
Ventilation distribution was assessed by electrical impedance changes in left and right lung, and functional residual capacity changes were evaluated by measurement of end-expiratory lung impedance changes. Measures were performed before anesthesia induction, 5 minutes after anesthesia induction during gastric fibroscopy, at the end of gastric fibroscopy, 5 minutes after NIV application during colonoscopy, and at the end of colonoscopy.
Main Results:
In awake patients, tidal volume was primarily distributed to the dependent lung (57.5% vs 43.1%; P=.009). After anesthesia induction, we observed a shift of ventilation to the nondependent lung (43.1% before anesthesia, 58.9% after anesthesia; P=.002) and marked decrease in end-expiratory lung impedancemetry of -1.68UI (4.47). Noninvasive ventilation application resulted in a significant increase of end-expiratory lung impedancemetry of 1.33 (6.49) (P=.005) but did not impact ventilation distribution.
Conclusions:
This study showed that NIV application in pressure support mode during spontaneous breathing anesthesia increased functional residual capacity. Other studies are needed to evaluate the clinical impact of this technique during anesthesia, especially in patients with poor respiratory conditions.
More Related Videos
 05:39
Author Spotlight: A Non-Intubated Video-Assisted Thoracoscopic Surgery with Multimodal Analgesia and Sevoflurane Inhalation Anesthesia
Published on: May 26, 2023
 14:52
Recording Brain Electromagnetic Activity During the Administration of the Gaseous Anesthetic Agents Xenon and Nitrous Oxide in Healthy Volunteers
Published on: January 13, 2018
Related Concept Videos
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation...
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:14
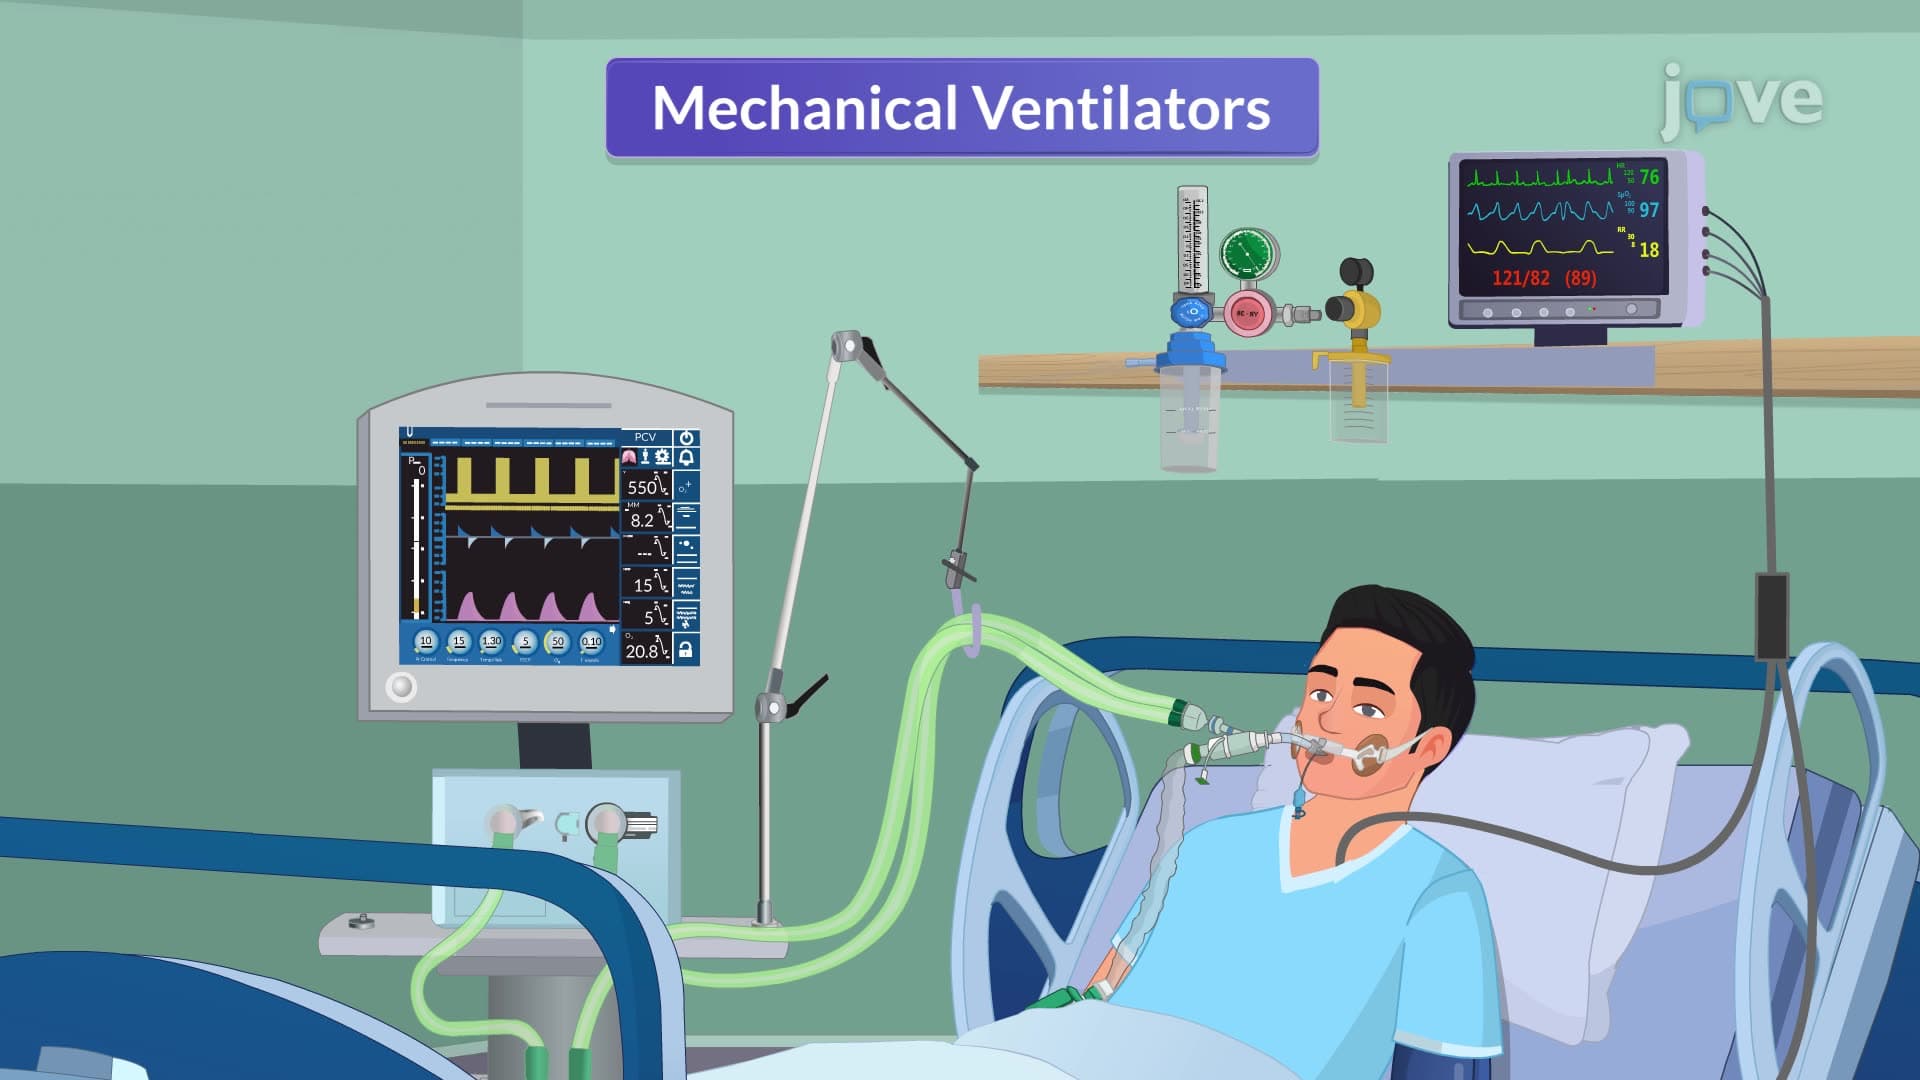
Ventilatory Modes
There are three ventilatory modes: full support, partial support, and spontaneous. These are described below.
Full Support Modes
Full support modes include controlled mechanical ventilation, continuous mandatory...