Related Experiment Video
Updated: Mar 14, 2026


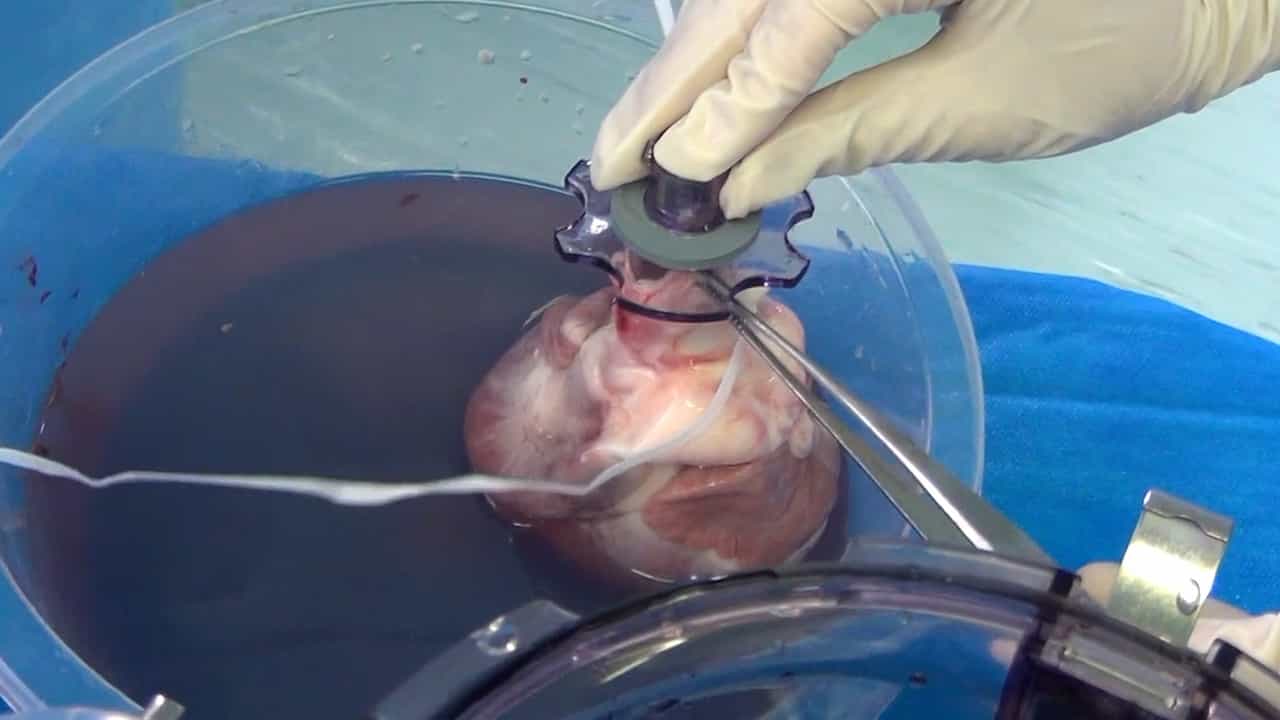
Implantation of Total Artificial Heart in Congenital Heart Disease
Published on: July 18, 2014
Hypoplastic left heart syndrome: from comfort care to long-term survival
Mouhammad Yabrodi1, Christopher W Mastropietro1
1Department of Pediatrics, Section of Critical Care, Riley Hospital for Children at Indiana University Health and Indiana University School of Medicine, Indianapolis, Indiana.

Insights
Hypoplastic left heart syndrome (HLHS) management evolved from supportive care to surgical interventions like the Norwood procedure. These advancements significantly improve survival rates for affected children.
Area of Science:
- Pediatric Cardiology
- Congenital Heart Disease Surgery
- Neonatal Intensive Care
Background:
- Hypoplastic Left Heart Syndrome (HLHS) historically had a poor prognosis, with most infants succumbing to the condition in the neonatal period.
- Early management in the 1970s was limited to supportive care, offering little hope for long-term survival.
- The lack of effective treatments necessitated a paradigm shift in pediatric cardiac care.
Observation:
- The introduction of the Norwood procedure in the early 1980s marked a turning point in HLHS management.
- This surgical innovation initiated a series of palliative procedures aimed at supporting single-ventricle physiology.
- Subsequent decades have seen continuous refinement of surgical techniques and perioperative care.
Findings:
- Modern HLHS management, centered around staged surgical palliation including the Norwood procedure, enables survival beyond infancy.
- A majority of children with HLHS now survive the neonatal period and can live into early adulthood.
- Innovations over the past 40 years have dramatically altered the clinical course and outcomes for HLHS patients.
Implications:
- The advancements in HLHS treatment offer improved quality of life and extended survival for affected individuals.
- Continued research into surgical techniques and long-term care is crucial for further enhancing outcomes.
- The evolution of HLHS management serves as a model for progress in treating complex congenital heart defects.
Abstract:
The management of hypoplastic left heart syndrome (HLHS) has changed substantially over the past four decades. In the 1970s, children with HLHS could only be provided with supportive care. As a result, most of these unfortunate children died within the neonatal period. The advent of the Norwood procedure in the early 1980s has changed the prognosis for these children, and the majority now undergoing a series of three surgical stages that can support survival beyond the neonatal period and into early adulthood. This review will focus on the Norwood procedure and the other important innovations of the last half century that have improved our outlook toward children born with HLHS.

Related Concept Videos
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 01:29
Cardiomyopathy V: Interprofessional Care
 01:30
Cardiomyopathy II: Dilated Cardiomyopathy
 01:28
Cardiomyopathy VII: Pre and Post Operative Nursing Management
 01:22
Heart Failure VI: Adjunct Therapies
 01:29
Cardiomyopathy VI: Nursing Management