Related Experiment Video
Updated: Mar 14, 2026


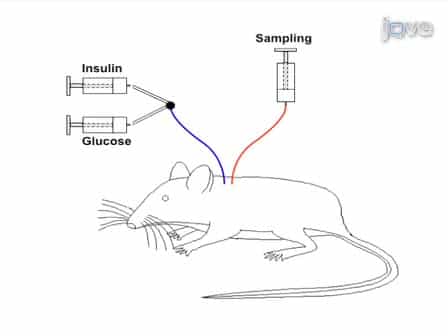
Hyperinsulinemic-euglycemic Clamps in Conscious, Unrestrained Mice
Published on: November 16, 2011
Hyperinsulinemic-normoglycemic clamp administered together with amino acids induces anabolism after cardiac surgery
Takumi Codère-Maruyama1, Thomas Schricker2, Dominique Shum-Tim3
1Department of Anesthesia, McGill University, Montreal, Quebec, Canada; takumi.coderemaruyama@mcgill.ca.

Cardiac surgery triggers an inflammatory stress response, leading to protein catabolism, a process that even high-dose insulin therapy alone cannot reverse. To determine whether hyperinsulinemic-normoglycemic clamp and perioperative amino acid (AA) supplementation improves whole body protein balance, 20 patients scheduled for elective coronary artery bypass grafting surgery were randomly assigned to have intra- and postoperative hyperinsulinemic-normoglycemic clamp, with or without intravenous AA supplementation. Primed continuous infusions of [6,6-2H2]glucose and l-[1-13C]leucine were used to quantify whole body protein and glucose metabolism before and after surgery. Adipose tissue and serum cytokines were also analyzed to measure their responsiveness to the anabolic effect of AA administration. During hyperinsulinemic-normoglycemic clamp, AA supplementation successfully stimulated whole body protein synthesis, resulting in a positive whole body protein balance after surgery (insulin: -13.6 ± 4.5 vs. insulin + AA: 2.1 ± 5.4 μmol·kg-1·h-1, P < 0.001). Endogenous glucose production was equally suppressed in both groups (insulin: 0.0 ± 3.8 vs. insulin + AA 1.6 ± 1.6 μmol·kg-1·min-1, P = 0.230). AA supplementation led to significant changes in serum and tissue IL-6 (insulin: 246.6 ± 111.2 vs. insulin + AA: 124.5 ± 79.3 pg/ml, P = 0.011). In conclusion, hyperinsulinemic-normoglycemic clamp technique, together with AA supplementation, can induce an anabolic state after open-heart surgery, as quantified by a positive whole body protein balance.
Cardiac surgery triggers an inflammatory stress response, leading to protein catabolism, a process that even high-dose insulin therapy alone cannot reverse. To determine whether hyperinsulinemic-normoglycemic clamp and perioperative amino acid (AA) supplementation improves whole body protein balance, 20 patients scheduled for elective coronary artery bypass grafting surgery were randomly assigned to have intra- and postoperative hyperinsulinemic-normoglycemic clamp, with or without intravenous AA supplementation. Primed continuous infusions of [6,6-2H2]glucose and l-[1-13C]leucine were used to quantify whole body protein and glucose metabolism before and after surgery. Adipose tissue and serum cytokines were also analyzed to measure their responsiveness to the anabolic effect of AA administration. During hyperinsulinemic-normoglycemic clamp, AA supplementation successfully stimulated whole body protein synthesis, resulting in a positive whole body protein balance after surgery (insulin: -13.6 ± 4.5 vs. insulin + AA: 2.1 ± 5.4 μmol·kg-1·h-1, P < 0.001). Endogenous glucose production was equally suppressed in both groups (insulin: 0.0 ± 3.8 vs. insulin + AA 1.6 ± 1.6 μmol·kg-1·min-1, P = 0.230). AA supplementation led to significant changes in serum and tissue IL-6 (insulin: 246.6 ± 111.2 vs. insulin + AA: 124.5 ± 79.3 pg/ml, P = 0.011). In conclusion, hyperinsulinemic-normoglycemic clamp technique, together with AA supplementation, can induce an anabolic state after open-heart surgery, as quantified by a positive whole body protein balance.
Related Concept Videos
 01:15
Hypoglycemia and Glucagon
 01:25
Metabolic States of the Body: The Absorptive State
 01:27
Glucose Homeostasis: Pancreatic Islets and Insulin Secretion
Insulin and C-peptide are...
 01:18
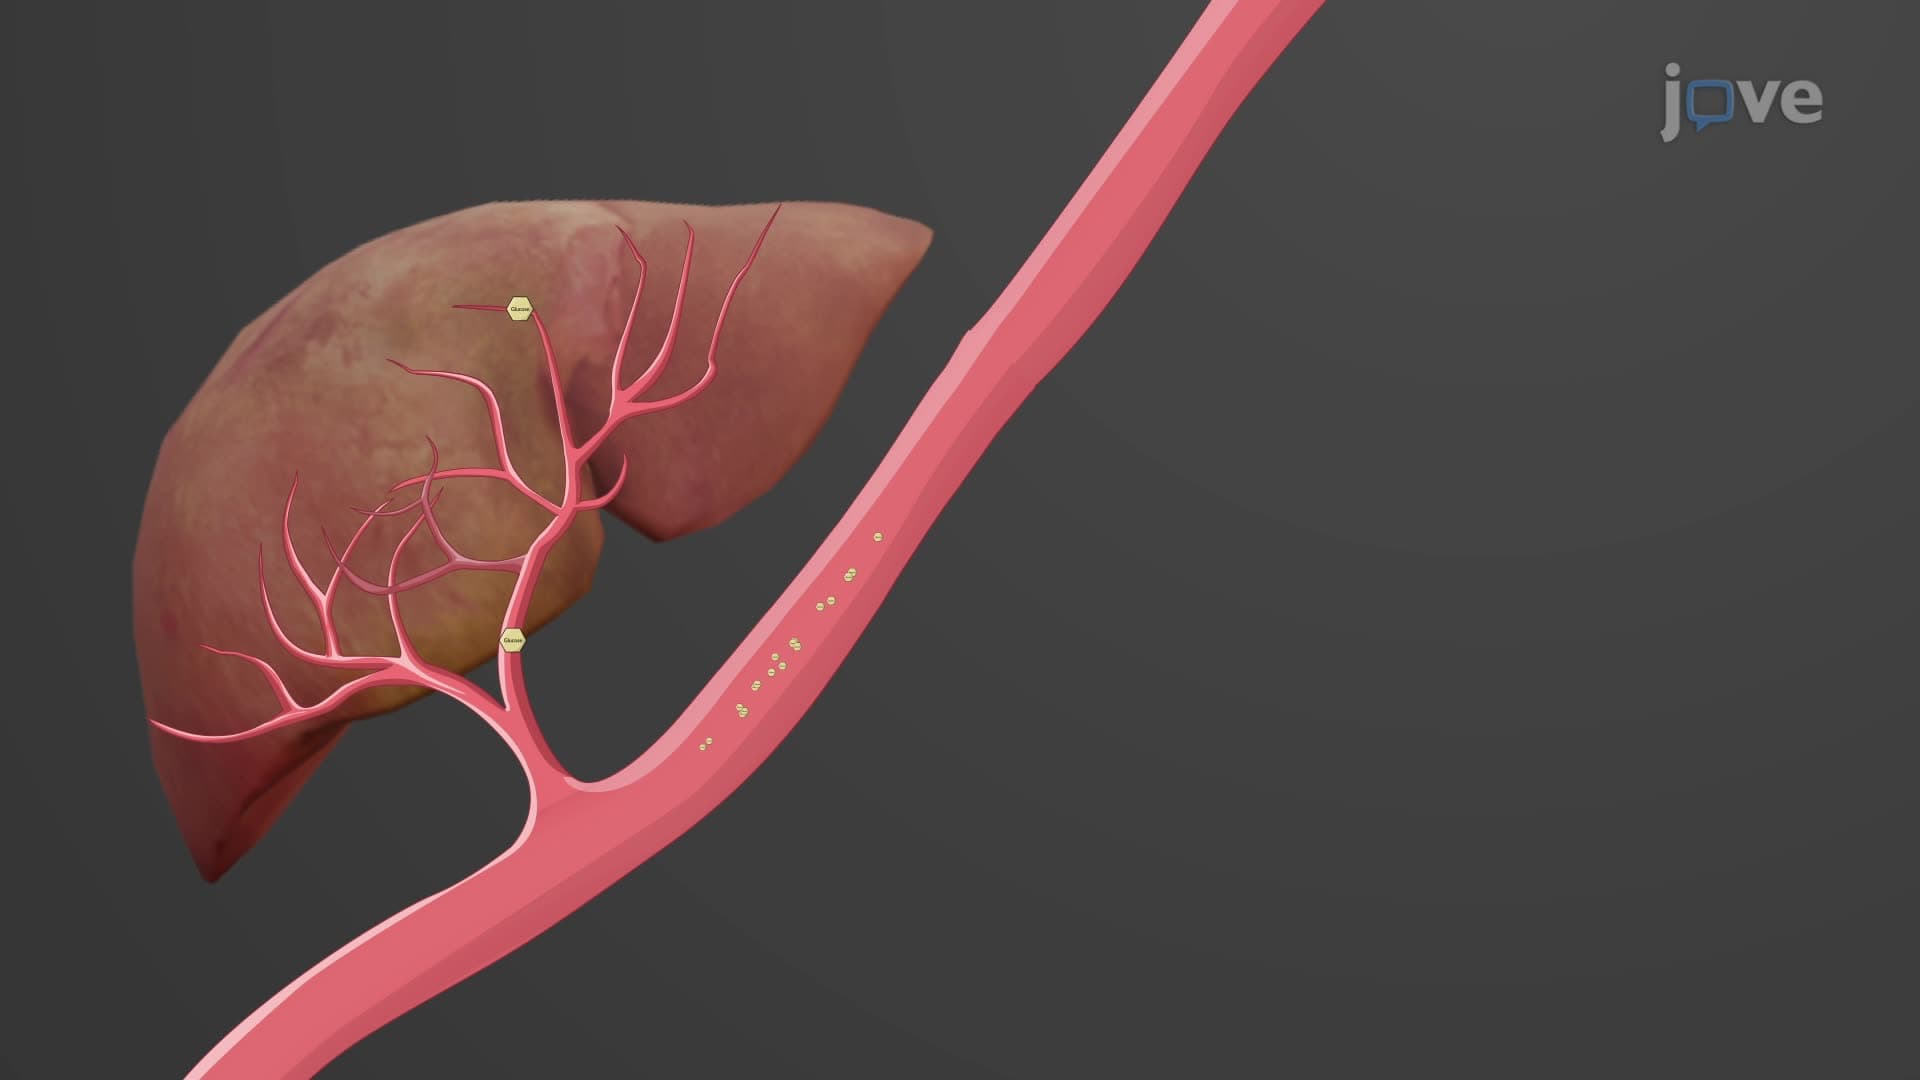
Metabolic States of the Body: The Postabsorptive State
Initially, glycogen stored in the liver is broken down to release glucose into the bloodstream, while glycogen in the muscles is broken down to supply glucose for energy directly within the muscle cells. As glycogen stores diminish,...
 01:16
Insulin: Dosing Regimen and Adverse Effects
The basal dose constitutes about 40%-50% of the total daily dose, with the rest as premeal insulin. The mealtime insulin dose should mirror...
 01:24
Glucagon-like Receptor Agonists
GLP-1, when administered in high doses intravenously, triggers insulin secretion, inhibits glucagon release, slows gastric emptying, reduces food intake, and restores normal insulin secretion. However, its rapid inactivation by...