Related Experiment Video
Updated: Mar 13, 2026


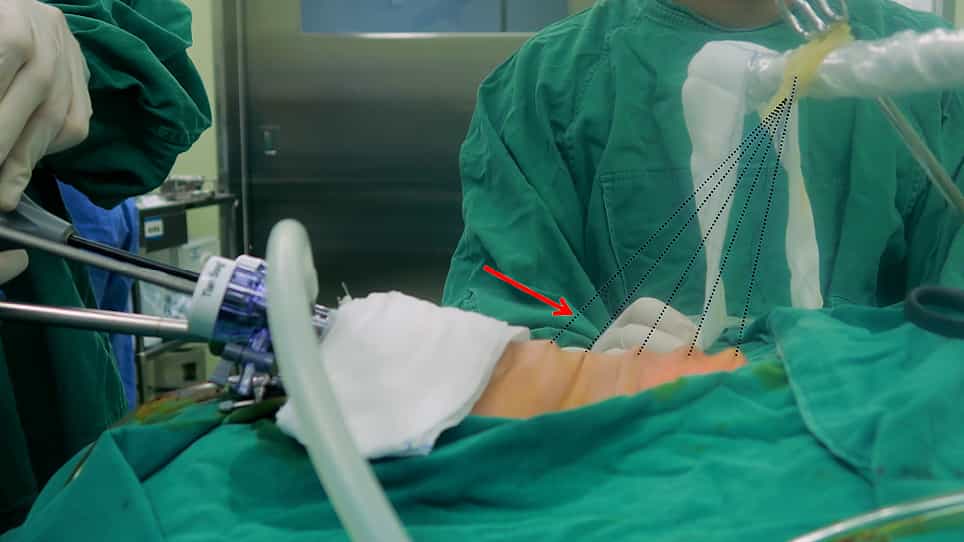
Subcostal Specimen Removal in Completely Portal Robotic Lobectomy
Published on: April 19, 2024
Video-assisted thoracoscopic lobectomy: which is the learning curve of an experienced consultant?
Antonio Mazzella1, Anne Olland2, Pierre Emmanuel Falcoz1
1Department of Thoracic Surgery, Hôpitaux universitaires de Strasbourg, Nouvel Hôpital Civil, Place de l'Hôpital 1, 67000 Strasbourg, France.

Background:
This study evaluates the number of video-assisted thoracic surgery-lobectomies (VATS-lobectomies) required for an experienced consultant thoracic surgeon to obtain competence and to perform standard quality surgery.
Methods:
We have analysed the initial VATS-experience (January 2012 to September 2014) of a confirmed senior consultant who has performed 145 consecutive anatomic resections by thoracoscopy. After excluding bilobectomies, segmentectomies, and lobectomies for infectious disease, we have focused into 119 consecutive lobectomies, classified into 4 chronologic groups of 30 each. We have considered: demographics; pathology; postoperative outcomes; conversion rate; morbidity. We compared the 4 groups in a Bayesian inference model (very strong probability of a difference if Pr>95% or <5%; strong probability if 95%>Pr>80% or 5%
Results:
There was a very strong probability of difference of group 1 (first 30 lobectomies) compared to the 3 other groups: less incomplete fissures (Pr1<2=0.019, Pr1<3=0.037, Pr1<4=0.046), more node samplings (Pr1>2=0.977, Pr1>3=0.96, Pr1>4=0.997) and, conversely, less radical dissections (Pr1<2=0.022, Pr1<3=0.039, Pr1<4=0.003), less harvested nodes (Pr1<2≤0.001, Pr1<3≤0.001, Pr1<4≤0.001), less pleural adhesions (Pr1<2=0.077, Pr1<3=0.044). Instead, there was a very strong probability of difference of group 4 compared to the first three groups (first 90 lobectomies): lower conversion rate (Pr1>4=0.992, Pr3>4=0.996, Pr2>4=0.995), lower duration of the operation (Pr1>4=0.946, Pr2>4=0.901, Pr3>4=0.932), less air leak (Pr1>4=0.936, Pr2>4=0.97) and shorter chest tube drainage (Pr1>4=0.94, Pr2>4=0.94, Pr3>4=0.937), as well as shorter hospital stay (Pr2>4=0.94, Pr3>4=0.937).
Conclusions:
The learning curve was bimodal. After the initial 30 lobectomies, oncologic quality of the procedure improved and stabilized. The surgeon became less selective and accepted to proceed with more complex cases (incomplete fissures, pleural adhesions). Efficiency was obtained after 90 lobectomies (shorter operative time and lower conversion rate).
More Related Videos

Related Concept Videos
 01:26
Endoscopic Studies II: Thoracocentesis
Description
Excess pleural fluid or air may accumulate in some respiratory disorders in the thoracic cavity. To treat pleural effusion, a physician conducts thoracentesis by carefully piercing the chest wall and entering...
 01:30
Endoscopic Studies I: Bronchoscopy and Thoracoscopy
Bronchoscopy
Description
Bronchoscopy is a procedure that involves direct visualization of the larynx, trachea, and bronchi for diagnostic and therapeutic purposes. A flexible fiber optic or rigid bronchoscope is used to carry out the procedure. The fiber-optic bronchoscope is more frequently used due...
 01:16
Tracheostomy Care I: Pre-procedural Steps
Required Equipment
The equipment necessary for tracheostomy care includes:
 01:26
Tracheostomy Suctioning I: Pre-Procedural Steps
Equipment Required
First, gather all necessary equipment: a sterile suction catheter, a sterile disposable container, sterile gloves, a towel or...
 01:25
Tracheostomy Care II: Procedure
Step 1: Perform hand hygiene, and put on personal protective equipment: gown, gloves, mask...
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques