Related Experiment Video
Updated: Mar 13, 2026

Author Spotlight: Advancing Awake Nasotracheal Intubation with Flexible Video Rhino-Laryngoscopes
Published on: August 2, 2024
Effects of an elevated position on time to tracheal intubation by novice intubators using Macintosh laryngoscopy or
Abraham K C Wai1, Colin A Graham1
1Accident and Emergency Medicine Academic Unit, The Chinese University of Hong Kong, Shatin, Hong Kong.

Objective:
To investigate the time to tracheal intubation using Glidescope videolaryngoscopy (GVL) compared to that of standard laryngoscopy, by using a Macintosh blade (SLM) in a human patient simulator in supine and elevated (ramped) positions.
Methods:
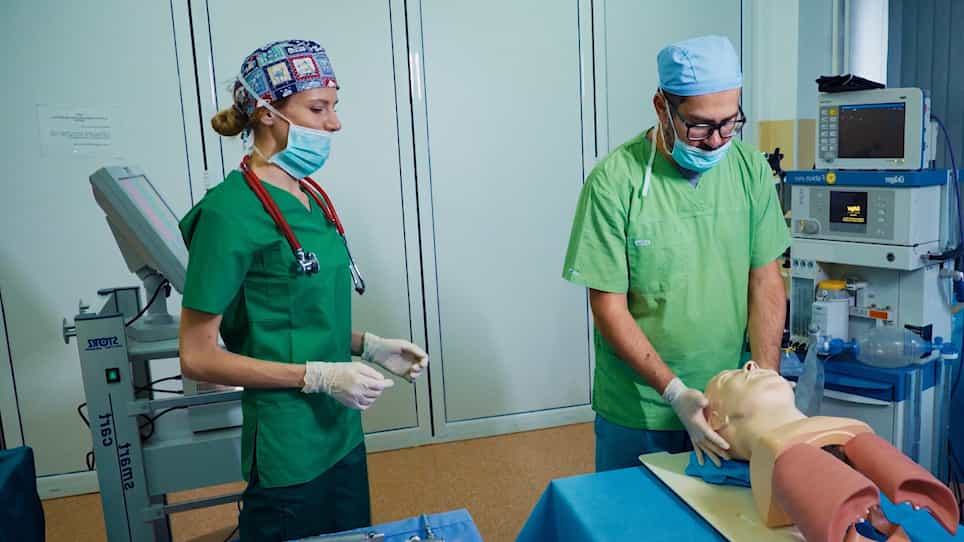
In this randomized crossover design, novice intubators (first-year medical students), using both laryngoscopic techniques, attempted tracheal intubation on a human patient simulator with a "normal airway" anatomy (Cormack-Lehane grade I). The simulator was placed in both supine and ramped positions using a commercial mattress system. The mean time to intubation and complications were compared between GVL and SLM in both positions. The percentage of glottic opening (POGO, GVL only) was estimated during intubation in the ramped and supine positions. The primary outcome was time to intubation, and the secondary outcomes included complication rates such as esophageal intubation and dental trauma.
Results:
There was no difference in the mean time to intubation in either position (P=0.33). The SLM intubation was significantly faster than GVL (mean difference, 1.5 minutes; P<0.001). The mean POGO score for GVL improved by 8% in the ramped position compared to that in supine position (P=0.018). The esophageal intubation rate for SLM was 15% to 17% compared to 1.3% for GVL; dental trauma occurred in 53% to 56% of GVL, compared to 2% to 6% for SLM (P<0.001, respectively).
Conclusion:
Novices had shorter intubation times using standard laryngoscopy with a SLM compared to GVL in both supine and ramped positions. GVL resulted in fewer esophageal intubations, but more dental trauma than standard laryngoscopy.
Related Concept Videos
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques
 01:15
Endotracheal Intubation I: Procedure
The ET tube comprises various components, including a standard adaptor to attach a bag-valve-mask (BVM) or ventilator, a cuff, a pilot balloon, and radiopaque markings along its length to measure the insertion distance. The tube sizes...
 01:17
Endotracheal Intubation II: Nursing Management
1. Nursing Care of Patients Before Intubation
Before the endotracheal intubation procedure, nurses play an essential role in ensuring the process goes smoothly. The nurses must be familiar with intubation...
 01:24
Endotracheal Tube Extubation
Procedure
Extubation removes the endotracheal tube (ETT) from the patient on mechanical ventilation. It requires a well-coordinated, multidisciplinary approach involving physicians, nurses, respiratory therapists, and other healthcare professionals....
 01:26
Tracheostomy Suctioning I: Pre-Procedural Steps
Equipment Required
First, gather all necessary equipment: a sterile suction catheter, a sterile disposable container, sterile gloves, a towel or...
 01:28
Tracheostomy: Procedure and Tubes
Tracheostomy tubes can be made of semiflexible plastic (polyurethane or silicone), rigid plastic, or metal, and they come in...