Related Experiment Video
Updated: Mar 13, 2026
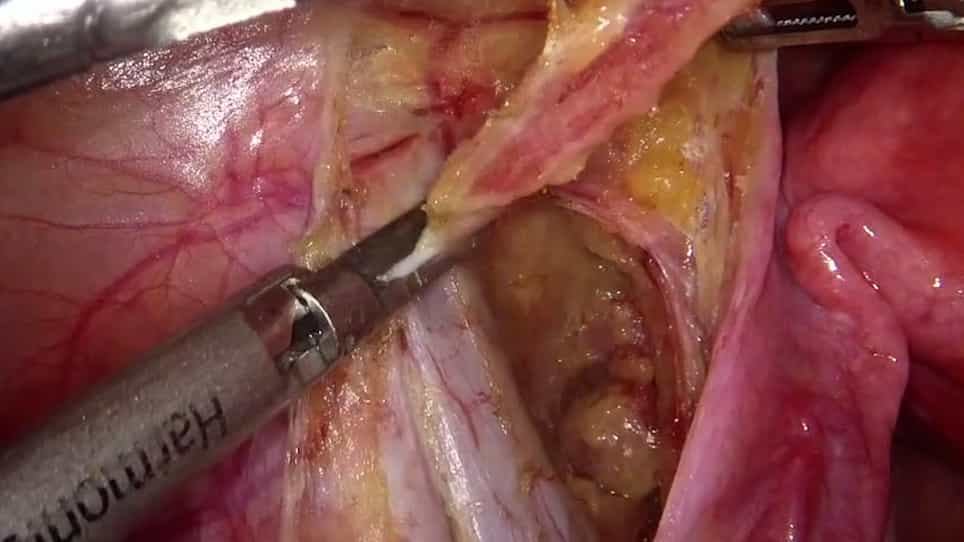
Sentinel Lymph Node Mapping and Biopsy for Endometrial Cancer at Early Stage with Laparoscopy
Published on: August 19, 2021
Current perspectives of sentinel lymph node dissection at the time of radical surgery for prostate cancer
Gavish Munbauhal1, Thomas Seisen2, Florie D Gomez3
1Academic Department of Urology of La Pitié-Salpétrière, Assistance-Publique Hôpitaux de Paris, Faculté de Médecine Pierre et Marie Curie, University Paris 6, 75013 Paris, France.

Abstract:
The sentinel lymph node dissection (SLND) concept relies on the accurate detection of primary nodal landing sites and could represent a major advancement towards accurate, non-invasive pelvic staging in prostate cancer (PCa). Different iterations of the technique have now been validated and reproduced mostly in large-volume centres. The existing evidence denotes the feasibility and sensitivity of SLND, with encouraging pre- and intraoperative detection rates of 98% and 96%. Yet, current surgical practice mandates a backup template dissection due to a false negative rate, up to 7.1%, of tracer-guided surgery. In practice, SLND failed to achieve nodal detection in up to 20% of pelvic sidewalls. Despite scarce validated evidence, current consensus mainly attributes these false negative cases to altered prostatic drainage secondary to malignant obliteration of lymphovascular structures. In parallel, multiple SLND studies have highlighted the complex and variable drainage pathways from the prostate, furthering the established anatomical atlases. The most promising approach may therefore rely in magnetic nanoparticles and PCa-targeting ligands. However, in the absence of a clear sentinel node or region for the prostate, formal SLND is difficult to integrate in routine surgical practice for now. As such, tracer-guided dissection is only used as a complementary intervention to highlight first- echelon nodes and aberrant lymphatic pathways found beyond the commonly adopted pelvic lymphadenectomy templates.