Related Experiment Video
Updated: Mar 13, 2026
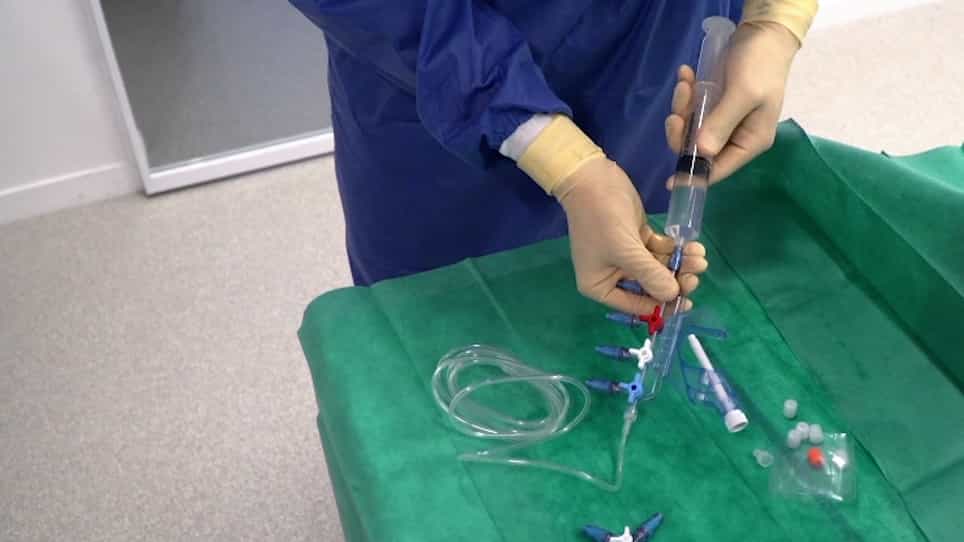
A Protocol to Set Up Needle-Free Connector with Positive Displacement on Central Venous Catheter in Intensive Care Unit
Published on: July 13, 2019
Economic Evaluation of Quality Improvement Interventions for Bloodstream Infections Related to Central Catheters: A
Teryl K Nuckols1, Emmett Keeler2, Sally C Morton3
1Cedars-Sinai Medical Center, Los Angeles, California2RAND Corporation, Santa Monica, California.

Importance:
Although quality improvement (QI) interventions can reduce central-line-associated bloodstream infections (CLABSI) and catheter-related bloodstream infections (CRBSI), their economic value is uncertain.
Objective:
To systematically review economic evaluations of QI interventions designed to prevent CLABSI and/or CRBSI in acute care hospitals.
Evidence Review:
A search of Ovid MEDLINE, Econlit, Centre for Reviews & Dissemination, New York Academy of Medicine's Grey Literature Report, Worldcat, prior systematic reviews (January 2004 to July 2016), and IDWeek conference abstracts (2013-2016), was conducted from 2013 to 2016. We included English-language studies of any design that evaluated organizational or structural changes to prevent CLABSI or CRBSI, and reported program and infection-related costs. Dual reviewers assessed study design, effectiveness, costs, and study quality. For each eligible study, we performed a cost-consequences analysis from the hospital perspective, estimating the incidence rate ratio (IRR) and incremental net savings. Unadjusted weighted regression analyses tested predictors of these measures, weighted by catheter-days per study per year.
Findings:
Of 505 articles, 15 unique studies were eligible, together representing data from 113 hospitals. Thirteen studies compared Agency for Healthcare Research and Quality-recommended practices with usual care, including 7 testing insertion checklists. Eleven studies were based on uncontrolled before-after designs, 1 on a randomized controlled trial, 1 on a time-series analysis, and 2 on modeled estimates. Overall, the weighted mean IRR was 0.43 (95% CI, 0.35-0.51) and incremental net savings were $1.85 million (95% CI, $1.30 million to $2.40 million) per hospital over 3 years (2015 US dollars). Each $100 000-increase in program cost was associated with $315 000 greater savings (95% CI, $166 000-$464 000; P < .001). Infections and net costs declined when hospitals already used checklists or had baseline infection rates of 1.7 to 3.7 per 1000 catheter-days. Study quality was not associated with effectiveness or costs.
Conclusions And Relevance:
Interventions related to central venous catheters were, on average, associated with 57% fewer bloodstream infections and substantial savings to hospitals. Larger initial investments may be associated with greater savings. Although checklists are now widely used and infections have started to decline, additional improvements and savings can occur at hospitals that have not yet attained very low infection rates.

Related Concept Videos
 01:22
Healthcare Associated Infections II: Preventive Measures
The best practices for preventing healthcare-associated infections include hand hygiene, patient risk...
 01:30
Health Information Technology and Healthcare Information System
Health Information Technology, commonly called HIT, integrates advanced information systems and technology in healthcare settings. Its primary functions include:
 01:29
Endocarditis IV: Nursing Management
 01:29
Venous Thrombosis III: Interprofessional Care
 01:26
Healthcare Associated Infections I: Iatrogenic, Exogenic and Endogenic
HAIs significantly increase the cost of health care. Extended stays in healthcare institutions, increased disability, increased costs of medications, including specialized antibiotics, and prolonged recovery times add to the patient's expenses and the healthcare institution and funding bodies.
 01:30
Venous Thrombosis IV: Nursing Management