Related Experiment Video
Updated: Mar 12, 2026

Home-Based Prescribed Pulmonary Exercise in Patients with Stable Chronic Obstructive Pulmonary Disease
Published on: August 24, 2019
Chronotropic incompetence can limit exercise tolerance in COPD patients with lung hyperinflation
Sébastien Hulo1, Jocelyn Inamo2, Aurélie Dehon3
1Université Lille, CHU Lille, EA 4483, IMPact de l'Environnement Chimique sur la Santé humaine, Lille, France.

Purpose:
Metabolic-chronotropic relationship is the only concept that assesses the entire chronotropic function during exercise, as it takes into account individual fitness. To better understand interrelationships between chronotropic incompetence (CI), dynamic hyperinflation (DH) and exercise limitation among Global initiative for chronic Obstructive Lung Disease (GOLD) stages of chronic obstructive pulmonary disease (COPD) disease severity, we evaluated cardiopulmonary responses to symptom-limited cycle exercise in stable patients.
Patients And Methods:
We prospectively studied 47 COPD patients classified by GOLD stage severity. Pulmonary function tests and cardiopulmonary responses to symptom-limited incremental exercise were studied. CI was defined by regression line between percent heart rate (HR) reserve and percent oxygen uptake (V'O2) reserve, ie, chronotropic-metabolic index (CMI). DH was defined from the knot resulting from the nonlinear regressions of inspiratory capacity changes from rest to peak (dynamic inspiratory capacity (ICdyn)) with percentage of maximal HR and CMI.
Results:
Aerobic capacity (median interquartile ranges) peak V'O2, 24.3 (23.6; 25.2), 18.5 (15.5; 21.8), 17.5 (15.4; 19.1) mL·kg-1·min-1 and CMI worsened according to GOLD severity. The optimal knot of ICdyn was equal to -0.34 L. The multivariate logistic regression showed a strong relationship between CI (outcome) and DH (odds ratio [confidence interval 95]) 25 (3.5; 191.6).
Conclusion:
COPD patients with DH have a poor cardiovascular response to exercise, which may be attributed to CI.
More Related Videos
 08:44
Author Spotlight: Integrating Alveolar-Capillary Reserve Measurements in Exercise Adaptation and Therapeutic Strategies
Published on: February 2, 2024
 09:33
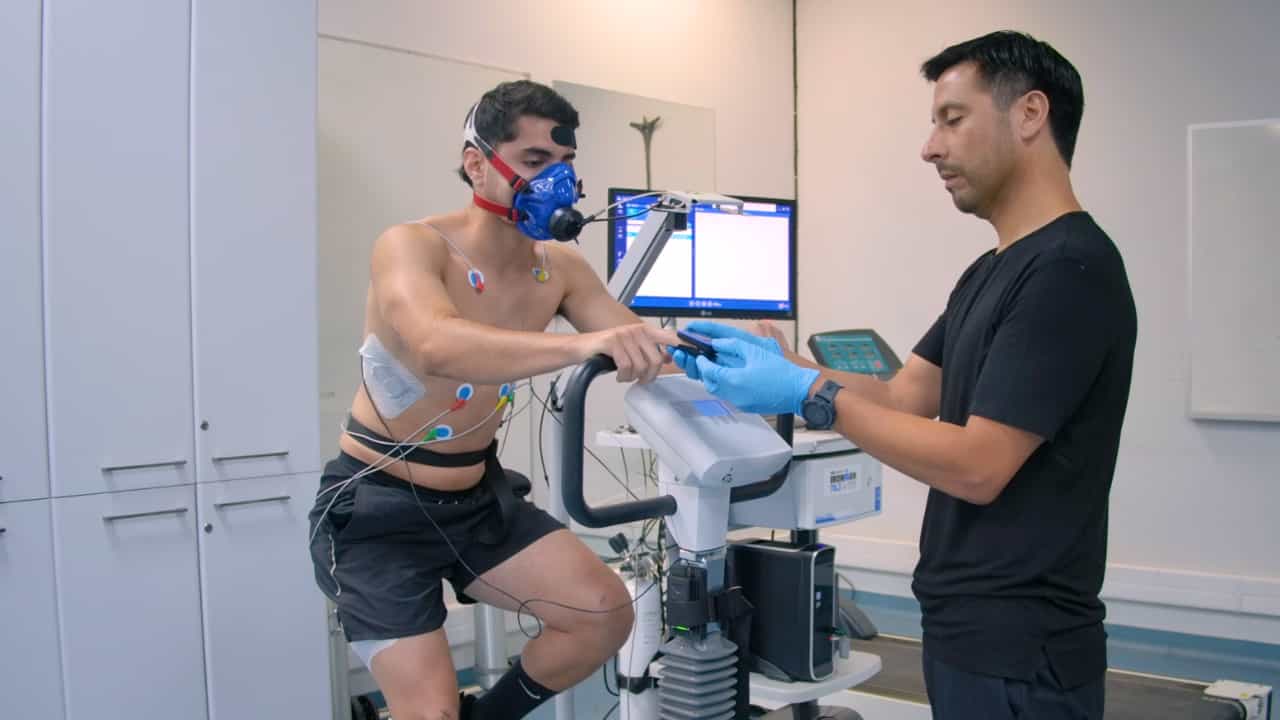
Using Near-Infrared Spectroscopy Wearable Devices to Identify Central Versus Peripheral Limitations During Exercise
Published on: December 19, 2024
Related Concept Videos
 01:26
COPD: Management Using Bronchodilators and Corticosteroids
 01:20
Chronic Obstructive Pulmonary Disease-I: Introduction
 01:26
Imbalances in Cardiac Output
CHF can occur due to the failure of either side of the heart. Left-side failure leads to pulmonary congestion—the right side continues to send...
 01:25
Hyperpnea and Hyperventilation
 01:24
Chronic Obstructive Pulmonary Disease
Smoking is a primary risk factor for COPD, with over 80% of patients having a history of it. Patients typically experience progressive dyspnea or labored breathing, frequent coughing, and recurrent pulmonary infections. Many eventually succumb to respiratory failure, characterized by...
 01:25
Chronic Obstructive Pulmonary Disease-III: Symptoms and Complications.
Symptoms of COPD can be classified as primary or systemic. Primary symptoms relate to reduced airflow, while systemic or extrapulmonary symptoms relate to COPD's broader impact on the body.
Primary Symptoms of COPD: