Related Experiment Video
Updated: Mar 12, 2026


Minimally Invasive Treatment for Thoracolumbar Burst Fracture Using Sagittal Alignment Screws and A Trauma Reduction Device
Published on: November 8, 2024
Outcomes of Spinal Fusion for Cervical Kyphosis in Children with Neurofibromatosis
Ilkka J Helenius1, Paul D Sponseller2, William Mackenzie3
1Department of Pediatric Orthopaedic Surgery, University of Turku and Turku University Hospital, Turku, Finland ilkka.helenius@utu.fi.

Background:
Cervical kyphosis may occur with neurofibromatosis type I (NF1) and is often associated with vertebral dysplasia. Outcomes of cervical spinal fusion in patients with NF1 are not well described because of the rarity of the condition. We aimed to (1) characterize the clinical presentation of cervical kyphosis and (2) report the outcomes of posterior and anteroposterior cervical fusion for the condition in these children.
Methods:
The medical records and imaging studies of 22 children with NF1 who had undergone spinal fusion for cervical kyphosis (mean, 67°) at a mean age of 11 years and who had been followed for a minimum of 2 years were reviewed.
Results:
Thirteen children presented with neck pain; 10, with head tilt; 9, with a previous cervical laminectomy or fusion; and 5, with a neurologic deficit. Two patients had spontaneous dislocation of the mid-cervical spine without a neurologic deficit. Eleven had scoliosis, with the major curve measuring a mean of 61°. Nine patients underwent posterior and 13 underwent anteroposterior surgery. Twenty-one received spinal instrumentation, and 1 was not treated with instrumentation. Preoperative halo traction was used for 9 patients, and it reduced the mean preoperative kyphosis by 34% (p = 0.0059). At the time of final follow-up, all spinal fusion sites had healed and the cervical kyphosis averaged 21° (mean correction, 69%; p < 0.001). The cervical kyphosis correction was significantly better after the anteroposterior procedures (83%) than after the posterior-only procedures (58%) (p = 0.031). Vertebral dysplasia and erosion continued in all 17 patients who had presented with dysplasia preoperatively. Thirteen patients had complications, including 5 new neurologic deficits and 8 cases of junctional kyphosis. Nine patients required revision surgery. Junctional kyphosis was more common in children in whom ≤5 levels had been fused (p = 0.054).
Conclusions:
Anteroposterior surgery provided better correction of cervical kyphosis than posterior spinal fusion in children with NF1. Erosion of vertebral bodies continued during the postoperative follow-up period in all patients who had presented with dysplastic changes preoperatively. The cervical spine should be screened in all children with NF1. Fusion should include at least 6 levels to prevent junctional kyphosis.
Level Of Evidence:
Therapeutic Level III. See Instructions for Authors for a complete description of levels of evidence.
Related Concept Videos
 01:16
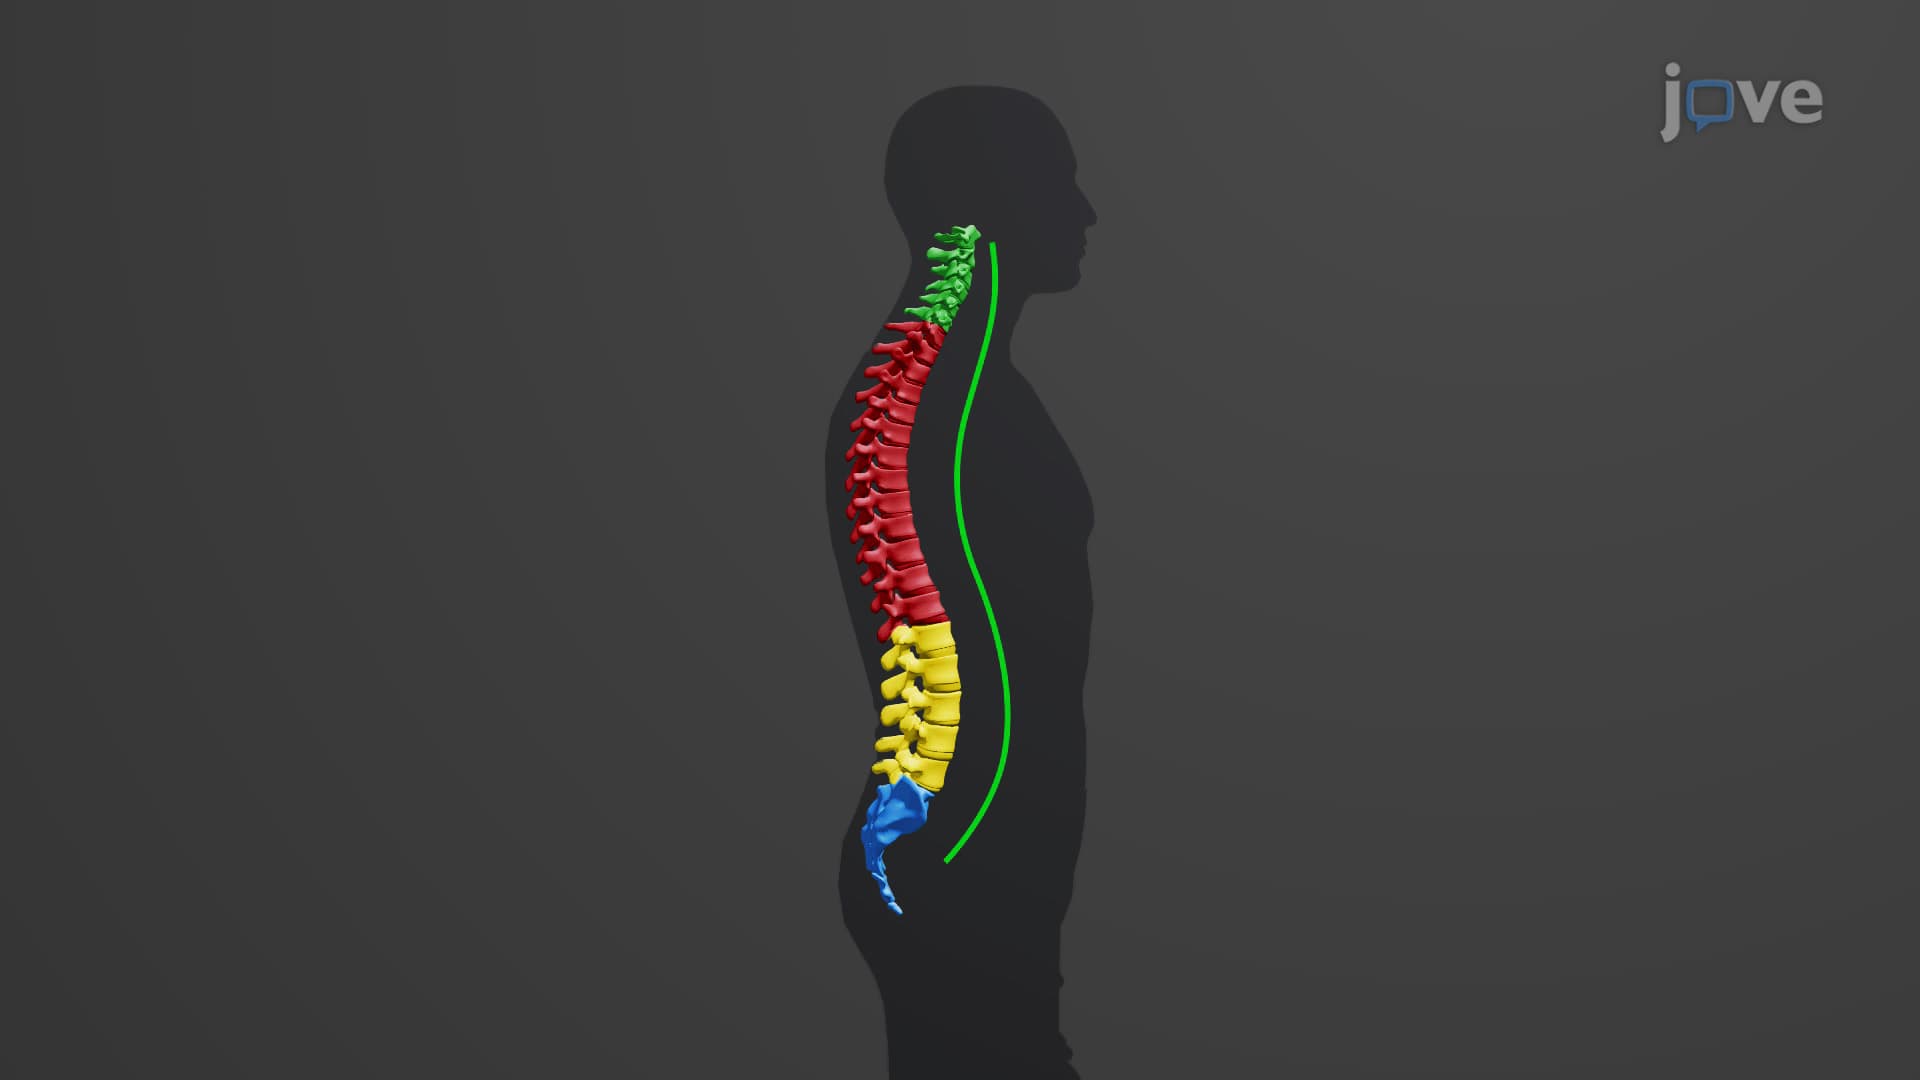
Vertebral Column: Regions and Curvature
Regions of the Vertebral Column
In an adult, the spine is subdivided into five regions: the cervical, the thoracic, the lumbar, the sacral, and the coccygeal region. The spine initially develops as a series of 33 vertebrae; after 20 years of age, the nine bones in the sacral region, five sacral, and four coccygeal bones fuse to form...
 01:22
Sutures of the Skull
Sutures are immobile joints between adjacent bones of the skull. The narrow gap between the bones is filled with dense, fibrous connective tissue that unites the bones. The long sutures located between the skull bones are not straight but instead follow irregular, tightly twisting paths. These twisting lines tightly...