Related Experiment Video
Updated: Mar 12, 2026
Gene Transfer for Ischemic Heart Failure in a Preclinical Model
Published on: May 15, 2011
Adenosine receptors expression in cardiac fibroblasts of patients with left ventricular dysfunction due to valvular
Silvia Del Ry1, Manuela Cabiati1, Veronica Della Latta1,2
1a CNR, Institute of Clinical Physiology , Pisa , Italy.

Context:
Adenosine restores tissue homeostasis through the interaction with its membrane receptors (AR) expressed on fibroblasts, endothelial cells, smooth muscle cells and leukocytes, but their modulation is still not fully understood.
Objective:
To evaluate whether changes in the transcriptomic profiling of adenosine receptors (AR) occur in cardiac fibroblasts (CF) of patients (pts) with LV dysfunction due to valvular disease (V). The secondary aim was to compare in the same pts the results obtained at cardiac level with those found in circulating leukocytes.
Materials And Methods:
Auricle fragments were excised from 13 pts during prosthetic implantation while blood samples were collected from pts (n = 9) and from healthy subjects (C, n = 7). In 7 pts cardiac biopsy and blood samples were taken simultaneously. A human CF atrial cell line (cc) was used as control.
Results:
AR higher levels of mRNA expression were observed with real-time PCR in Vpts compared to C, both at cardiac (overexpression A1R:98%, A2AR:63%, A2BR:87%, A3R:85%, CD39:92%, CD73:93%) and at peripheral level (A1R vs C: p = .0056; A2AR vs C: p = .0173; A2BR vs C: p = .0272; A3R vs C: p = .855; CD39 vs C: p = .0001; CD73 vs C: p = .0091).
Conclusion:
All AR subtypes were overexpressed in CF of Vpts. The same trends in AR expression at cardiac level was assessed on circulating leukocytes, thus opening a new road to minimally invasive studies of the adenosinergic system in cardiac patients.
More Related Videos


Related Concept Videos
 01:29
Heart Failure II: Pathophysiology
 01:17
Pathophysiology of Heart Failure
 01:26
Heart Failure Drugs: Inhibitors of Renin-Angiotensin System
 01:26
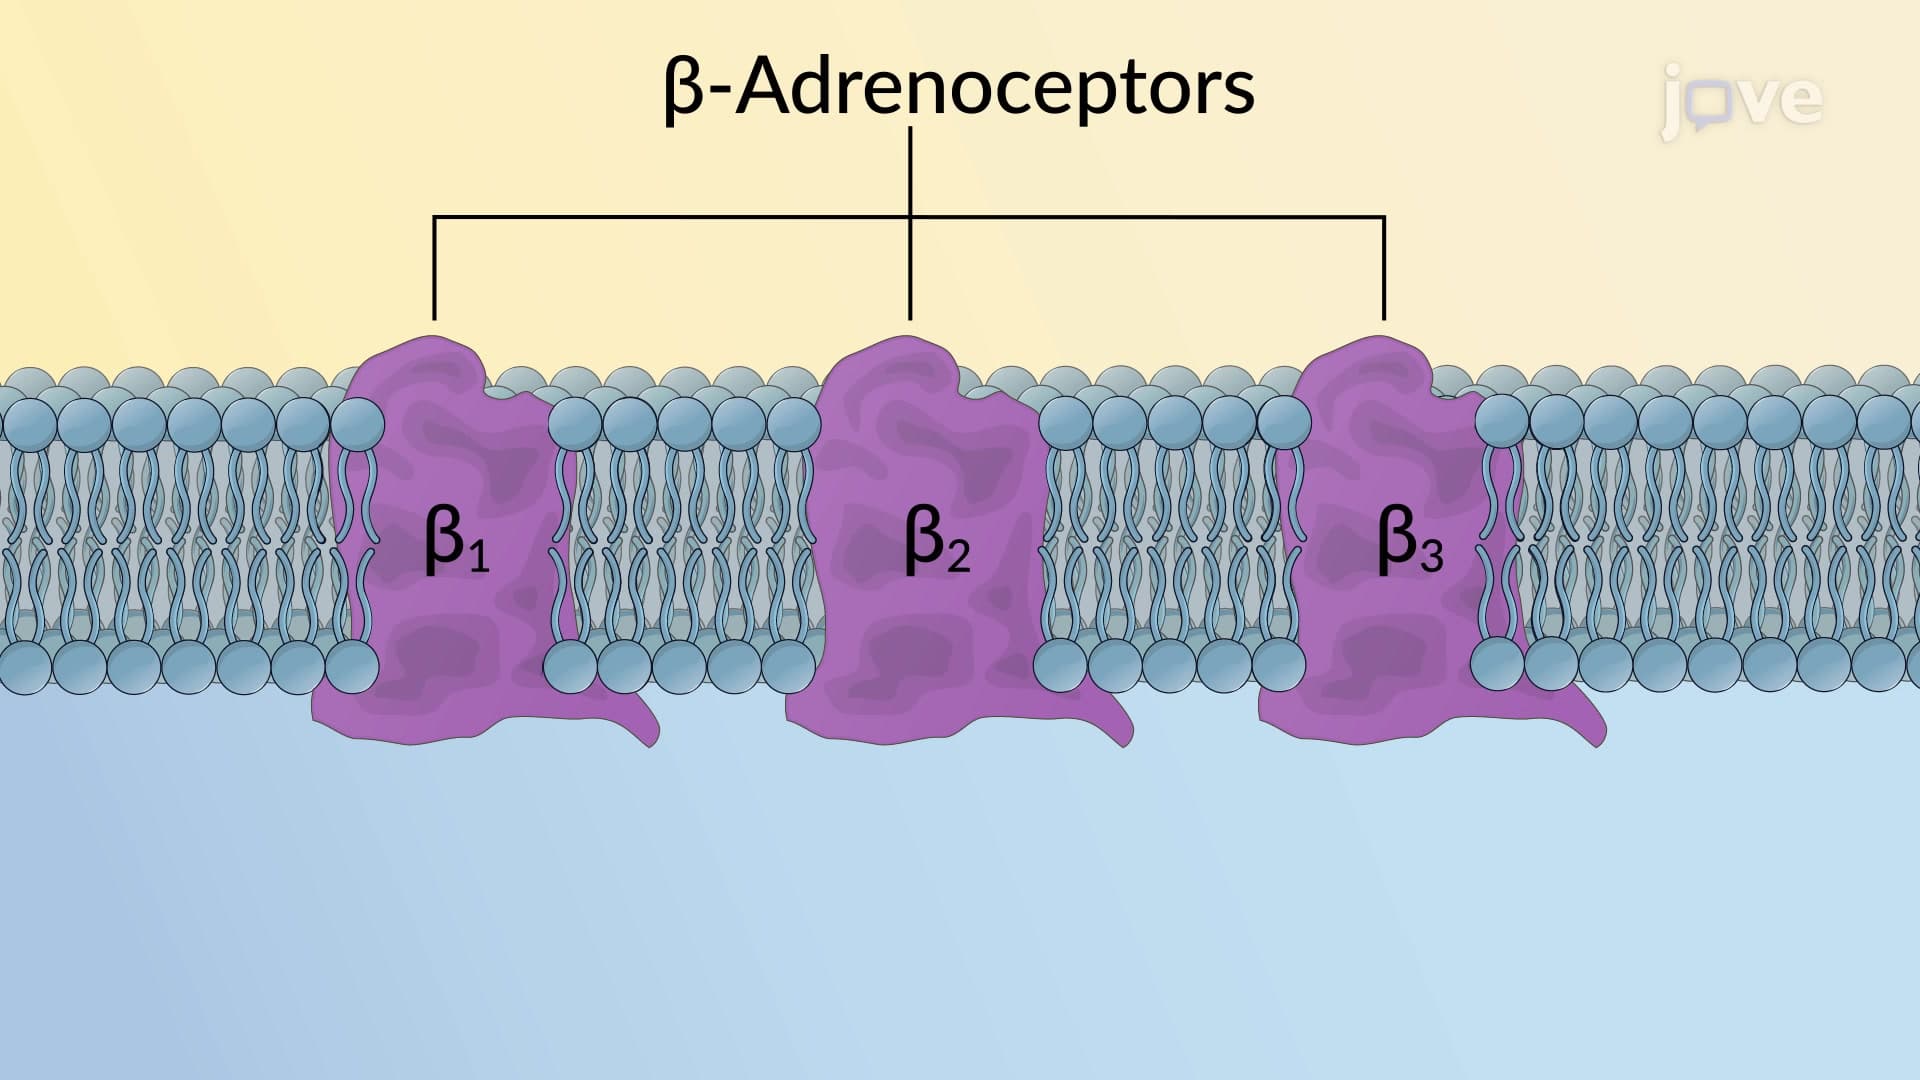
Adrenergic Receptors: β Subtype
Isoprenaline > Adrenaline > Noradrenaline
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors...
 01:31
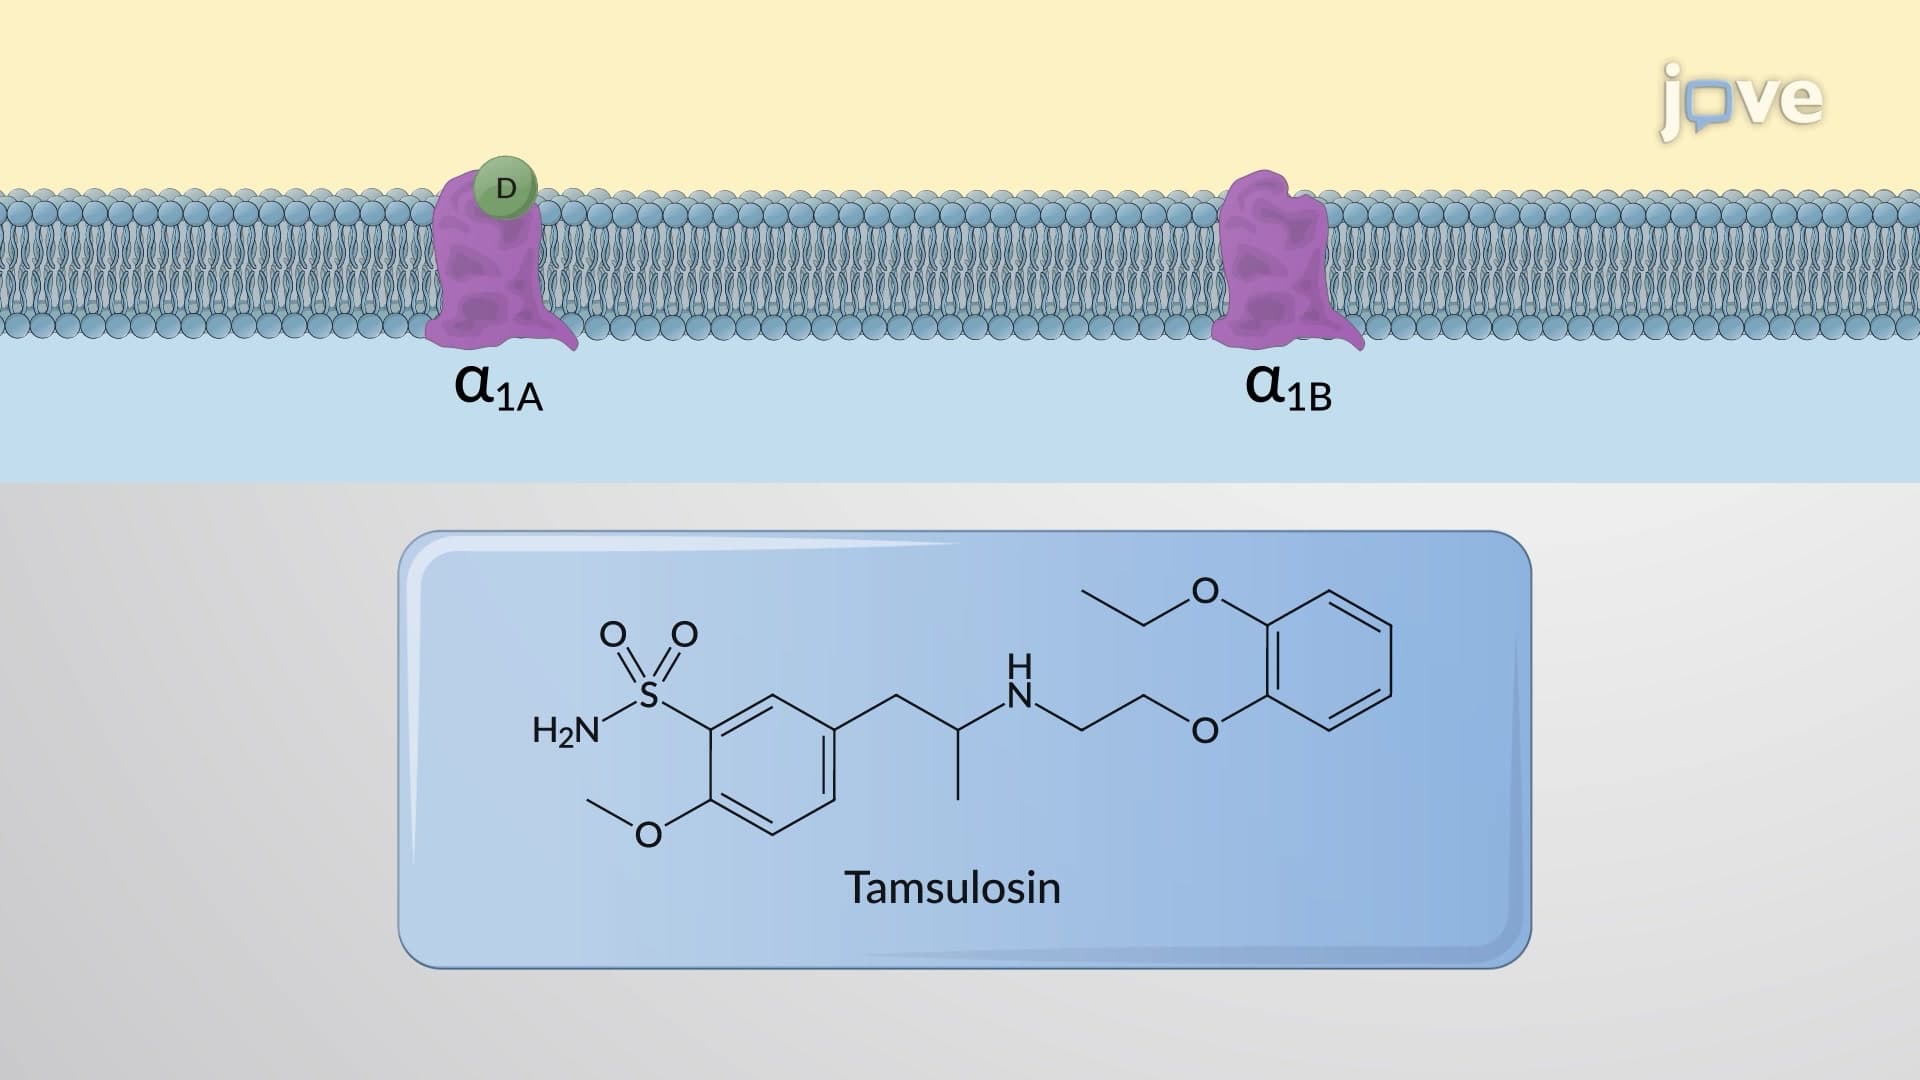
Adrenergic Receptors: ɑ Subtype
Adrenaline ≥ Noradrenaline >> Isoprenaline
α-adrenoceptors are further divided into α1 and α2-adrenoceptors.
α1-Adrenoceptors: These receptors are located postsynaptically on the effector organs and cause constriction of smooth muscle mediated by activation of phospholipase...
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy