Related Experiment Video
Updated: Mar 12, 2026
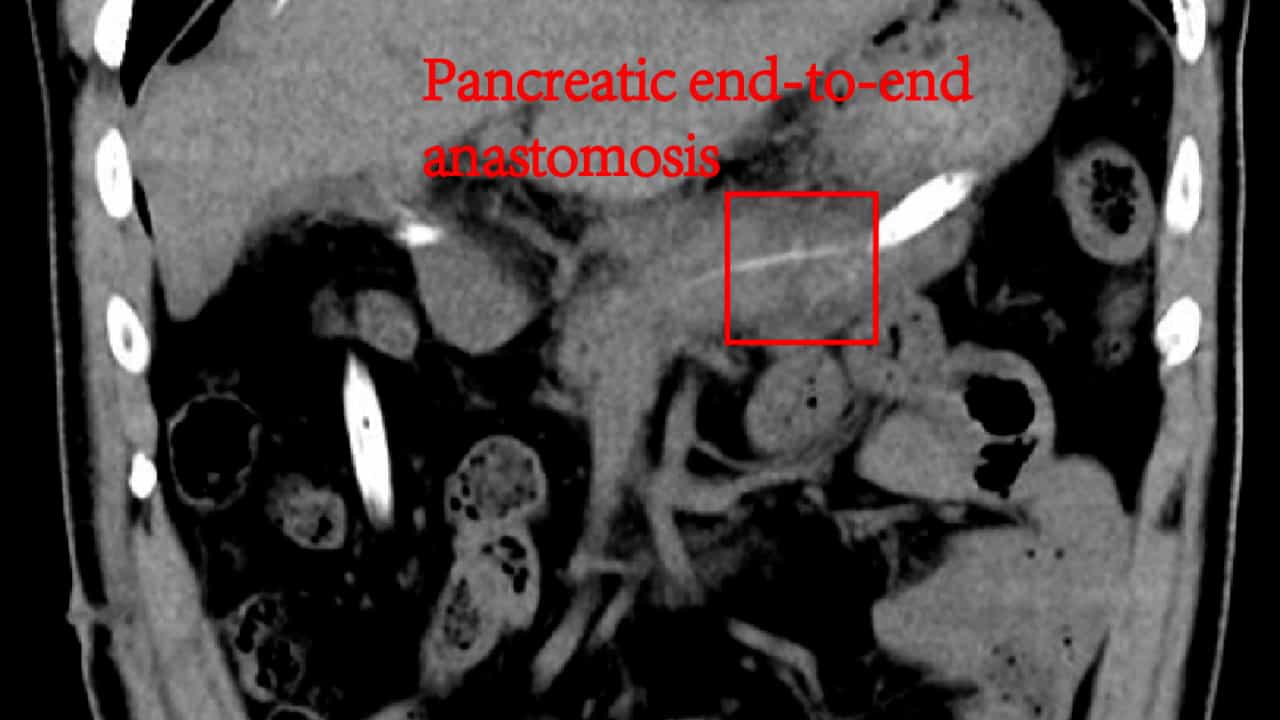

Application of Mid-Pancreatectomy with End-to-End Anastomosis in Pancreatic Benign Tumors
Published on: February 9, 2024
Trends in utilization of neoadjuvant therapy and short-term outcomes in resected pancreatic cancer
Katelin A Mirkin1, Christopher S Hollenbeak2, Niraj J Gusani1
1Department of Surgery, The Pennsylvania State University, College of Medicine, Hershey, PA, USA.

Background:
Surgical resection and chemotherapy offer the only chance of long-term survival for pancreatic cancer. Neoadjuvant therapy (NAT) is increasingly used to optimize outcomes. Trends in NAT utilization and short-term outcomes in resected pancreatic cancer were evaluated.
Methods:
The National Cancer Database (2003 to 2011) was analyzed for pancreatic cancer patients who underwent surgery ± NAT, evaluating utilization, 30- and 90-day mortality, hospital readmissions, and length of stay (LOS).
Results:
About 16,007 underwent initial surgery and 1,736 received NAT. Over the past decade, initial surgery and multimodality NAT have steadily decreased, whereas the use of neoadjuvant radiation has remained low and the use of neoadjuvant chemotherapy (neoCT) has steadily increased. Thirty- and 90-day mortality rates and hospital readmissions were significantly higher for NAT vs initial surgery on univariate analysis. There was no significant difference in LOS or readmission rate. On multivariate analysis, neoCT had no significant impact on odds of mortality at 30 and 90 days (hazard ratio = .68, P = .285, hazard ratio = 1.32, P = .161, respectively). Advanced age, greater comorbidities, greater clinical stage disease, and resection with pancreaticoduodenectomy or total pancreatectomy negatively impacted 30- and 90-day mortality.
Conclusion:
The use of neoCT has increased over the past decade and does not appear to adversely affect short-term outcomes, including 30- and 90-day mortality, LOS, and readmission rates.